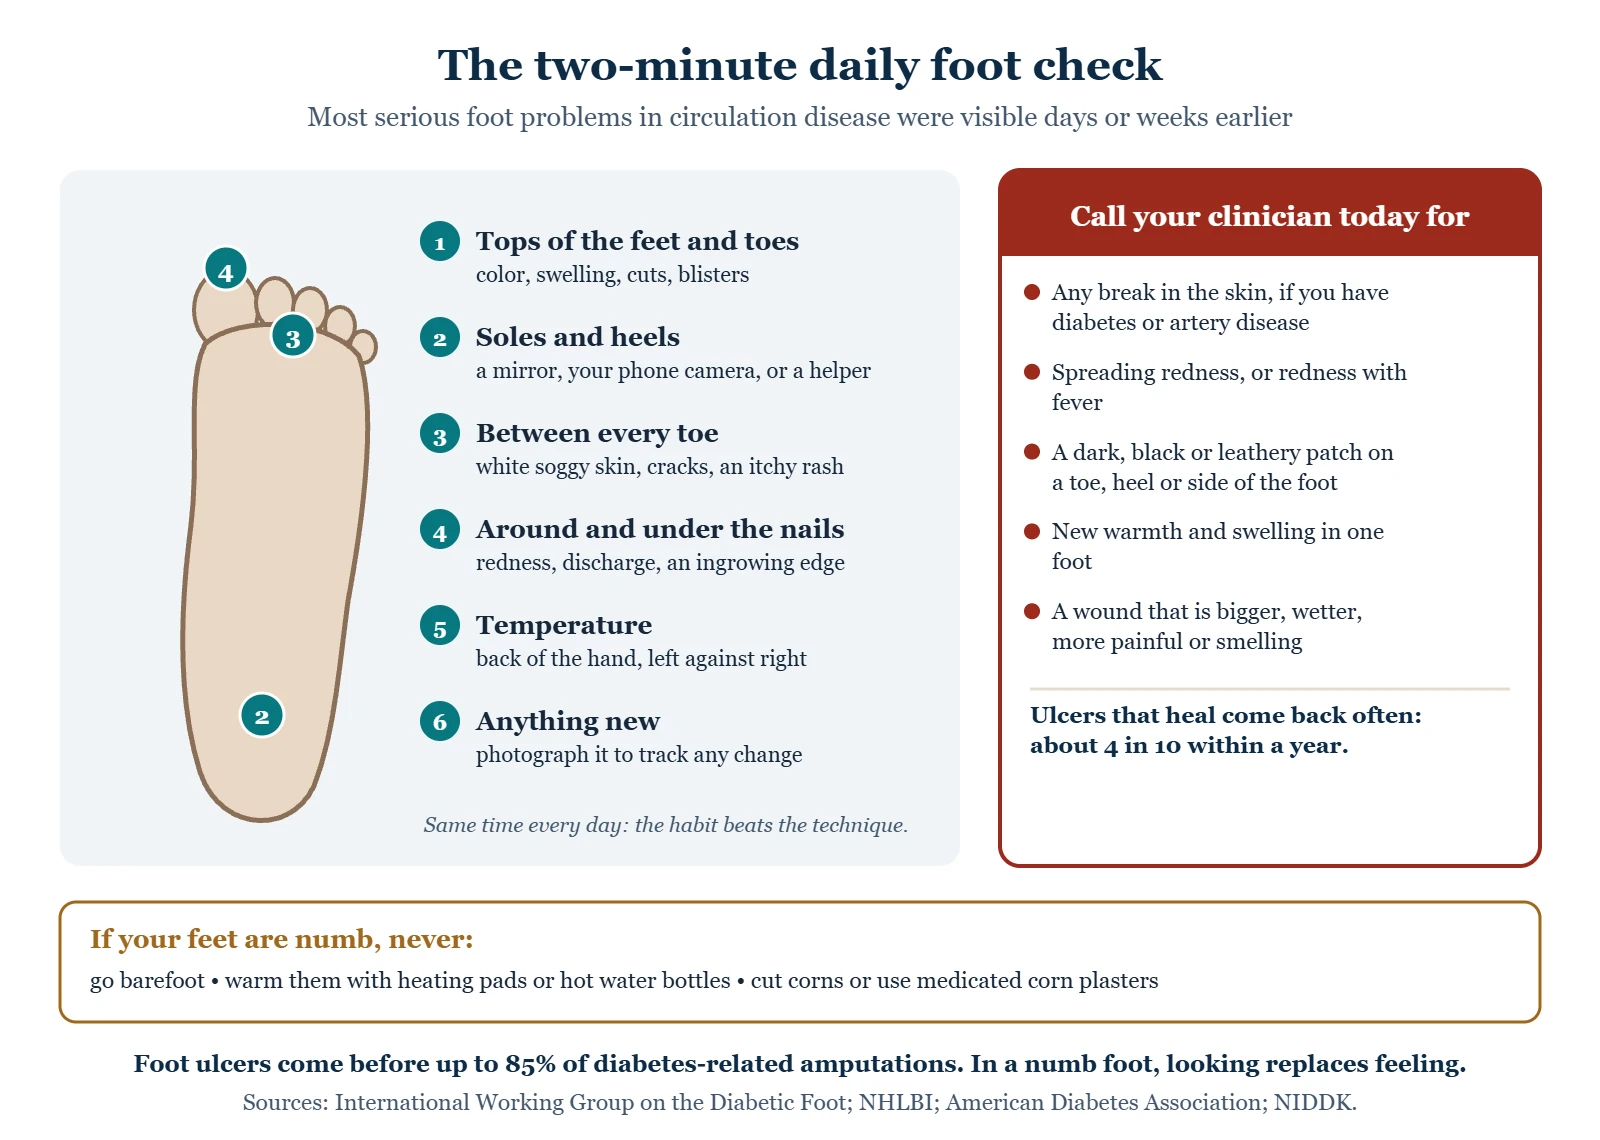
Almost every serious foot problem in circulation disease starts as something small that was visible days or weeks earlier. A two-minute daily look is the single highest-value habit on this site.
What you find that means calling today
- A break in the skin, however small, if you have diabetes or known artery disease
- New or spreading redness (an emergency department now if it spreads fast, leaves a red streak, or comes with a fever, chills or feeling unwell, or if you have diabetes, numb feet or poor circulation)
- A new dark area on a toe, heel or the side of the foot (an emergency department now if it is black, gray or dark purple, or looks dead)
- A new area of warmth and swelling in one foot, particularly with reduced sensation
- Any wound that is larger, wetter, more painful, or starting to smell
Why it matters this much
People with diabetes have a 19 to 34% lifetime risk of a foot ulcer, and the International Working Group on the Diabetic Foot notes that foot ulcers come before up to 85% of diabetes-related amputations, with about half of people with a diabetic foot ulcer also having PAD. Ulcers that heal come back often — about 4 in 10 within a year. The American Heart Association calls foot care crucial in every form of PAD. Small, early and visible is the stage at which all of this is easiest to change.
The daily check
- Tops of the feet and toes. Color, swelling, cuts, blisters.
- Soles and heels. Use a mirror on the floor, or your phone camera, or ask someone. If you cannot see them, this is the part that gets missed — and it is where the important wounds are.
- Between every toe. Soft white macerated skin, cracks, or an itchy scaly rash. The fourth web space is the usual offender.
- Around and under the nails. Redness, discharge, an ingrowing edge.
- Feel the temperature with the back of your hand and compare left with right. A newly warm foot with swelling can be an early sign of a problem, particularly in a foot with reduced sensation.
- Note anything new and photograph it, so change is visible rather than remembered.
Do it at the same time every day — after a shower, or when you take your shoes off in the evening. The habit is worth more than the technique.
Skin care
- Wash daily in lukewarm water, and dry carefully — especially between the toes. Test water temperature with your hand or elbow, never your foot, if sensation is reduced.
- Moisturize the tops and soles with a plain, fragrance-free emollient. Dry skin cracks, and cracks let infection in. If the skin above your ankles is dry and itchy from vein disease, the American Academy of Dermatology suggests petroleum jelly or a fragrance-free ointment within a couple of minutes of bathing.
- Not between the toes. Moisture trapped there causes maceration and fungal infection.
- Do not soak. Long soaks soften and weaken skin, and hot water is a burn risk in a foot that cannot feel it.
- Treat athlete’s foot properly rather than ignoring it — the cracks it creates are a genuine entry point for cellulitis.
- Warm feet with socks, not heat. The American Diabetes Association warns that numb feet burn easily on hot water bottles and heating pads, and that the best way to warm cold feet is warm socks. Clean, dry socks in bed are fine.
Nails and calluses
If you have diabetes, reduced sensation, or known arterial disease, nail and callus care belongs with a professional; the National Heart, Lung, and Blood Institute specifically advises people with PAD not to treat corns, calluses or ingrown nails themselves. Bathroom scissors, razor blades and pharmacy corn removers are a common route to a wound in a foot that cannot feel what is happening. Medicated corn plasters contain acid and are a particular hazard — they do not distinguish between callus and healthy skin.
Callus itself is worth taking seriously. It forms where pressure is too high, and pressure high enough to build callus is pressure high enough to break skin underneath it. Callus with a dark spot in it is often a wound that has already started below the surface.
Footwear
- Check inside your shoes before every wear. A stone, a seam, a folded insole, a child’s toy. This is not an over-cautious ritual; it is a recurring cause of serious wounds.
- Seamless socks and well-fitting, low-heeled shoes, as NHLBI advises for people with PAD.
- Buy later in the day, when feet are at their largest.
- Depth matters as much as length and width — the toes need room above as well as in front.
- Treat any rub or red mark as information about the shoe, not something to break in. Shoes do not stretch faster than skin breaks.
- Never barefoot, indoors or out, if sensation is reduced. Slippers with a proper sole indoors.
- New shoes, short wear at first — an hour or two, then check the feet. Shoes for swollen feet →
Why “it does not hurt” is not reassuring
Nerve damage removes the warning system. In a foot with reduced sensation, a painless wound is the expected finding rather than a mild one — the absence of pain is the reason it went unnoticed long enough to matter. If you have any numbness, looking replaces feeling, and it has to happen daily.
From the clinic
Most of the wounds I treat in feet with poor circulation started with something mundane: new shoes, a nail trimmed too short, a heating pad, a pebble in a slipper. The ones caught on day one tend to heal in weeks. The ones found on day ten are the ones we fight over for months. The two-minute check is the difference between those two stories.
Common questions
How do I check my soles if I cannot reach or see?
A long-handled mirror, or a mirror flat on the floor. A phone camera on selfie mode works well and lets you zoom in. And asking someone is a perfectly good answer — it takes thirty seconds and it is what family members are usually glad to help with. For caregivers →
Is a foot spa or paraffin bath safe?
With reduced sensation or poor circulation, generally no. Heat is the problem — a temperature that feels pleasant to a hand can burn a foot that cannot register it, and the resulting wound is exactly the kind that struggles to heal.
Can I cut my own toenails?
If your sensation and circulation are normal and you can see and reach them comfortably, yes — straight across, not down the sides. With diabetes, numbness or known artery disease, professional care is the safer route.
How often should a professional look at my feet?
It depends on risk. People with diabetes are generally advised to have an annual foot check at minimum, and considerably more often with neuropathy, deformity, poor circulation or a history of ulceration; for people with both PAD and diabetes, NHLBI advises a foot examination twice a year. Ask what interval applies to you specifically.
What should I do if I find a small cut or blister?
Clean it gently with water, cover it with a simple dressing, and keep pressure off it. If you have diabetes or known artery disease, do not wait it out: the American Diabetes Association says every foot ulcer should be seen by a doctor right away, and NIDDK advises calling promptly about any foot sore that has not started to heal after a few days. Wounds that will not heal →
Where to go next
- Trench foot: keeping feet dry in cold, wet conditions
- Lymphangitis: when a foot wound sends red streaks up the leg
- Frostbite: protecting your feet in freezing weather
- Cellulitis: the skin infection that starts at cracks and athlete’s foot
- What to do about a wound that will not heal
- The rest of daily care
- When to seek care
- For caregivers: looking after someone else’s feet
- Shoes for swollen feet: what to look for
- Near Howell or Bloomfield Township, Michigan: a foot and ankle evaluation (the author’s own practice)
- Burning or numb feet: where to start
Sources
- National Institute of Diabetes and Digestive and Kidney Diseases. Diabetes and Foot Problems.
- National Institute of Neurological Disorders and Stroke. Peripheral Neuropathy.
- NHS. Leg ulcer — treatment.
- National Heart, Lung, and Blood Institute. PAD — Treatment.
- National Heart, Lung, and Blood Institute. Living with peripheral artery disease.
- American Heart Association. 2024 PAD guideline: top things to know.
- American Diabetes Association. Foot complications.
- MedlinePlus. Diabetes: taking care of your feet.
- International Working Group on the Diabetic Foot. Guideline on peripheral artery disease and diabetes-related foot ulcers (2023, PDF).
- International Working Group on the Diabetic Foot. Guideline on the prevention of foot ulcers (2023, PDF).
- StatPearls. Diabetic foot ulceration and complications.
- American Academy of Dermatology. Stasis dermatitis: self-care.
Written by Tom Biernacki, DPM, FACFAS. Published 20 September 2026. Updated 15 October 2026. General education, not medical advice.