The ankle-brachial index compares blood pressure at your ankle with blood pressure at your arm. It is quick and painless, involves no needles and no radiation, and it is the first-line test for peripheral artery disease (PAD). The number is simple; reading it well is not, and the most common mistake is being falsely reassured by a “normal” result.
Do not wait for a test appointment if
- a leg or foot suddenly turns cold, pale, numb or weak, or becomes severely painful — call 911. That is a blocked artery, not a scheduling question.
- your toes or forefoot ache at rest, especially at night and eased by hanging the foot over the bed, or there is a wound, blister or dark patch on the foot that is not healing — be seen the same day, and say so when you call (an emergency department now if any skin has turned black, gray or dark purple, or looks dead).
Who should have one
The ABI is a test for people with a reason to look, and the reasons fall into three groups:
- Symptoms or signs that suggest PAD — calf, thigh or buttock pain that comes on with walking and eases with rest, a wound on the foot or leg that is slow to heal, weak or absent foot pulses, or rest pain in the toes.
- Higher risk even without symptoms. The 2024 American College of Cardiology and American Heart Association guideline considers testing reasonable for people aged 65 or older; those aged 50 to 64 with diabetes, a history of smoking, high cholesterol, high blood pressure, chronic kidney disease or a family history of PAD; those under 50 with diabetes plus one other risk factor; and anyone with known atherosclerosis elsewhere, such as in the heart, neck or kidney arteries. It recommends against testing people outside those groups.
- Before compression for venous disease or a leg ulcer. Strong compression on a leg with poor arterial supply can cause harm, so an arterial check comes first. Why that order matters →
The numbers explain why. About 6% of US adults over 40 — some 7 million people — have an ABI of 0.90 or below, rising to about 17.5% of those aged 75 and over, and many of them have no leg symptoms at all. But the US Preventive Services Task Force concluded in 2018 that the evidence is insufficient to judge routine ABI screening in adults with no symptoms and no known heart, artery or severe kidney disease. That is a statement about screening the whole population, not about you: if you are in the higher-risk group above, it is a reasonable conversation to have with your clinician.
What happens during the test
- You rest lying flat for five to ten minutes or more so the pressures settle. This is part of the test, not waiting-room time — a reading taken straight after walking in from the parking lot can be misleading, and sitting instead of lying can raise the result by about 0.3.
- Blood pressure cuffs go on both arms and just above both ankles. You stay in your clothes apart from socks and shoes, and the cuff needs to be the right size for your limb.
- A small handheld Doppler probe with gel listens to each pulse while a cuff is inflated and slowly released. It makes a whooshing sound. At the ankle, the two main foot arteries — one on top of the foot, one behind the inner ankle bone — are each measured.
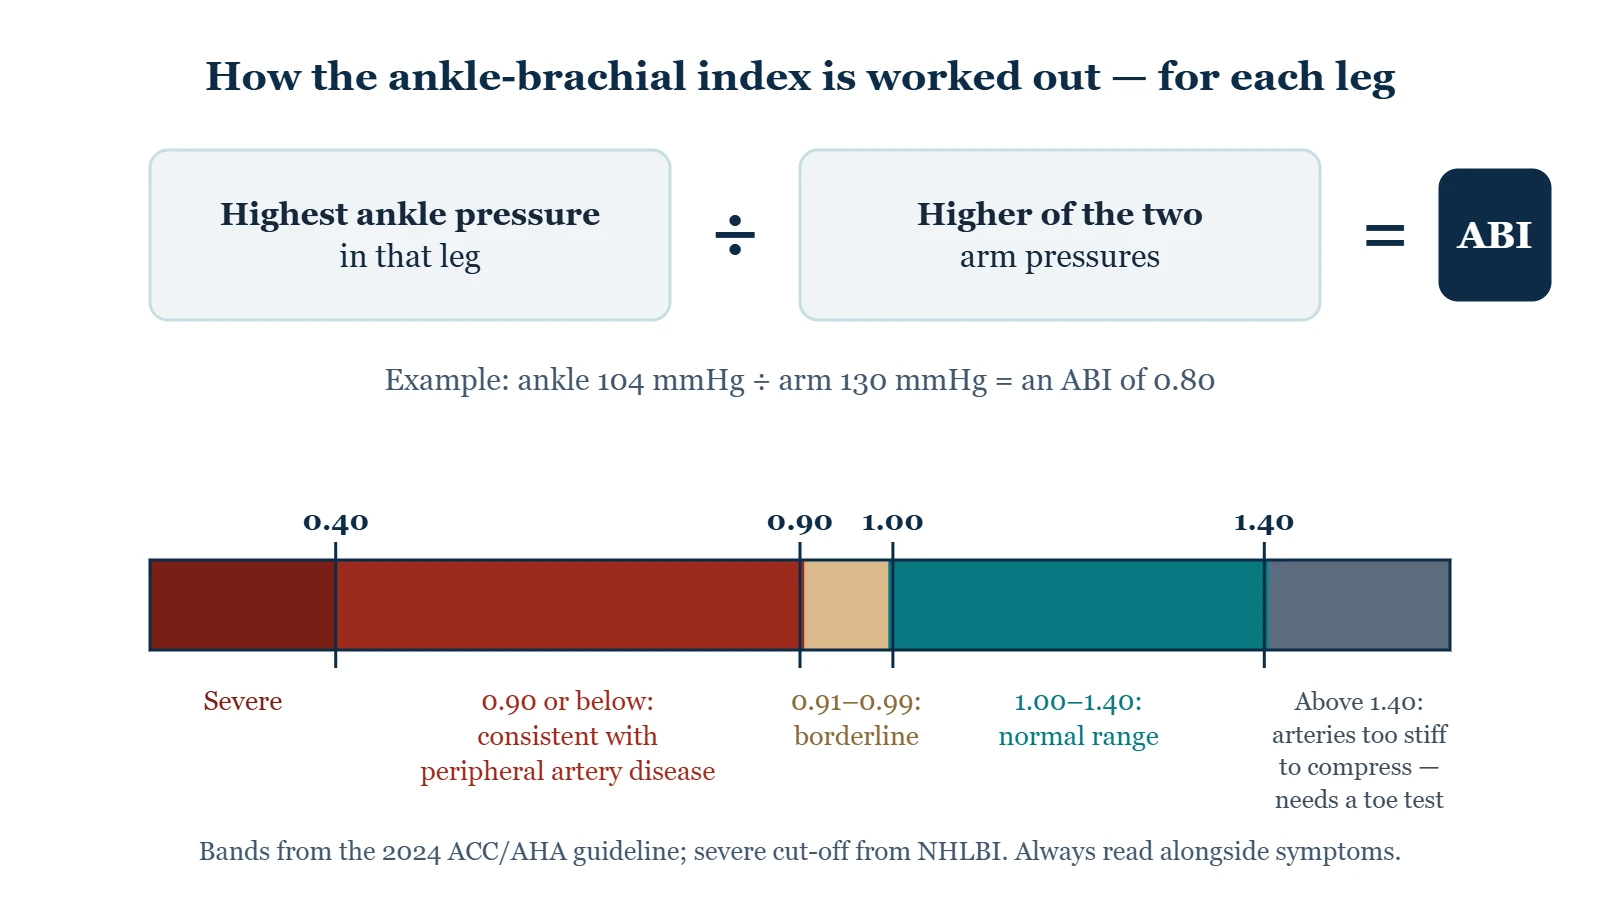
- The ratio is calculated for each leg separately: the higher of that leg’s two ankle pressures, divided by the higher of the two arm pressures.
There are no needles; the cuffs squeeze firmly for a moment, as with an ordinary blood pressure check. To prepare, skip caffeine on the day of the test, avoid tobacco, alcohol and exercise for an hour beforehand, and wear loose clothing. If you have a painful wound or rest pain, mention it — the person doing the test can adjust where the cuff goes. The readings themselves take only a few minutes; with the rest period, allow 15 to 30.
Reading the number
| ABI | Usually interpreted as | What tends to happen next |
|---|---|---|
| Above 1.40 | Non-compressible — the ankle arteries are too stiff to squeeze | Not reassuring. A toe pressure or toe-brachial index is needed |
| 1.00 to 1.40 | Normal range | If symptoms still fit PAD, an exercise ABI or toe test |
| 0.91 to 0.99 | Borderline | Often an exercise ABI; risk factors treated regardless |
| 0.90 or below | Peripheral artery disease | Medical treatment to protect the heart and brain, a walking program, and a plan for the legs |
| Below 0.40 | Severe disease | Urgent vascular assessment, particularly with rest pain or a wound |
The first four bands are the thresholds used in the 2024 ACC/AHA guideline; the severe cut-off is the one the National Heart, Lung, and Blood Institute uses. The lower the number, the more it matters whether there is pain at rest or tissue that needs to heal. The result also guides compression: above 0.8, full-strength compression can be considered; between 0.6 and 0.8, only reduced compression under supervision; and below 0.6, or with an ankle pressure under 60 mmHg or a toe pressure under 30 mmHg, no sustained compression and an urgent vascular referral.
A worked example
Arm pressures 132 and 128: the higher, 132, is used. Right ankle 120 and 116: the higher, 120, gives a right ABI of 120 ÷ 132 = 0.91, borderline. Left ankle 96 and 90: 96 ÷ 132 = 0.73, consistent with PAD in the left leg. Two legs, two results — and the person in this example will often say it is the left calf that aches on the walk to the mailbox.
The most important limitation
A normal or high ABI does not always mean healthy arteries. In diabetes, chronic kidney disease and in older age, calcium in the artery wall makes the ankle arteries hard to compress — so the cuff has to be inflated to a high pressure and the ratio comes out normal or falsely high. In one study of more than 2,000 tests, the resting ABI picked up only about half of significant narrowings in people with diabetes and fewer than half in kidney disease, while the toe-brachial index found 84% and 77%. Nearly a quarter of people with limb-threatening ischemia have an ABI in the normal range. A normal ABI in someone with real symptoms, or with a foot wound that is not healing, is a reason for more testing, not for reassurance.
The toe-brachial index and toe pressures
Toe arteries are rarely too stiff to compress, so a small cuff on the big toe gives a more trustworthy reading in exactly the people in whom the ABI misleads. The guideline recommends a toe pressure or toe-brachial index — toe pressure divided by the higher arm pressure — whenever the ABI is above 1.40, and it is commonly added when you have diabetes or kidney disease, or when the ABI looks normal but the story does not. A TBI of 0.70 or below is considered abnormal.
When there is a wound, the absolute toe pressure matters in its own right. The question is no longer just “is there disease?” but “is there enough blood pressure reaching the foot to heal this?” A toe pressure below 30 mmHg signals severe ischemia, a higher risk of amputation and a lower chance of healing. Transcutaneous oxygen (TcPO2), measured with a sensor on the skin of the foot, and skin perfusion pressure help too: a TcPO2 above 30 mmHg or a skin perfusion pressure above 40 mmHg makes healing more likely. Those are the numbers that move a wound from “dressings and offloading” to “the circulation needs fixing first”.
The exercise ABI
Narrowing can be mild enough to leave the resting pressures normal while still starving the calf muscles during walking. If your resting ABI is normal or borderline but your symptoms sound like claudication, the guideline recommends repeating the test one to five minutes after walking on a treadmill; earlier guidance accepted repeated heel raises where no treadmill is available. A drop in the ABI of 20% or more after exercise is considered abnormal. It is also a practical way to tell arterial leg pain from the look-alikes, such as spinal stenosis.
Other measurements you may see on the report
The common ones are below. For anything else, the plain-English glossary covers most of the words on a vascular report.
- Segmental pressures — three or four cuffs from thigh to ankle. A big drop between two cuffs points to whether the narrowing is in the pelvis, the thigh or below the knee.
- Pulse volume recordings (PVR) or Doppler waveforms — the shape of the pulse at each level. A healthy waveform is sharp; a flattened one suggests narrowing above that point. These still work when calcified arteries make the pressures unreliable.
- Duplex ultrasound — imaging of the arteries themselves, usually a separate appointment. What it adds →
If your ABI is low: what it changes
A low ABI is a leg finding with a whole-body meaning. The same hardening of the arteries is very likely to be present in the heart and neck arteries too: over five years, cardiovascular death is about 9% in people with a low ABI and no symptoms, and about 13% with symptoms, against about 5% with a normal ABI. That is why a diagnosis of PAD usually leads to:
- Medicines that protect the arteries — typically a statin and an antiplatelet medicine, plus control of blood pressure and blood sugar. Your prescriber decides the specifics.
- Stopping smoking, the single most powerful change for both the legs and the heart.
- A structured walking program, which improves walking distance more than most people expect. How it works →
- Foot protection — daily checks, proper footwear and early attention to any break in the skin, because healing is slower.
- Imaging and procedures only when they would change something — lifestyle-limiting symptoms despite treatment, rest pain, or a wound that needs more blood flow to heal. PAD treatment →
From the clinic
The result that worries me most in a foot and ankle practice is not the obviously low one — that patient gets referred and treated. It is the “normal” ABI in someone with diabetes, numb feet and a sore that has hung around for a month. Those arteries are often too stiff for the cuff to read, the nerves have taken away the pain that would have been the warning, and the number on the page says all is well. If that describes you or someone you care for, ask directly: “Have my toe pressures been checked?” It is a fair question, and a quick test.
What the ABI does not tell you
- Exactly where the narrowing is — that needs segmental pressures, ultrasound or other imaging.
- Anything about your veins. It is an arterial test. Swelling, varicose veins and clots are a different question and a different ultrasound.
- Anything about your nerves. Numbness and burning need sensory testing, which is a separate examination. Nerves or circulation? →
- Whether a wound will heal on its own — toe pressures and the clinical picture do more of that work.
Common questions
What is a normal ABI?
Between 1.00 and 1.40. A result of 0.91 to 0.99 is borderline, 0.90 or below is consistent with peripheral artery disease, and above 1.40 usually means the arteries are too stiff to compress, which needs a toe test rather than reassurance.
Can I do an ABI at home?
Not meaningfully. It needs a Doppler probe, correctly sized cuffs, a proper rest period and practiced technique, and it is a measurement where small errors change the category. A home blood pressure cuff on the ankle does not produce a valid ABI, and NICE warns that even automated clinic machines tend to overestimate the result, so disease can be missed. This is a short test in a clinic that has a manual Doppler.
Does it hurt?
No more than a blood pressure check. The cuffs squeeze briefly. If you have rest pain or a painful wound, mention it beforehand — the technician can adjust how the test is done.
My ABI was 1.5. Is that good?
It is not a good result — it usually means the ankle arteries are too stiff to compress properly, which is itself a marker of disease and is common with diabetes and kidney disease. A high ABI predicts heart and stroke risk just as a low one does — and is more strongly linked to stroke. It should lead to a toe pressure or toe-brachial index rather than to reassurance.
My ABI was normal but my calves still hurt when I walk. What now?
Ask whether an exercise ABI makes sense. Mild narrowing can leave resting pressures normal and only show up when the muscles are working. If the exercise test is also normal, the cause is more likely to be something else, such as spinal stenosis, and that changes who you should see next.
Is the ABI the same as a leg ultrasound?
No. The ABI measures pressures and gives a ratio; an arterial duplex ultrasound images the arteries and shows where and how severe a narrowing is. And a venous ultrasound, the test for clots and leaky valves, is a third, separate study.
How often should the ABI be repeated?
There is no fixed schedule. It is repeated when symptoms change, after a procedure on the leg arteries, or to follow a borderline result. A fall of more than 0.15 between tests suggests the disease has progressed. Because it is quick and non-invasive, comparing against your previous number is often more informative than any single reading.
Does Medicare cover an ABI?
For a reason, yes; as screening, no. In Michigan, Medicare’s contractor covers arterial studies for problems such as claudication, rest pain or a non-healing wound, generally no more than once a year. It does not cover screening people without symptoms, and it treats a simple ABI on its own as part of the physical examination rather than a separately billed test. Other plans vary, so ask before the appointment.
Can a podiatry office do this?
Many can, and some refer for formal vascular studies. Ask the specific practice what they have in-house before the visit rather than assuming either way — and ask whether they can measure toe pressures, which is the part that matters most if you have diabetes.
Where to go next
- PAD symptoms and warning signs
- Claudication: leg pain on walking that eases with rest
- Arterial and venous ultrasound
- What imaging adds after the pressures
- Why this test comes before compression
- Poor circulation in the legs and feet
- Near Howell or Bloomfield Township, Michigan: a foot and ankle evaluation (the author’s own practice)
Sources
- Gornik HL, et al. 2024 ACC/AHA/AACVPR/APMA/ABC/SCAI/SVM/SVN/SVS/SIR/VESS Guideline for the Management of Lower Extremity Peripheral Artery Disease. Circulation 2024;149:e1313–e1410.
- Gerhard-Herman MD, et al. 2016 AHA/ACC Guideline on the Management of Patients With Lower Extremity Peripheral Artery Disease.
- American Heart Association. Measurement and Interpretation of the Ankle-Brachial Index — Top Things to Know.
- US Preventive Services Task Force. Peripheral Artery Disease and CVD in Adults: Risk Assessment With the Ankle-Brachial Index (2018).
- National Heart, Lung, and Blood Institute. Peripheral Artery Disease — Diagnosis.
- Mayo Clinic. Ankle-brachial index.
- Cleveland Clinic. Ankle-Brachial Index (ABI).
- StatPearls. Ankle Brachial Index.
- National Institute for Health and Care Excellence. Peripheral arterial disease: diagnosis and management (CG147).
- National Institute for Health and Care Excellence. Automated ankle brachial pressure index measurement devices (HTG677).
- NHS. Leg ulcer — diagnosis.
- National Wound Care Strategy Programme. Leg Ulcer Recommendations Summary (2023).
- Society for Vascular Surgery. Critical analysis and limitations of the resting ankle-brachial index.
- Centers for Medicare & Medicaid Services. Local Coverage Determination L35761: Non-Invasive Peripheral Arterial Vascular Studies.
Written by Tom Biernacki, DPM, FACFAS. Published 20 September 2026. Updated 15 October 2026. General education, not medical advice. Interpretation of any result belongs with the clinician who knows your history.