Once a pressure test says something is wrong, the next question is where and how bad — and that needs a picture. There are four ways to make one, they are not interchangeable, and the differences come down to your kidneys, your implants and what the picture is for.
Imaging comes second
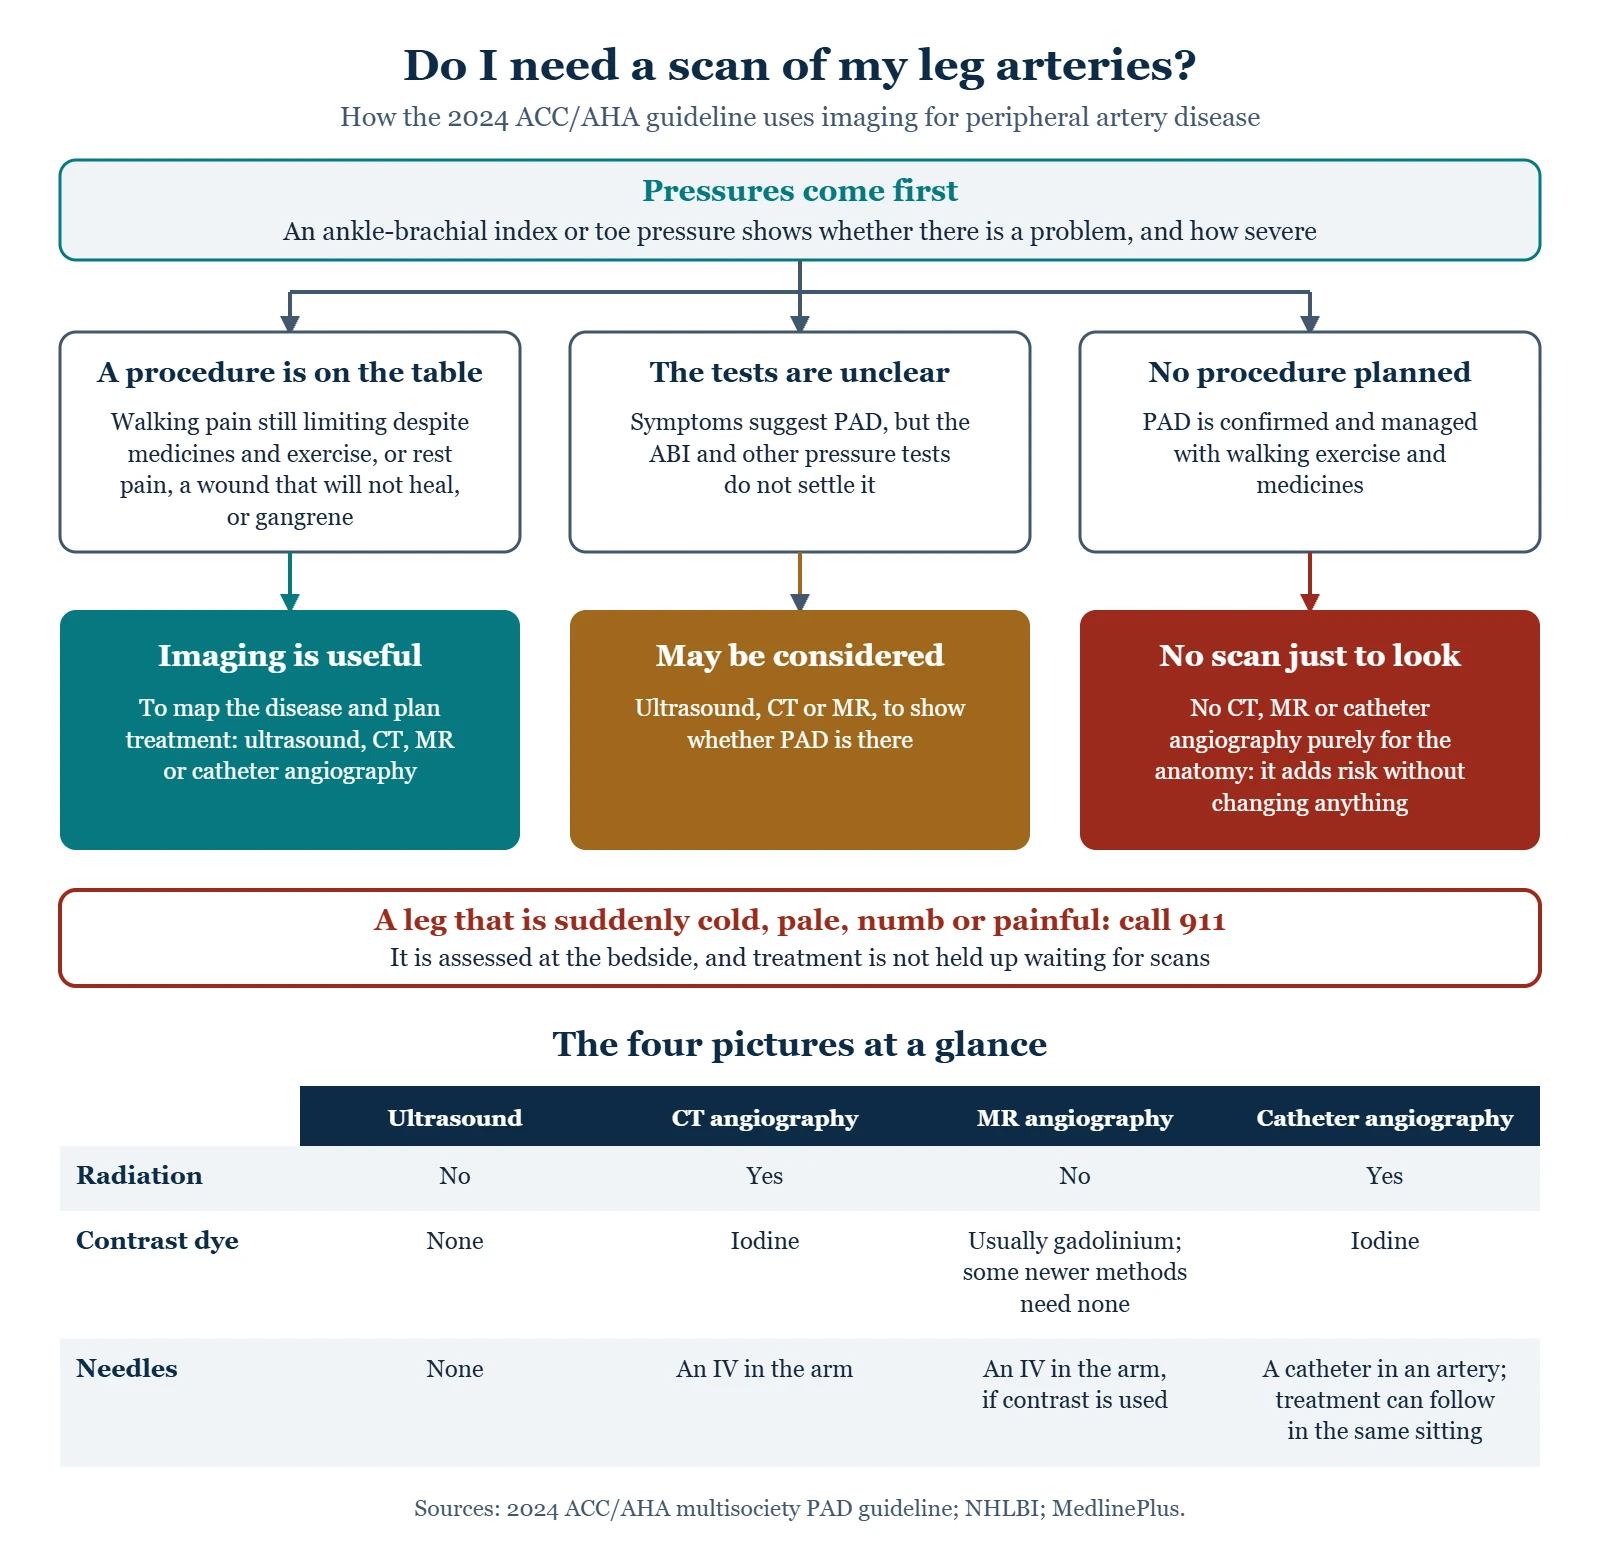
Pressures first, pictures after. An ankle-brachial index or toe pressure tells you whether there is a significant problem and roughly how severe. Imaging tells you where it sits and what could be done about it, which mainly matters once treatment is being considered. The 2024 American College of Cardiology and American Heart Association guideline is explicit: when PAD is confirmed and no procedure is being considered, CT, MR or catheter angiography should not be done just to look at the anatomy, because it adds risk without changing anything.
The four methods
| Method | What it is and what it does best | Limits and considerations |
|---|---|---|
| Duplex ultrasound | Sound waves showing both the vessel and the flow inside it. No radiation or contrast, so it can be repeated as often as needed: the usual starting point, the main test for veins, and the follow-up tool for grafts and stents | Depends heavily on the skill and time of the person scanning; body size, bowel gas and heavily calcified vessels can limit the view |
| CT angiography | An X-ray scan with iodine contrast injected into a vein. Fast, detailed arterial maps, including the pelvis and abdomen, often used to plan procedures | Uses radiation and iodine contrast, which can affect kidneys that are already impaired; heavily calcified small vessels can be harder to read |
| MR angiography | A magnetic scan, usually with gadolinium contrast. Detail without radiation, and newer techniques can image the leg and foot arteries without contrast at all | Some gadolinium agents are avoided in severe kidney disease because of a rare scarring condition; pacemakers, some implants and claustrophobia can be issues |
| Catheter angiography | A thin catheter in the artery with contrast injected directly. The clearest picture of small vessels, and treatment can happen in the same sitting | Invasive: a puncture site with a risk of bleeding and other access-site problems, plus radiation and contrast |
When imaging is actually recommended
- Claudication that still limits you despite medicines and structured exercise, when a procedure is being considered: ultrasound, CT, MR or catheter angiography is useful to map the disease and plan the approach.
- Limb-threatening disease — rest pain, a wound that will not heal, or gangrene: imaging is used to plan how blood flow can be restored. Rest pain and CLTI →
- An unclear diagnosis when the ABI and other pressure tests are inconclusive: noninvasive imaging may be considered to settle whether PAD is there.
- Confirmed PAD with no procedure planned: the guideline advises against CT, MR or catheter angiography purely for a look.
- A suddenly cold, painful, pale leg: this is assessed at the bedside and treated urgently, and the guideline is clear that scans should not delay it. When to seek care →
Catheter angiography
The oldest method gives the clearest picture of all, particularly in the small vessels below the knee, and its distinguishing feature is that treatment can happen in the same sitting — the balloon or stent goes in while the catheter is already there. Angioplasty, stents and bypass →
Because it is invasive, it is generally reserved for when treatment is expected rather than used purely to look. There is one interesting exception: in some people with advanced kidney disease, a targeted catheter angiogram can use less contrast than a CT scan would, so it may be chosen as the safer route when a procedure is planned anyway. If you are booked for one, it is reasonable to ask whether the plan is diagnosis, treatment, or both.
The kidney question
Iodine contrast for CT and catheter angiography can worsen kidney function in people whose kidneys are already impaired. This matters in vascular disease more than in most fields, because kidney disease and arterial disease travel together. It is managed rather than avoided — checking kidney function beforehand, using the smallest dose that answers the question, giving fluids, and reviewing medicines such as metformin around the scan — and for many people ultrasound or MR is chosen instead.
Tell whoever orders the scan if you have kidney disease, are on dialysis, have had a contrast reaction before, take metformin, or might be pregnant. None of those necessarily stops the test; all of them change how it is done.
What to expect
- Ultrasound. No preparation for leg arteries or veins; an abdominal or pelvic scan may ask you to fast. Warm gel, firm pressure from the probe, and a lot of quiet while the sonographer works. The pressure on a tender leg can be uncomfortable — say so. What the ultrasound looks for →
- CT angiography. You may be asked not to eat for a few hours. A cannula goes in the arm, and many people feel a warm flushing as the contrast goes in, sometimes as if they have wet themselves. They have not, and it passes in seconds.
- MR angiography. Remove everything metal, expect loud knocking noises and a narrow tube. Say in advance if you are claustrophobic — this is common and there are ways to manage it. Declare any implant, clip, pump or stimulator.
- Catheter angiography. Fasting, a puncture usually at the groin, local anesthetic and sedation, then lying flat for a period afterward while the site seals. Someone drives you home.
Afterward, ask when and how you will get the result, and who is responsible for acting on it. Scans sitting unread on a system is a real failure mode, and one phone call prevents it.
The report is yours
Ask for a copy, and ask for the images on a disc or portal link if a second opinion is likely. If you are ever told nothing can be done for your leg, having the imaging in hand is what makes a second opinion possible without repeating everything. If the wording is hard going, the plain-English glossary translates the common terms. Why that second opinion sometimes matters →
From the clinic
Before foot surgery in someone with poor circulation, imaging is what tells the team whether the blood supply can be improved first, and where. What I tell patients is that a scan earns its place when it will change what happens next. If you are booked for an angiogram, it is fair to ask whether it is to look, to treat, or both — and, if your kidneys are not perfect, what is being done to protect them.
Common questions
Which scan is best?
There is no single best. Ultrasound is the usual starting point because it is safe, repeatable and free of contrast. CT gives a fast, detailed map for planning. MR avoids radiation and, with newer techniques, sometimes contrast too. The right one depends on your kidneys, your implants, what part of the body is in question, and what the answer will be used for.
Is the contrast dangerous?
For most people it is well tolerated. The groups who need care are people with reduced kidney function, people who have reacted to contrast before, and — for some gadolinium agents used in MR — people with severe kidney disease. All are managed with precautions or by choosing a different test, which is why declaring them beforehand matters more than worrying about them.
Why does my report say the narrowing is worse than my symptoms suggest?
Images show anatomy; symptoms reflect function. A long-standing narrowing with good collateral vessels around it can cause remarkably little trouble, while a shorter one that developed quickly causes a lot. Treatment decisions are made on symptoms and pressures together with the pictures, not on the pictures alone.
Do I need imaging if my ABI is abnormal?
Not necessarily. If you have claudication being managed with exercise and medicines, an abnormal ABI does not by itself call for a scan, and the 2024 guideline advises against CT, MR or catheter angiography just to look when no procedure is being considered. Imaging is for when a procedure is on the table, when symptoms are severe or progressing, or when there is a wound or rest pain.
My leg went suddenly cold and painful. Should I wait for a scan?
No — call 911. A suddenly cold, pale, numb or painful leg is assessed at the bedside and treated urgently, and the guideline says scans should not delay that.
Where to go next
Sources
- Gornik HL, et al. 2024 ACC/AHA multisociety guideline for the management of lower extremity peripheral artery disease. Circulation 2024.
- National Heart, Lung, and Blood Institute. Peripheral Artery Disease — Diagnosis.
- MedlinePlus, National Library of Medicine. Angiography.
- National Institute of Diabetes and Digestive and Kidney Diseases. Chronic Kidney Disease.
- Society for Vascular Surgery. Peripheral Artery Disease.
Written by Tom Biernacki, DPM, FACFAS. Published 21 September 2026. Updated 16 October 2026. General education, not medical advice.