A wound on the foot or lower leg that has not closed is a circulation question before it is a dressing question. Poor arterial blood supply is a common, often missed reason a foot wound will not heal — and no dressing solves that, so it is ruled out first. On the lower leg, vein disease is the most common cause of ulcers; pressure and swelling that nobody has taken off are the other usual reasons.
Get seen today if
- There is new or spreading redness — and go to an emergency department now if it spreads fast or leaves a red streak, comes with a fever, chills or feeling unwell, or you have diabetes, numb feet or poor circulation; call 911 if you feel confused or very unwell
- The wound is getting bigger, more painful, wetter, or starting to smell
- There is a new dark patch on a toe, heel or the side of the foot that is still soft (black, gray or dark purple skin, or skin that looks dead, needs an emergency department now)
- You can see bone or tendon in the base of the wound
- You have diabetes and any new break in the skin of the foot — the threshold is lower, not higher
The rule of thumb
A break in the skin below the knee that has not closed in about two weeks, or that is getting worse at any point, should be assessed. Not re-dressed — assessed, with the circulation checked. Waiting to see whether it turns a corner is how small wounds become large ones. The NHS defines a leg ulcer as a sore that takes more than two weeks to heal, and clinicians call a wound chronic once repair has not restored the skin after about three months. If you have diabetes, the bar is lower still: NIDDK advises calling promptly about any foot sore that has not started to heal after a few days.
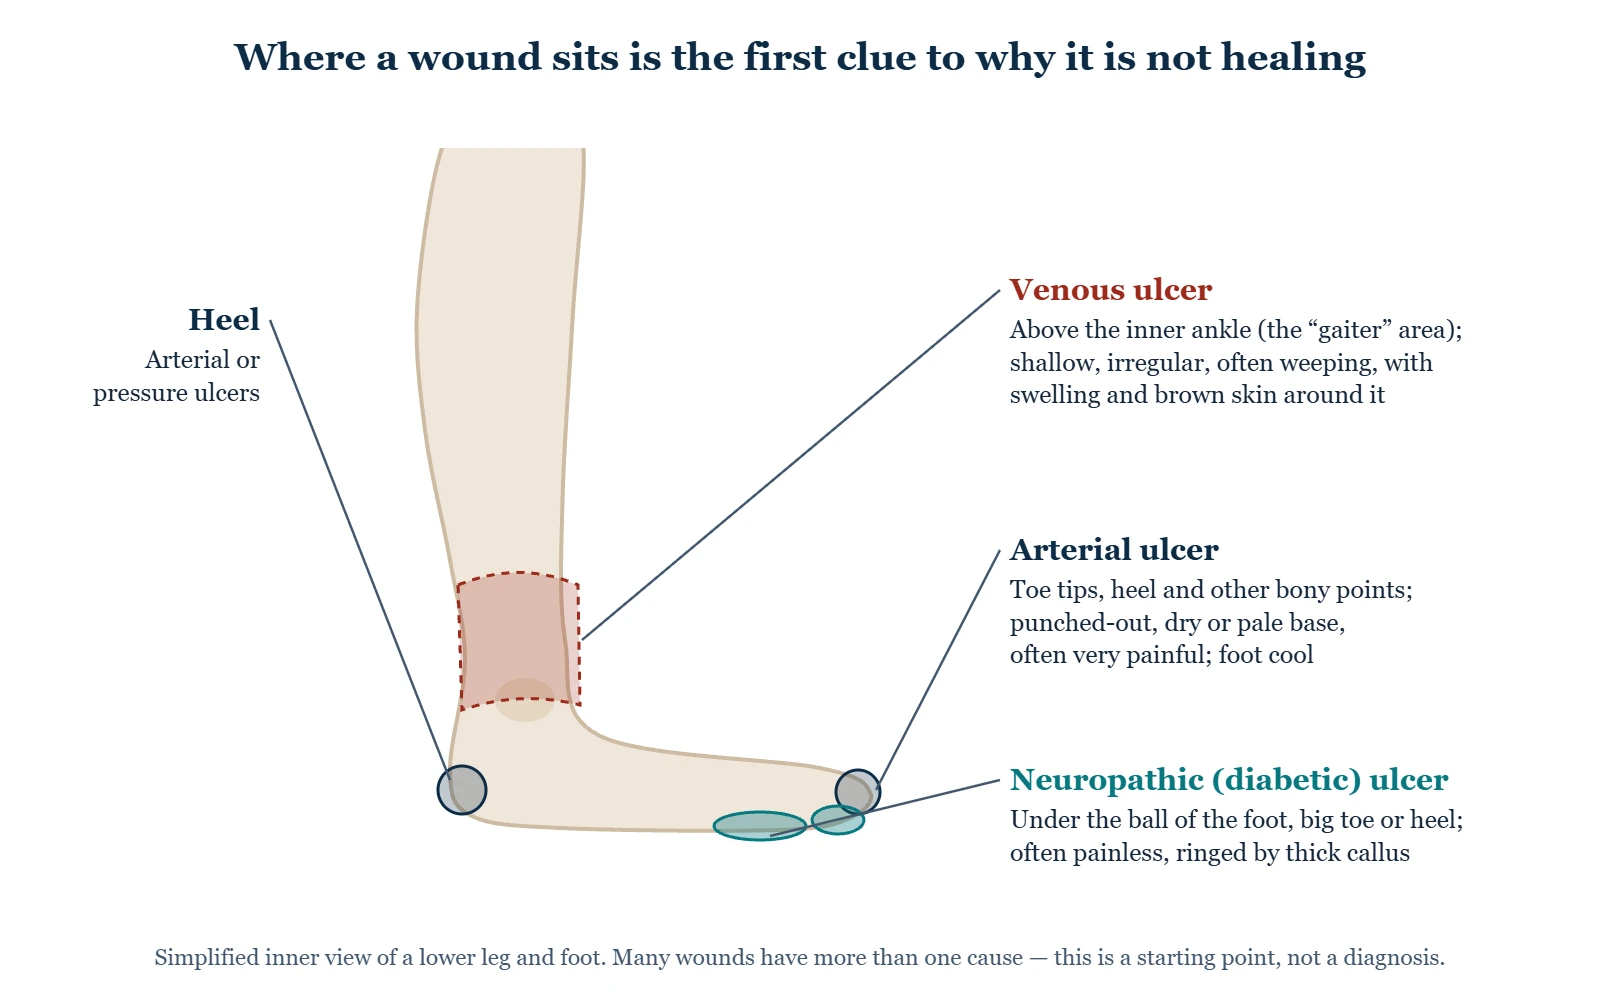
Why wounds stall
| Reason | What it looks like | What it needs |
|---|---|---|
| Not enough arterial blood | Toes, heel or bony points; dry, pale or black base; often very painful; cool foot, weak pulses | Arterial assessment, and often revascularization — healing depends on it |
| Venous pressure | Inner ankle; shallow, irregular, weeping; brown staining and swelling around it | Compression bandaging by a trained clinician, plus wound care |
| Pressure and no sensation | Under the ball of the foot, the heel, or the tip of a toe; often painless, with thick callus around it | Offloading — taking pressure off it — and footwear |
| Infection | Two or more of redness, warmth, swelling or hardness, and pain, or pus; redness is harder to see on brown or black skin | Antibiotics, sometimes surgical drainage; assessment for bone involvement |
| Lymphatic swelling | Firm swollen limb, skin folds, repeated cellulitis | Lymphedema management alongside wound care |
| Something else | Unusual appearance, unusual site, rolled or raised edges, not responding to correct treatment | Reassessment, sometimes biopsy — a small number are not ordinary wounds at all |
More than one is often true at once. A diabetic foot ulcer frequently combines pressure, no sensation, poor arterial supply and infection, and each element needs addressing.
The three common types, in more detail
Venous leg ulcers
Venous ulcers are the most common kind: more than 60% of leg ulcers, according to the NHS, and they affect 1 to 3% of Americans. They sit in the “gaiter” area above the ankle, usually on the inner side, and come with the signs of long-standing venous pressure: swelling, brown staining, itchy or eczema-like skin, and firm, tight tissue. They are usually less painful than they look and improve when the leg is raised. Compression is the treatment that heals them, applied by someone trained to do it once the arteries have been checked. With that care most heal within six months, but they come back in up to 70% of people, which is why compression stockings are advised indefinitely afterwards. Venous ulcers →
Arterial ulcers
Arterial ulcers appear where the blood supply is poorest and the skin is under pressure: the tips of the toes, between the toes, the heel, and over the ankle bones or shin. They often look “punched out”, with a pale, dry or dark base, and they hurt — typically worse at night and lying flat, better with the foot hanging down. The foot is often cool with weak or absent pulses. Restoring blood flow is usually what allows them to heal. Rest pain and threatened limbs →
Diabetic (neuropathic) foot ulcers
People with diabetes have a 19 to 34% lifetime risk of a foot ulcer, about half of people with a diabetic foot ulcer also have PAD, and foot ulcers come before up to 85% of diabetes-related amputations. They form under pressure points on the sole — the ball of the foot, the big toe, the heel — usually beneath a callus that has built up and broken down from the inside. Because nerve damage removes pain, many are discovered by sight or smell rather than feeling. The treatment that matters most is offloading: taking every bit of pressure off the wound for as long as it takes to close. For ulcers on the sole, the International Working Group on the Diabetic Foot prefers a knee-high device the patient cannot take off: a total contact cast, or a walking boot made non-removable.
The part most people are not told
Before anything else, the question is: is there enough blood supply for this to heal at all? Dressings, antibiotics and offloading all assume that the answer is yes. If it is no, the wound will not close however good the dressing, and the priority becomes restoring blood flow. That is why a non-healing wound below the knee should get an arterial assessment early rather than after several months of dressings. International diabetic foot guidelines advise urgent vascular imaging when the ankle pressure is below 50 mm Hg or the ABI below 0.4, and urgent assessment when the toe pressure is below 30 mm Hg. ABI and toe pressures →
What a proper assessment involves
- Arterial check — pulses, ABI, toe pressure, and imaging where needed.
- Wound assessment — site, size, depth, base, edges, discharge, whether it probes to bone.
- Sensation testing, because a painless wound tells you something important.
- Infection assessment, and X-ray or other imaging if bone involvement is a possibility.
- Cause-specific treatment: revascularization, compression, offloading, antibiotics, debridement — chosen by what the assessment found.
- Follow-up with measurement. A wound that is not substantially smaller after four weeks of correct treatment is a reason to re-examine the diagnosis, not to continue. For diabetic foot ulcers the international guidance is specific: if the ulcer has not shrunk by at least half within four weeks of proper care, the circulation should be reassessed.
What helps healing, beyond the wound itself
- Blood sugar control if you have diabetes — high glucose slows healing and feeds infection.
- Not smoking. Smoking is the strongest single driver of arterial disease, and in people with diabetic foot ulcers it predicts amputation and death.
- Enough protein and calories. Malnutrition stalls healing and should be treated, though vitamin and protein supplements have not been shown to speed the healing of diabetic foot ulcers.
- Swelling control — elevation for venous and lymphatic wounds, and compression once the arteries are confirmed adequate.
- The right footwear after healing. Diabetic foot ulcers come back often: about 4 in 10 within a year of healing, and roughly two-thirds within three to five years.
While you wait for the appointment
- Keep it clean and covered with a simple dressing.
- Keep weight off it if it is on the sole or a pressure point.
- Do not use corn or callus removers, strong antiseptics, or home remedies on an open wound.
- Do not apply compression that nobody has assessed you for.
- Do not soak it. Soaking softens and macerates the surrounding skin.
- Photograph it, with something for scale, so change is visible rather than remembered.
From the clinic
The wounds that do worst are not usually the frightening-looking ones. They are the small, painless holes under a callus on a diabetic foot that have been “kept an eye on” for six weeks with a bandage and a pair of ordinary shoes. Every step reopens them. If you take one thing from this page: a wound on the sole of a foot that cannot feel properly will not heal while you keep walking on it, and offloading is not optional.
Common questions
How long should a wound take to heal?
A simple break in the skin on a healthy leg generally shows clear progress within one to two weeks. Anything below the knee still open at two weeks, or open and not visibly improving, has earned an assessment. Chronic wounds are judged by whether they are measurably smaller over four weeks of correct treatment.
It does not hurt. Is that good?
No — and it is one of the more dangerous reassurances there is. A painless foot wound usually means reduced sensation, which means nothing will warn you if it gets worse. Painless wounds need more vigilance, not less.
Should I let it air out?
Generally no. Wounds heal better in a moist, covered environment than dried out under a scab, and covering protects from knocks and contamination. Which dressing suits depends on the wound, which is another reason to have it looked at.
Can I just get antibiotics?
Antibiotics treat infection. They do not treat poor blood supply, unrelieved pressure, or venous hypertension — and those are the more common reasons a wound stalls. Repeated antibiotic courses for a wound that keeps not healing is a sign the underlying cause has not been found.
Should I put hydrogen peroxide or iodine on it?
Not routinely. Strong antiseptics can damage the new tissue a wound is trying to build, and plain cleaning with water or saline is usually enough. If an antiseptic dressing is needed for infection, your clinician will choose one and tell you how long to use it. For diabetic foot ulcers, international guidelines specifically advise against antiseptic dressings as a way to speed healing.
Could a wound that will not heal be cancer?
Occasionally. Skin cancers can look like ulcers, and long-standing ulcers can rarely turn cancerous. A wound with raised or rolled edges, unusual growth or bleeding, or one that has not responded to months of correct treatment should be biopsied. American Family Physician guidance suggests biopsy for atypical wounds not healed after three to six months of standard care, and conditions such as pyoderma gangrenosum and vasculitis can also masquerade as ordinary ulcers. Cancer arising in an old wound, called a Marjolin ulcer, is rare and usually takes decades to develop.
I have diabetes. Is this different?
Yes, in urgency. Reduced sensation, reduced blood supply and higher infection risk often combine, and diabetic foot ulcers can deteriorate quickly and quietly. The American Diabetes Association says every foot ulcer should be seen by a doctor right away, and NIDDK advises calling promptly about any foot sore that has not started to heal after a few days.
Where to go next
- Lymphangitis: red streaks from an infected wound
- Gangrene: a wound with black or dead tissue
- The PAD guide — the most common reason wounds stall
- Venous leg ulcers
- Skin changes that precede venous ulcers
- ABI and toe pressures
- Daily checks that catch these early
- Near Howell or Bloomfield Township, Michigan: a foot and ankle evaluation (the author’s own practice)
- Arterial ulcers: how they look and how they heal
Sources
- NHS. Venous leg ulcer.
- NHS. Venous leg ulcer: treatment.
- American Family Physician. Chronic wounds: evaluation and management (2020).
- American Family Physician. Venous ulcers: diagnosis and treatment (2019).
- International Working Group on the Diabetic Foot. Practical guidelines on the prevention and management of diabetes-related foot disease (2023, PDF).
- International Working Group on the Diabetic Foot. Guideline on peripheral artery disease and diabetes-related foot ulcers (2023, PDF).
- International Working Group on the Diabetic Foot. Guideline on wound healing interventions (2023, PDF).
- International Working Group on the Diabetic Foot. Guideline on the prevention of foot ulcers (2023, PDF).
- NICE. Diabetic foot problems: prevention and management (NG19).
- StatPearls. Diabetic foot ulceration and complications.
- StatPearls. Marjolin ulcer.
- Mayo Clinic. Pyoderma gangrenosum.
- National Institute of Diabetes and Digestive and Kidney Diseases. Diabetes and foot problems.
- American Diabetes Association. Foot complications.
- Mayo Clinic. Cuts and scrapes: first aid.
- MedlinePlus. Surgical wound care: open.
Written by Tom Biernacki, DPM, FACFAS. Published 20 September 2026. Updated 15 October 2026. General education, not medical advice.