Itchy, dry, discolored skin around the ankles is one of the most frequently misdiagnosed things on the lower leg. It is regularly treated as an infection or an allergy when it is the skin’s response to sustained venous pressure — and the treatments for those are different. Get the label right and the plan becomes simple: lower the pressure, protect the skin, calm the flares.
When it is not just dermatitis
See someone promptly if there is spreading redness with fever or feeling unwell, increasing pain, pus or a bad smell, or a break in the skin that is getting larger. Infection can sit on top of stasis dermatitis, and it needs treating.
And if one leg has become newly swollen, red and painful over hours to days, that needs assessment today — both cellulitis and a clot look like that. More on DVT →
What it looks like
- Dry, scaly, itchy skin on the lower leg, usually worst just above the inner ankle
- Redness that is often on both legs — a useful clue, because cellulitis is almost always one leg
- Brown or rust-colored staining, from iron left behind by leaked red blood cells
- Weeping or crusting patches during a flare
- Ankle swelling that is worse by evening, and often varicose veins nearby
- Over time, skin that feels firm, tight and woody, sometimes narrowing the lower calf — called lipodermatosclerosis
- Small white, irregular scars ringed by tiny red dots (atrophie blanche), and eventually shallow ulcers, most often on the inner ankle
On white skin it looks red or brown; on brown or Black skin it can look dark brown, purple, grey or ashen, and it is easier to miss. The earliest staining can show as pinpoint rust-colored dots, which can look like the cayenne-pepper dots of capillaritis, a harmless capillary leak.
The mistake that matters
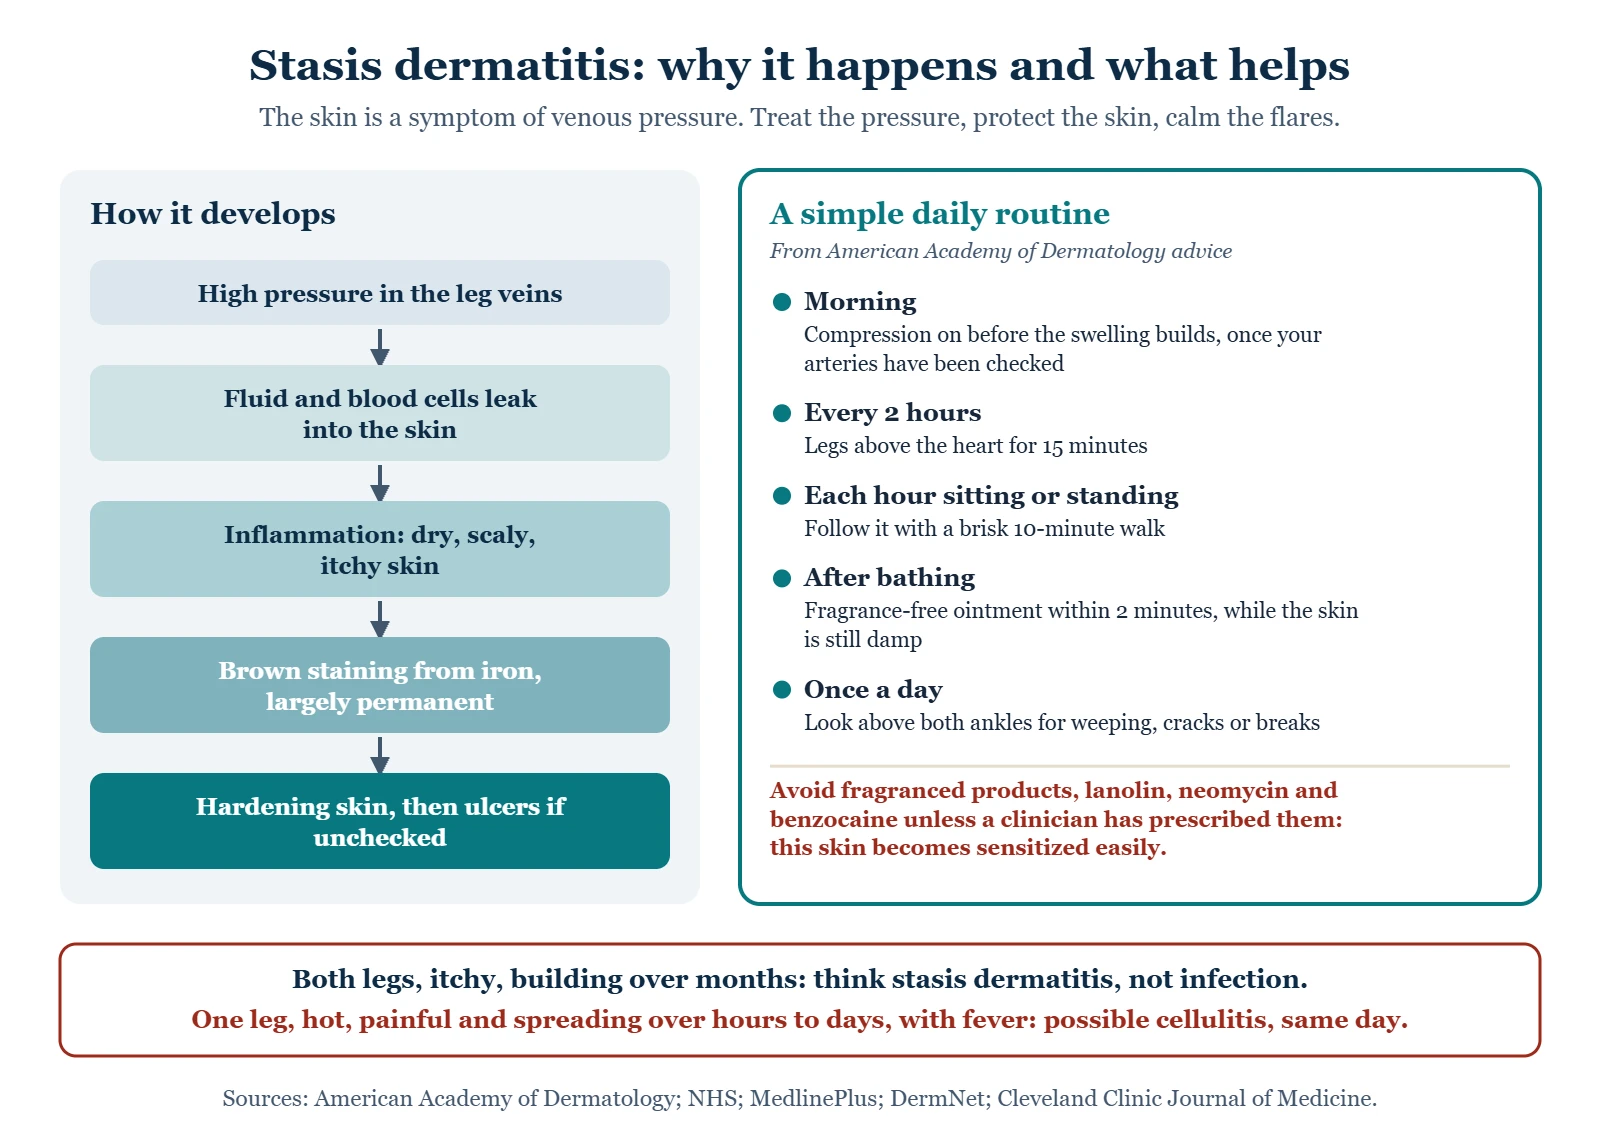
Stasis dermatitis on both legs is frequently treated as bilateral cellulitis and given repeated courses of antibiotics that do not help — because there is no infection to treat. Stasis dermatitis is the condition most often mistaken for cellulitis, and misdiagnosis is common: in one study of 259 patients diagnosed with leg cellulitis, 30% turned out not to have it, and almost all of them had been given antibiotics they did not need. Cellulitis is usually one-sided and spreads over hours to days; fever is common but can be absent. Chronic, itchy, symmetrical redness with brown staining and a long history is a different animal. It is a reasonable thing to raise if you have had several courses of antibiotics for legs that keep looking the same.
| Stasis dermatitis | Cellulitis | |
|---|---|---|
| Legs affected | Often both | Almost always one |
| Onset | Gradual, months to years, with flares | Over hours to a few days |
| Main symptom | Itch | Pain and tenderness |
| Fever, chills, feeling unwell | No | Often |
| Skin | Scaly, brown-stained, sometimes weeping | Hot, tight, spreading redness |
| Response to antibiotics | None | Improves within days |
How stasis dermatitis changes over time
Stasis dermatitis is also called venous eczema, varicose eczema, gravitational eczema or gravitational dermatitis, and some pages call it venous stasis dermatitis. The American Academy of Dermatology (AAD) describes how it tends to progress.
- Early. Swelling and faintly discolored skin, especially over varicose veins, are often the first signs. The swelling is often on the inside of the ankle and builds toward the end of the day; early on it tends to clear while you sleep and come back once you are up.
- Advancing. The swelling may no longer clear overnight, the skin can become sensitive to touch, and a lotion applied to the dry, itchy skin can burn and sting. Discolored, scaly skin can spread over much of the lower legs and the tops of the feet, and once it reaches the tops of the feet the AAD says wearing shoes can be painful even with treatment.
The AAD also says treatment can ease pain and discomfort at any stage but cannot cure stasis dermatitis, and that the earlier it is caught and treated, the better.
On brown and Black skin
The NHS notes that the redness of cellulitis may be less obvious on brown or Black skin, and the MSD Manual describes the skin over cellulitis as usually redder, or darker on dark skin. So do not rely on redness alone: the NHS also lists skin that is painful, hot and swollen, possible blistering, and feeling unwell. For stasis dermatitis itself, the NHS lists itchy, swollen, dry, flaky or scaly skin, and tender, tight skin that can eventually harden; none of those depends on color.
How fast to get it looked at
Itching and staining are a routine-appointment problem, but infection on top of stasis dermatitis is not. These tiers follow the site’s when-to-seek-care guide, with the NHS cellulitis advice added.
- Routine appointment: itching, dryness or brown staining of the skin around the ankles.
- The same day: a leg that is red, hot and swollen, which may be cellulitis and needs antibiotics promptly (go to an emergency department now if you feel unwell or have a fever or chills).
- The same day or the next: a break in the skin that has not closed or is getting bigger, wetter or more painful.
- Today: one leg newly swollen when the other is not, because a clot can look the same.
- Call 911: a wound with spreading redness plus fever, chills, confusion, a rapidly worsening appearance or a foul smell. The NHS emergency list for cellulitis also includes a fast heartbeat or fast breathing, feeling dizzy or faint, cold, clammy or pale skin, and purple patches, which may be less obvious on brown or Black skin.
If cellulitis is diagnosed, the NHS advice includes not wearing compression stockings until you are better, so ask the clinician when to restart.
Why it happens
Sustained high pressure in the lower leg veins pushes fluid and blood cells out into the tissue. The body’s response to that leakage is inflammation, and the skin sitting in an inflamed, fluid-logged environment becomes dry, fragile and itchy. Iron from broken-down red cells is what produces the brown staining, which is essentially permanent once established. Over years the inflammation lays down fibrous tissue and the skin hardens. It is common: the American Academy of Dermatology estimates that 15 to 20 million Americans over 50 have it, and more than 20% of people over 70. Risk rises with varicose veins, a past clot or cellulitis, heart failure, kidney disease, excess weight, inactivity and long hours standing or sitting.
In other words, the skin is a symptom. Treating the skin without addressing the pressure underneath it is a losing strategy. The venous insufficiency behind it →
How stasis dermatitis is diagnosed
The NHS says a doctor can often make the diagnosis simply by looking at the skin, and MedlinePlus says it is primarily based on how the skin looks. Because blood flow in the leg veins is the main cause, expect questions about varicose veins, a past clot (DVT), leg ulcers, cellulitis, and surgery or injury to the legs. Tests are added when the picture is unclear:
- Pulses and an ankle-brachial index (ABI). The NHS says a GP may check the pulses in your feet and compare ankle and arm blood pressures (the ankle brachial pressure index, ABPI) to see whether compression stockings are suitable. A significant difference suggests a problem with arterial flow, and then compression may not be safe. Compression safety covers who needs this check first.
- A leg ultrasound. The AAD says a Doppler ultrasound can rule out a blood clot and show damage to blood vessels.
- A patch test. The AAD says some patients need an allergy patch test to find out whether an allergic reaction is affecting the skin.
Stasis dermatitis can resemble cellulitis or contact dermatitis (AAD). DermNet lists stasis and contact eczema, fungal infection, a deep vein clot, lipodermatosclerosis and insect bites among the conditions often mistaken for cellulitis. If the usual treatment is not helping, the NHS says a GP may refer you to a dermatologist in case there is another cause or contact dermatitis.
What actually helps
- Address the venous pressure. Correctly fitted graduated compression, elevation above heart level, and walking. This is the part that changes the trajectory. It requires an arterial assessment first. Why →
- Moisturize consistently. Plain, fragrance-free emollients, applied generously and often. Dry skin cracks, and cracks become ulcers.
- Treat the inflammation during a flare. Topical steroids, prescribed for a defined period — often a stronger one until the patches flatten, then a milder one until the itch settles — calm the inflammation. Long, unsupervised use thins skin that is already fragile.
- Calm weeping patches with cool, wet compresses as your clinician directs, before going back to moisturizer and compression.
- Be careful what you put on it. Skin in this state becomes sensitised easily. When people with leg ulcers or stasis dermatitis are patch tested, a large share react to something — most often fragrance ingredients such as balsam of Peru, lanolin (wool alcohols) and the antibiotic neomycin. Choose fragrance-free products, and avoid over-the-counter antibiotic ointments, lanolin and numbing creams such as benzocaine unless a clinician has prescribed them. If a product makes things worse, stop it and say so.
- Do not scratch. Easier said than done, and the usual route from intact skin to an open ulcer. Treating the itch properly is the practical answer.
- Protect from knocks. A minor bump on this skin can open a wound that takes months.
A simple daily routine
Morning: compression on, before the swelling builds. Through the day: the American Academy of Dermatology suggests raising your legs above your heart for 15 minutes every two hours, and a brisk 10-minute walk after each hour of sitting or standing. After bathing: petroleum jelly or a fragrance-free ointment within two minutes, while the skin is still damp. Once a day: look at the skin above both ankles for new weeping, cracks or breaks. Boring, and it works.
From the clinic
A surprising number of the angriest-looking legs I see are not getting worse from the veins — they are reacting to what has been put on them. Triple-antibiotic ointments, fragranced lotions, “natural” creams with plant extracts and even some dressings can trigger an allergic rash on top of stasis dermatitis, and the result looks like the original problem flaring. When a leg refuses to settle, I strip the routine back to plain petroleum jelly or a fragrance-free emollient and compression, and see what is left.
Common questions
Will the brown staining go away?
Often not entirely. The pigment is iron deposited in the skin and it typically persists even when everything else improves. Treatment is aimed at stopping further damage and preventing ulceration; for the color itself, intense pulsed light treatment has cleared it in some patients.
Is it contagious?
No. It is a response to pressure and inflammation inside your own leg, not an infection, and nobody can catch it from you.
Can I just use a strong steroid cream?
Topical steroids have a real role in flares, prescribed and time-limited. Used continuously without supervision they thin skin that is already fragile, which makes ulceration more likely. And they do nothing about the venous pressure causing the problem, so the flares keep coming.
Should I put antibiotic ointment on it?
Generally no. There is usually no infection to treat, and MedlinePlus specifically advises avoiding topical antibiotics such as neomycin, which a notable share of people with this kind of skin turn out to be allergic to. If infection is suspected, it needs assessing and treating properly — with a prescribed antibiotic if one is needed — rather than with a tube from the pharmacy.
Why do both my legs look the same?
Because venous insufficiency is often bilateral — both legs have been standing in the same gravity for the same number of years. That symmetry is one of the features that distinguishes it from cellulitis.
Does this mean I will get an ulcer?
Not necessarily, but the skin changes are the stage before ulceration, and that is worth knowing rather than being told after the fact. Consistent compression and skin care are what lower the odds. If an ulcer does form, about 70% of people who keep up compression heal — and wearing stockings after healing roughly halves the chance of it coming back. Venous ulcers →
Can treating my veins clear it up?
Often it helps substantially. If an ultrasound shows a refluxing surface vein, closing it lowers the pressure in the lower leg, and the itching, flares and weeping tend to settle — though the brown staining usually remains. Compression and skin care still matter afterwards.
Is stasis dermatitis serious?
On its own it is an inflammatory skin reaction to pressure in the leg veins, not an infection, and it is not contagious. It is usually long-term, though the NHS says treatments help keep it under control. It becomes serious when it is left untreated: the NHS says leg ulcers can develop, and the AAD says cellulitis becomes more common as it worsens. Itching, dryness and brown staining call for a routine appointment; a red, hot, swollen leg or a break in the skin that is not closing needs to be seen the same day or the next.
How can you tell stasis dermatitis from cellulitis?
Stasis dermatitis is long-standing and usually affects both legs, with itchy, dry or scaly skin, brown staining and ankle swelling. Cellulitis is usually in one leg and rarely, if ever, in both, tends to come on over hours to days, and is painful, hot and swollen, sometimes blistered, often with feeling unwell, fever or chills. On brown and Black skin the redness of cellulitis can be less obvious, so go by the pain, heat and swelling. The two can occur together, because stasis dermatitis raises the risk of cellulitis. If you are not sure, or one leg has suddenly changed, be seen the same day.
What is the best cream for stasis dermatitis?
There is no single best cream. The usual pairing is a plain moisturizer every day plus a prescribed steroid cream in short courses when the skin is inflamed; the NHS lists emollients and topical corticosteroids, and American Family Physician describes daily emollients with short courses of topical steroids. DermNet lists avoiding soap, and using water alone or a non-soap cleanser when bathing, among the measures that reduce flare-ups. MedlinePlus says to talk to your provider before using any lotions, creams or antibiotic ointments, and to avoid topical antibiotics such as neomycin, drying lotions such as calamine, lanolin, and numbing products such as benzocaine. No cream treats the vein pressure underneath, which is why the plan also includes compression, after the arteries have been checked.
Where to go next
- Hemosiderin staining: brown skin on the lower legs, and whether it fades
- Red dots and purple spots on the lower legs
- Lipodermatosclerosis: when the skin above the ankle hardens
- The venous insufficiency it comes from
- Venous leg ulcers
- Daily skin and foot care
- Choosing compression socks
- A wound that will not heal
- Red, blue, pale or purple feet
- Weeping legs: when swollen legs leak fluid
- Compression safety: who needs an assessment first
- Varicose veins: symptoms and treatment choices
- When to seek care
Sources
- American Academy of Dermatology. Stasis dermatitis: overview.
- American Academy of Dermatology. Stasis dermatitis: who gets it and causes.
- American Academy of Dermatology. Stasis dermatitis: diagnosis and treatment.
- American Academy of Dermatology. Stasis dermatitis: self-care.
- DermNet. Venous eczema.
- NHS. Varicose eczema.
- MedlinePlus. Stasis dermatitis and ulcers.
- Cleveland Clinic. Venous stasis dermatitis.
- National Eczema Association. Stasis dermatitis.
- Yosipovitch G, et al. Stasis Dermatitis: An Overview of Its Clinical Presentation, Pathogenesis, and Management. Am J Clin Dermatol 2023.
- Keller EC, et al. Distinguishing cellulitis from its mimics. Cleve Clin J Med 2012.
- Weng QY, et al. Costs and Consequences Associated With Misdiagnosed Lower Extremity Cellulitis. JAMA Dermatol 2017.
- Geier J, et al. Contact sensitization in patients with chronic leg ulcers or stasis dermatitis (IVDK). Contact Dermatitis 2017.
- Society for Vascular Surgery. Chronic Venous Insufficiency.
- NHS. Leg ulcer.
- StatPearls, NCBI Bookshelf. Cellulitis.
- American Family Physician (Trayes, Studdiford, Pickle and Tully, 2013). Edema: Diagnosis and Management.
- MSD Manual Professional Version. Edema.
Written by Tom Biernacki, DPM, FACFAS. Published 20 September 2026. Updated 18 October 2026. General education, not medical advice.