Rest pain is the point at which arterial disease stops being an inconvenience on walks and becomes a threat to the limb. It has a distinctive story, it is often mistaken for arthritis or neuropathy for months, and the delay is the part that costs people toes and feet.
This is not a wait-and-see page
Call 911 if a foot or leg becomes suddenly cold, pale or mottled, numb, weak or severely painful over minutes to hours. That is an abrupt blockage, and permanent damage can happen within four to six hours.
Get seen the same day for pain in the forefoot or toes that comes on lying down, wakes you at night, and eases when you hang the foot over the side of the bed — especially alongside a wound that will not heal, or a new dark area on a toe or heel. A toe or patch of skin that has turned black, gray or dark purple, or looks dead, needs an emergency department now. The Society for Vascular Surgery advises urgent referral to a vascular surgeon for exactly this. Ask specifically for an arterial assessment and say that you have night pain relieved by dangling the foot.
What rest pain actually feels like
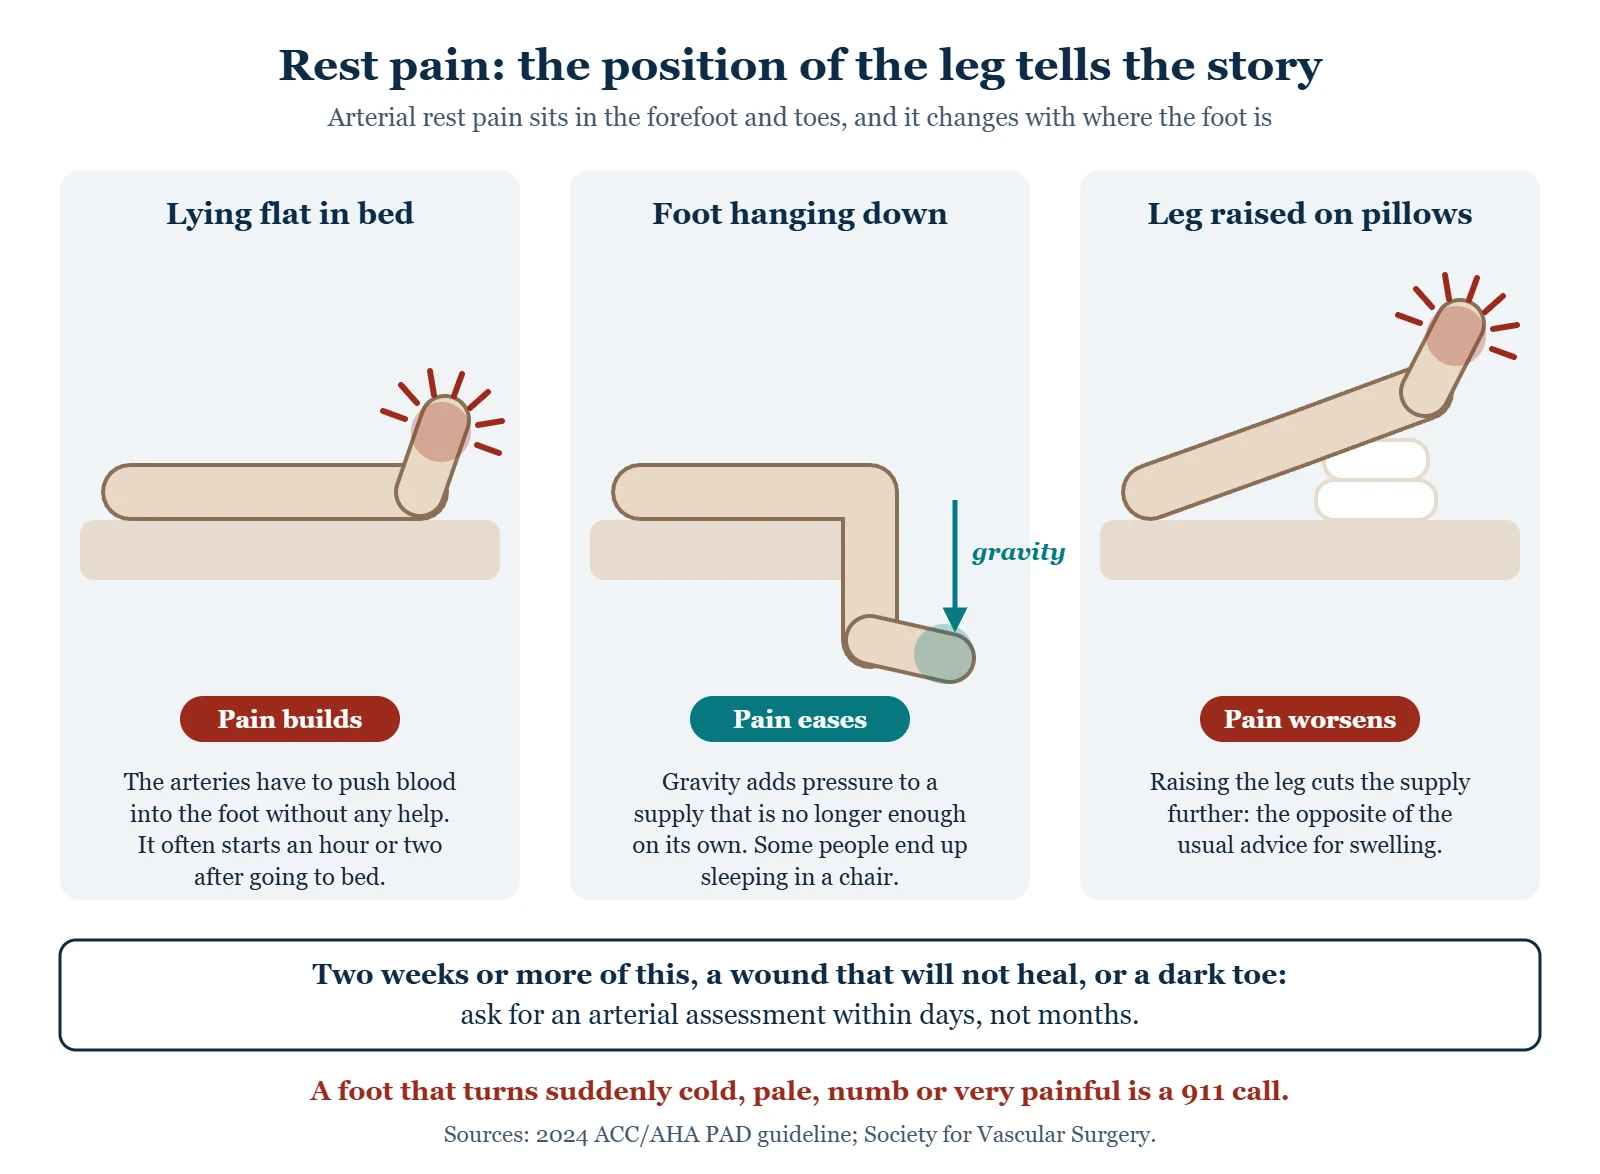
It sits in the forefoot and toes rather than the calf. It is a deep, burning, relentless ache rather than a cramp. It arrives when the leg is horizontal — typically an hour or two after going to bed — and it is relieved, partly or completely, by lowering the foot. People describe sleeping in a recliner, sitting on the edge of the bed with one leg down, or getting up and walking a few steps to settle it.
The reason is gravity. When the leg lies flat, the arteries have to push blood into the foot without help. When the foot hangs down, gravity adds pressure to a supply that is no longer adequate on its own. Anything that relieves foot pain by lowering the leg is an arterial story until proven otherwise.
Why it gets missed
Night-time foot pain has several common explanations that are all more likely in the general population — neuropathy, cramps, arthritis, plantar fasciitis. Rest pain is rarer, and it can appear in someone who never had classic claudication, because people who cannot walk far for other reasons never reach the distance that would have produced it. Diabetes complicates it further: damaged nerves can blunt the pain, so the first sign is sometimes a wound rather than a symptom. About half of people with limb-threatening disease have diabetes.
The detail that separates it from the others is the position. Neuropathy and cramps ease with getting up and moving. Rest pain eases with the foot hanging down and returns when it is raised.
Chronic limb-threatening ischemia
Chronic limb-threatening ischemia, or CLTI, is the term for the advanced stage of peripheral artery disease. The 2024 American College of Cardiology and American Heart Association guideline uses it when someone has objectively confirmed arterial disease together with rest pain, a wound on the foot or leg that is not healing, or tissue that has died, lasting more than two weeks. It estimates that CLTI develops in 11 to 20% of people with known PAD.
It is called limb-threatening because that is the accurate description. Historically, up to 30% of people with CLTI needed an amputation within a year, and 25 to 35% died. In a review of people with CLTI whose blood flow was not restored, 22% had a major amputation and 22% died over a median of about a year. Treated, most limbs are salvageable — and the difference between those outcomes is very largely a matter of how quickly the arterial supply is assessed and restored. CLTI also signals arterial disease throughout the body, so heart attack and stroke risk are high at the same time, and managing that is part of the treatment rather than an afterthought.
How it is assessed
| Step | What it adds |
|---|---|
| Examination and pulses | Where the disease is, what the skin and any wound look like, whether there is infection |
| Ankle-brachial index | A first objective measure. Can be falsely normal or high when the ankle arteries are stiff, which is common in diabetes and kidney disease — nearly a quarter of people with CLTI have an ABI in the normal range |
| Toe pressure and toe-brachial index | More reliable than the ankle in those situations, and the usual way CLTI is confirmed. A toe pressure under 30 mm Hg signals severe ischemia |
| Skin perfusion or transcutaneous oxygen measurement | Whether a specific wound has enough blood supply to heal |
| Duplex ultrasound, CT or MR angiography | A map of where the blockages are, used to plan treatment |
| Wound assessment and infection control | Runs in parallel, not after. Infection in a poorly supplied foot escalates quickly |
What treatment involves
The central question is whether blood flow can be restored. The guideline says everyone with CLTI should be assessed for revascularization, and recommends it to limit tissue loss, heal wounds, relieve pain and keep a functional limb. That is done either from inside the vessel — balloon angioplasty, sometimes with a stent — or by bypassing the blocked segment with a graft, usually a vein from the same person. Which approach is chosen depends on where the disease sits, how long the blocked segment is, what vein is available, and the person going through it. In the BEST-CLI trial of 1,830 patients, people with a usable great saphenous vein did better with bypass, with 32% fewer major limb events or deaths and 27% fewer above-ankle amputations; for those without one, the two approaches were similar. The treatment map →
Restoring flow is one half. The other half runs at the same time: treating any infection, debriding and dressing the wound, offloading pressure from it, controlling blood sugar, and starting or optimizing the medicines that protect arteries everywhere — a statin, antiplatelet treatment, and blood pressure control. The guideline notes that CLTI care works best when delivered by a multispecialty team, and the American Heart Association names podiatrists as key members of it. Stopping smoking matters enormously: smokers with PAD progress to limb-threatening disease and amputation more often. Why it matters this much →
Three things that make rest pain worse
Elevating the leg. This is the opposite of the advice for swelling, and it is one of the few places on this site where the two conditions point in opposite directions. Raising a leg with inadequate arterial supply reduces it further. If elevation makes the pain worse, that is information — take it to the appointment.
Compression stockings. Compression is for the venous system. On a leg with severe arterial disease it can reduce an already marginal supply. Arterial assessment comes before compression, always. The safety check →
Heat. Heating pads, hot water bottles and hot soaks burn feet with reduced sensation and poor blood supply, and those burns become the wound that starts everything. Warm socks are the safe answer.
What to say at the appointment
- Lead with the position. Pain in the front of the foot that comes on lying flat and is relieved by hanging the leg down. That sentence is the one that gets the right test ordered.
- Say how long. Two weeks or more of it changes the category.
- Mention any wound, however small, including between the toes and on the heel, and how long it has been there.
- Ask for an arterial assessment — ankle-brachial index and, if you have diabetes or kidney disease, toe pressures.
- Bring your medicine list and your smoking history. Both change what happens next.
- Ask directly what the plan is if the test is abnormal, and how soon. Vagueness at this stage is worth pushing back on.
From the clinic
The phrase that makes me stop and examine a foot properly is “I have to hang it off the bed to get to sleep”. People offer it almost as an aside, often after months of being treated for neuropathy or arthritis. If that is you, say it first, and do not let a trim, a callus treatment or foot surgery happen on that foot until the circulation has been checked.
Common questions
How is rest pain different from night cramps?
Cramps are a sudden, visible tightening of the calf muscle that lasts seconds to minutes and is relieved by stretching or standing. Rest pain is a continuous burning ache in the forefoot and toes that lasts as long as the leg is flat and is relieved by lowering it. They feel different, sit in different places, and respond to different things.
I never had leg pain on walking. Can I still have this?
Yes, and it is more common than people expect. Claudication only shows up if you regularly walk far enough to produce it. Someone limited by arthritis, breathing problems, or simply not walking much can progress to rest pain without ever having had a warning symptom. Diabetic nerve damage can also mute the earlier stages.
Does rest pain always mean amputation?
No. Most limbs affected by chronic limb-threatening ischemia can be saved when the blood supply is restored and any wound is treated properly, and the great majority of people keep their leg. What drives the bad outcomes is delay, untreated infection, and continued smoking — not the diagnosis itself.
Should I be walking?
Structured walking is excellent treatment for stable claudication, and it is not the treatment for rest pain, an open wound, or a sudden change. At this stage the priority is assessment and restoring flow. Walking programs come back into the picture afterward. The distinction in full →
My ankle-brachial index was normal but the pain fits. What now?
A normal or high ABI does not rule out significant disease when the ankle arteries are calcified and will not compress, which is common with diabetes and kidney disease; in the guideline’s data, nearly a quarter of people with CLTI had an ABI in the normal range. Ask for toe pressures or a toe-brachial index, which use a vessel that is far less affected. If the story fits, do not accept a normal ABI as the end of the conversation.
Who should I see for rest pain?
Start with whoever can see you soonest and say the key sentence about night pain relieved by hanging the foot down. The Society for Vascular Surgery advises urgent referral to a vascular surgeon for rest pain or a foot sore that will not heal, and the best results come from a team that includes vascular, wound and foot care, including a podiatrist.
Where to go next
- Night cramps or rest pain? Telling them apart
- Night leg cramps or rest pain?
- Buerger’s disease: rest pain and toe sores in younger adults who smoke
- Gangrene: dry and wet gangrene of the toes, and what happens next
- Leg pain at night: telling the common causes apart
- PAD treatment: medicines, exercise and procedures
- A wound that will not heal
- PAD symptoms and warning signs
- When to seek care
- Living with PAD after a procedure
- Arterial ulcers: how they look and how they heal
- Cold feet at night: why your body is warm but your feet are not
Sources
- Gornik HL, et al. 2024 ACC/AHA multisociety guideline for the management of lower extremity peripheral artery disease. Circulation 2024.
- American College of Cardiology. 2024 guideline for lower extremity PAD: key points.
- American Heart Association. 2024 PAD guideline: top things to know.
- National Heart, Lung, and Blood Institute. Peripheral Artery Disease — Treatment.
- Society for Vascular Surgery. Critical Limb Ischemia.
- Society for Vascular Surgery. Peripheral artery disease.
- Society for Vascular Surgery. Acute Limb Ischemia.
- Society for Vascular Surgery. BEST-CLI: patients with good veins should consider surgery.
- Cleveland Clinic. Acute limb ischemia.
- StatPearls. Peripheral arterial disease.
- American Diabetes Association. Foot complications.
- National Institute of Diabetes and Digestive and Kidney Diseases. Diabetes and Foot Problems.
Written by Tom Biernacki, DPM, FACFAS. Published 21 September 2026. Updated 15 October 2026. General education, not medical advice.