Walking is one of the few things that genuinely improves how far someone with claudication can walk. But the instruction that works is specific — walk until it hurts moderately, rest, repeat — and applying it to the wrong person is how people get hurt. This page explains the program, the evidence behind it, and who should not start it yet.
This page is for stable, diagnosed claudication only
Do not follow a walk-into-discomfort program if you have any of the following. Each needs assessment first, and for some of them walking through pain is actively harmful.
- A wound, ulcer, blister or break in the skin on the foot or leg
- Pain in the foot at rest, or pain that wakes you at night
- A sudden change in symptoms, or a walking distance that has collapsed recently
- No diagnosis yet — leg pain on walking has several causes and they are not all arterial
- Reduced sensation in the feet, until someone has checked how you should be protecting them
- Chest pain, breathlessness or dizziness on exertion — your heart needs checking before an exercise program
Why walking works
It is not that the blocked artery opens. Improvement comes from a combination of things: small collateral vessels around the blockage may develop, the muscle becomes more efficient at using the oxygen it does receive, walking mechanics improve, and — not trivially — confidence returns, so people stop unconsciously shrinking their world.
The evidence is strong. A Cochrane review of 32 trials with 1,835 people found that exercise programs added on average about 82 meters of pain-free walking and 120 meters of maximum walking distance, with benefit still seen up to two years later. The same review found no change in the ankle-brachial index, which fits: the gains are in how the leg works, not in the artery itself. The 2024 American College of Cardiology and American Heart Association guideline gives supervised exercise therapy, or a structured community-based program with behavior-change support, its strongest level of recommendation.
What a structured program looks like
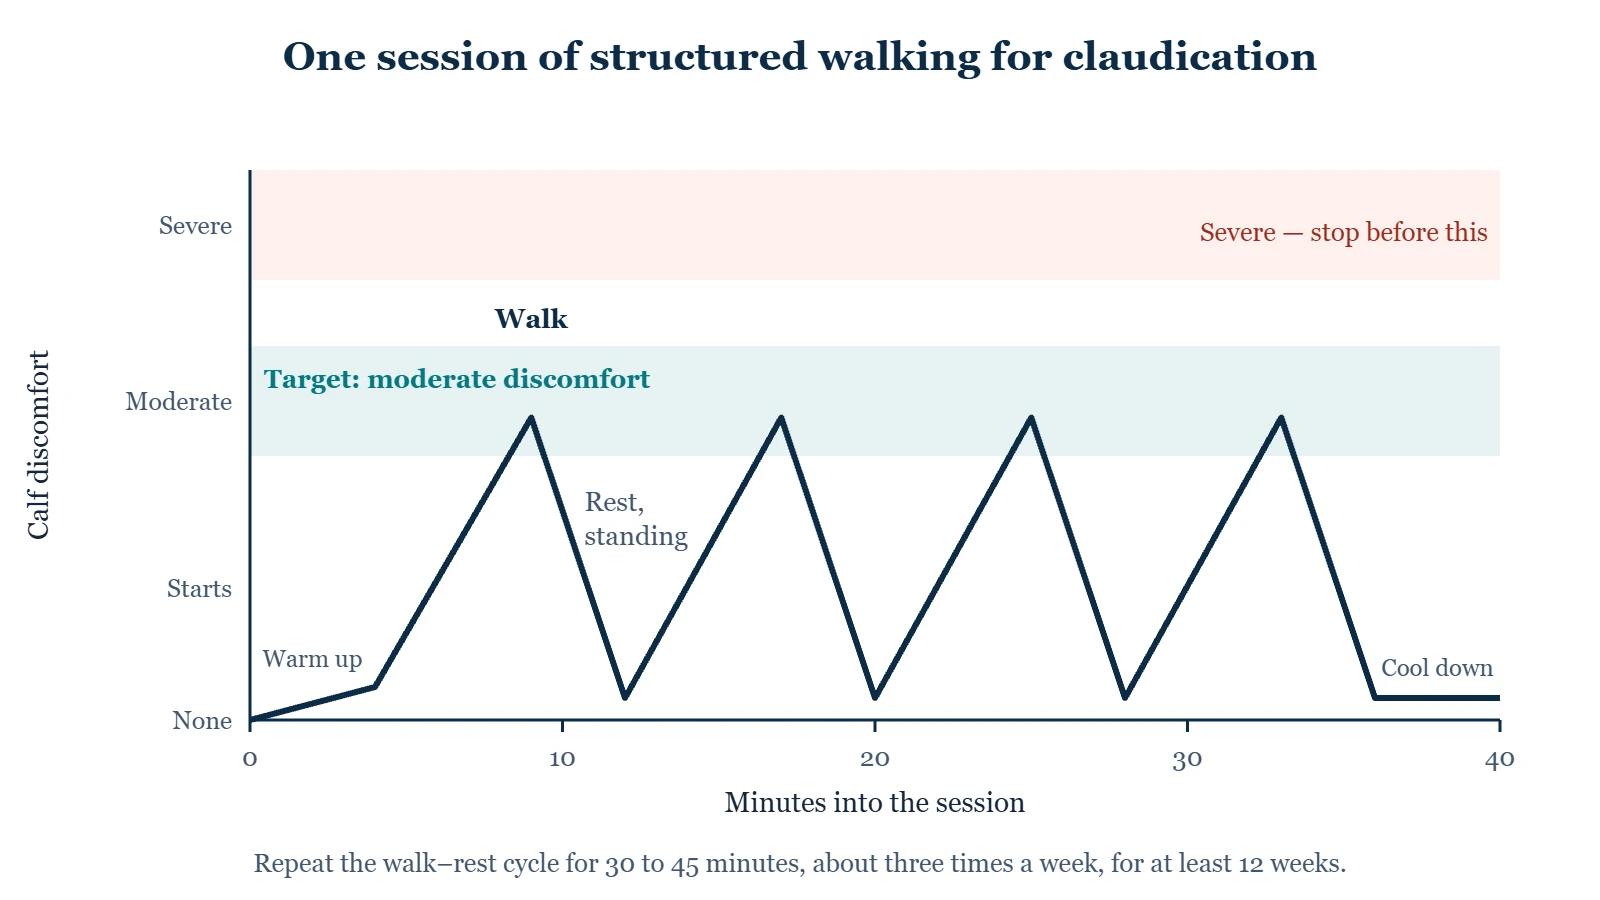
- Warm up with a few minutes of easy walking.
- Walk until the claudication discomfort is moderate — present and unmistakable, but not severe. This usually takes a few minutes.
- Stop and rest standing until the discomfort settles, typically two to five minutes. Sitting is not necessary.
- Repeat the walk-rest cycle to fill the session, commonly 30 to 45 minutes of total time including rests.
- Three sessions a week, for at least twelve weeks, is the shape most programs use.
- Cool down with easy walking.
“Walking to discomfort” is the part people get wrong
The target is moderate claudication discomfort, not severe pain, and certainly not pushing through a new or different pain. If a walk produces pain in the foot rather than the calf, or pain that does not settle within a few minutes of stopping, or any pain accompanied by color change, that is not the program working. Stop and report it.
Why the discomfort matters
It is tempting to walk only as far as is comfortable. The LITE trial tested exactly that. Among 305 people with PAD walking at home five days a week, those who walked at a pace that brought on moderate-to-severe leg symptoms improved their six-minute walk by about 35 meters at a year, while those who walked at a comfortable pace did no better than people who did not exercise. The guideline accordingly rates walking that avoids moderate-to-severe symptoms as of uncertain benefit, although some supervised treadmill studies found that walking only to the onset of discomfort also helped. The ischemic discomfort is, in effect, the training signal. That is also why the program needs a confirmed diagnosis first: the same instruction given to someone with a wound or rest pain would be harmful.
Supervised or at home?
| Supervised exercise therapy | Structured home program | |
|---|---|---|
| Where | Hospital or clinic exercise unit, usually on a treadmill | Your own routes, with instruction and a log |
| Who guides it | Trained staff present at each session | Periodic check-ins with a clinician or coach |
| Evidence | Strongest; the guideline’s top recommendation | Can work when structured, with coaching and a log; the guideline rates unstructured advice to walk more as uncertain |
| Coverage | Medicare covers up to 36 sessions over 12 weeks with a referral; other plans vary | Usually no cost beyond visits |
| Best for | Getting started safely, building confidence, measurable progress | People who cannot attend sessions, and long-term maintenance |
Ask your clinician for a referral by name — supervised exercise therapy for PAD. Not every practice offers it, so it is worth asking directly.
Making it stick
- Keep a simple log — distance or time to onset of discomfort, and total session time. Progress in claudication is slow enough to be invisible without a record, which is the usual reason people quit.
- Same route, so the distance means something. A known route turns a vague sense of “about the same” into a measurement.
- Flat ground to begin with. Hills and speed both bring symptoms on sooner.
- Check your feet before and after. More walking means more chance of a blister, and in a foot with reduced blood supply a blister is not a small thing.
- Shoes that fit, with room over the toes. Feet swell as the day goes on.
- Use a cane or walker if you need one. There is no prize for managing without, and it can be what makes the program possible.
What to expect
Benefit builds over weeks rather than days, and most programs are evaluated at around twelve weeks. Gains fade if the walking stops, so this is an ongoing habit rather than a course of treatment. Exercise improves walking distance; it does not replace the medicines aimed at reducing heart attack and stroke risk, which continue regardless. The rest of PAD treatment →
If walking is not possible
Walking is the best-studied option, but it is not the only one. The guideline rates other structured exercise, such as arm-cranking (arm ergometry) or cycling, as a reasonable alternative, noting growing evidence that these improve walking performance and quality of life much as treadmill programs do. A Cochrane review reached a similar conclusion, though the evidence is low certainty. If arthritis, balance or another condition makes walking programs impractical, say so rather than skipping exercise altogether — there is usually a version that works.
From the clinic
The patients who get the most out of this are the ones who treat it like a prescription with a dose: three sessions, written in the calendar, logged. The ones who get the least were told to “walk more” and quietly stopped at the first twinge, because nobody told them the twinge was the point. If that is you, it is worth starting again properly — with a referral, a log and a twelve-week horizon.
Common questions
Is it safe to walk into pain?
For stable, diagnosed claudication, walking to moderate discomfort is the established approach: it is how the programs that showed benefit were run, and in the LITE trial the pace that brought on leg symptoms improved walking while a comfortable pace did not. Report pain that carries on at rest, pain in the foot rather than the calf, or chest pain. For anyone with a wound, rest pain, an undiagnosed leg, or a recent change, it is the wrong instruction. The distinction is the diagnosis, which is why this page starts with it.
Does Medicare cover supervised exercise for PAD?
Yes. Since 2017, Medicare has covered supervised exercise therapy for people with claudication from PAD: up to 36 sessions over 12 weeks, each 30 to 60 minutes, in a hospital outpatient department or a physician’s office. You need a referral from the clinician treating your PAD after a face-to-face visit, and Medicare contractors can approve up to 36 more sessions. Coverage under other plans varies, so ask.
Can I use a treadmill or a bike instead?
Treadmill walking is what most supervised programs use and is entirely reasonable. Cycling, arm-cranking and strength training are reasonable alternatives that appear to improve walking about as much, though the trials are small. Walking remains the best-studied option, so the alternatives make most sense when walking itself is the obstacle, and any of them beats doing nothing.
How long before I notice a difference?
Weeks rather than days. Programs are usually judged at around twelve weeks, and in the trials the benefit was still seen up to two years later. This is precisely why the log matters — without one, slow improvement feels like no improvement.
Is walking better than a stent?
For walking distance in stable claudication, supervised exercise performs well and carries no procedural risk, which is why guidelines put it first. A procedure may be considered if symptoms still limit daily life after a proper trial of exercise and medicines, or if the limb is threatened. Exercise still matters after a procedure: the guideline also recommends supervised exercise after revascularization to improve walking and quality of life.
Should I stop if my ankle or knee hurts?
Joint pain is a different problem from claudication and is not something to push through. Report it — the program can usually be adjusted rather than abandoned.
Can I do this without seeing anyone first?
We would not recommend it. The first question is whether your leg pain is arterial at all, and the second is whether your feet are safe to be walking more on. Both are quick to answer and neither can be answered at home.
Where to go next
Sources
- Gornik HL, et al. 2024 ACC/AHA multisociety guideline for the management of lower extremity peripheral artery disease. Circulation 2024.
- American College of Cardiology. 2024 guideline for lower extremity PAD: key points.
- Cochrane. Exercise for intermittent claudication.
- Cochrane. Supervised exercise therapy versus home-based exercise or walking advice for intermittent claudication.
- Cochrane. Alternative exercise modes for intermittent claudication.
- LITE randomized clinical trial. Low- vs high-intensity home-based walking exercise in peripheral artery disease. JAMA 2021.
- American College of Cardiology journal scan. GOALS: home-based walking exercise intervention in PAD.
- Centers for Medicare & Medicaid Services. Supervised exercise therapy for symptomatic PAD (NCD 20.35).
- Centers for Medicare & Medicaid Services. MLN Matters MM10295: supervised exercise therapy for symptomatic PAD.
- National Heart, Lung, and Blood Institute. Peripheral artery disease: treatment.
- StatPearls. Peripheral arterial disease.
- NICE. Peripheral arterial disease: diagnosis and management (CG147).
- NHS. Peripheral arterial disease: treatment.
- MedlinePlus. Peripheral artery disease: legs.
Written by Tom Biernacki, DPM, FACFAS. Published 20 September 2026. Updated 15 October 2026. General education, not medical advice. Exercise programs for PAD should be set up with your clinician.