Peripheral artery disease is driven by the same plaque process that narrows the heart and neck arteries. That is the important framing: the risk factors for PAD are the risk factors for heart attack and stroke, and treating them is treating all three at once.
The 2024 American College of Cardiology and American Heart Association guideline estimates that 10 to 12 million Americans over 40 have PAD. Awareness is poor: in one US survey cited by the American Heart Association, only about 1 in 4 adults with risk factors and walking problems had even heard of it.
The factors you can change
Smoking
The single strongest modifiable risk factor for PAD, raising the risk about four-fold. It accelerates plaque formation and constricts vessels directly, and in people who already have PAD, continuing to smoke is linked to more heart attacks, strokes and limb events. Stopping has a larger effect on the course of PAD than anything else available, but the risk falls slowly: the guideline notes that former smokers’ risk stays more than double a never-smoker’s for 10 to 20 years. In Cleveland Clinic’s figures, about 86 in 100 people who quit after a PAD diagnosis are alive five years later, compared with 69 in 100 who keep smoking. Building a quit plan →
Diabetes
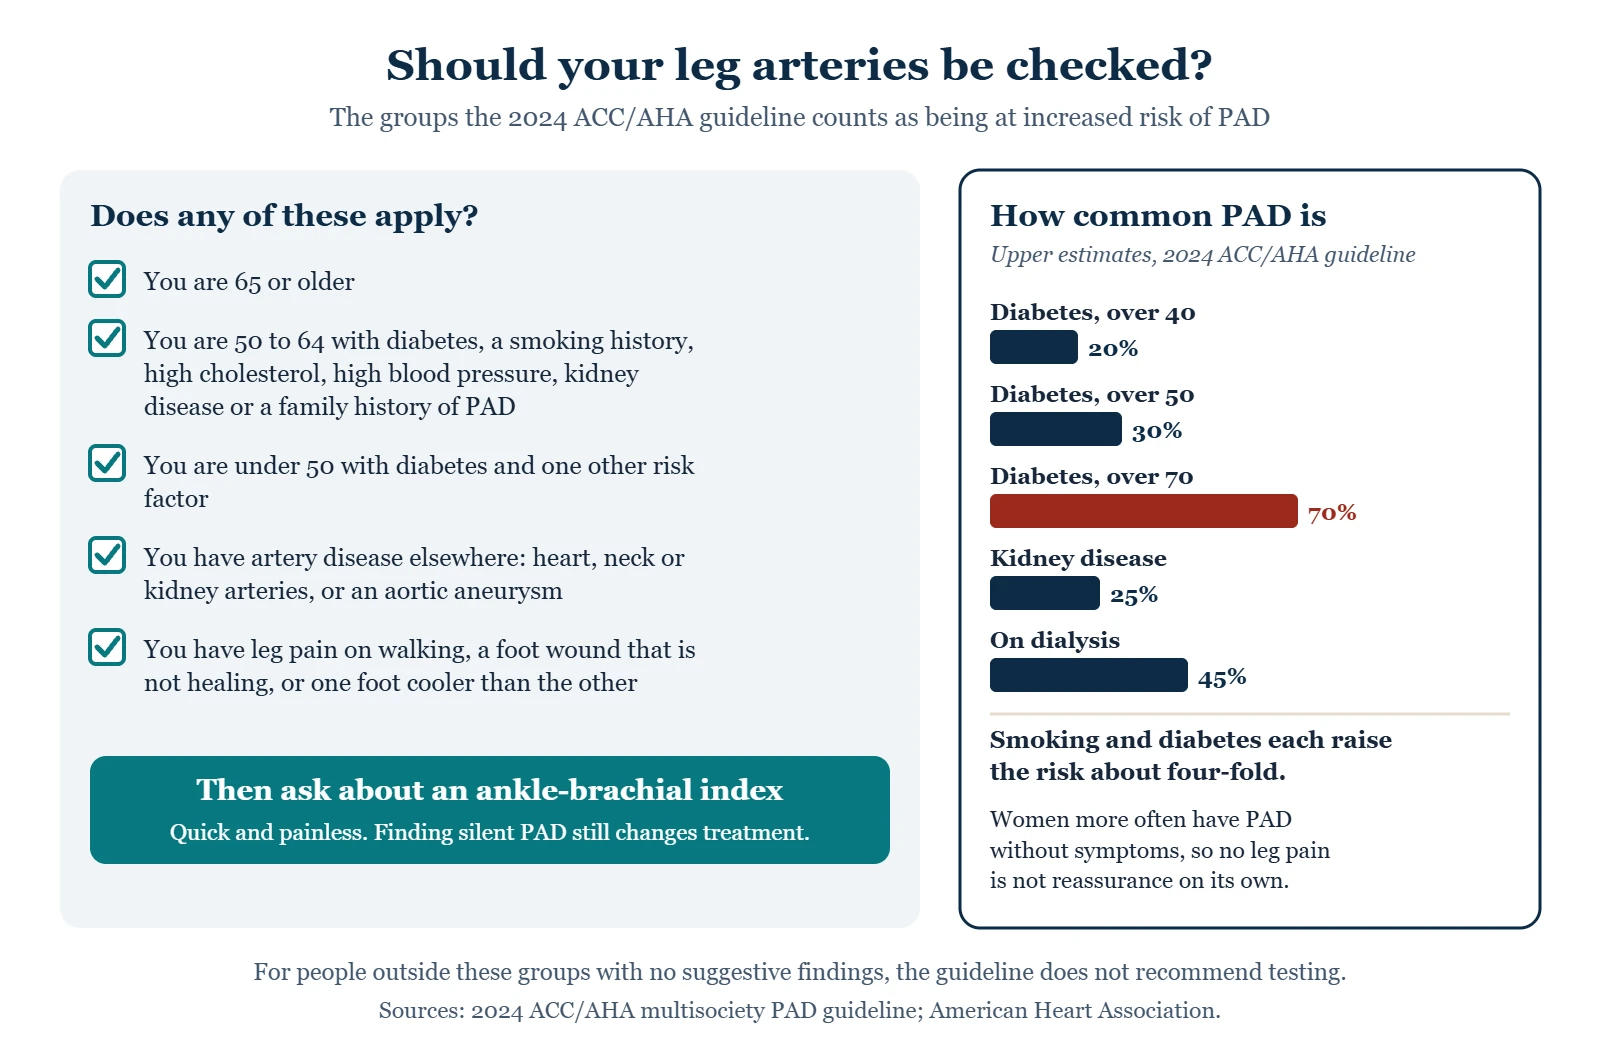
People with diabetes are about four times more likely to develop PAD. The guideline estimates it affects up to 20% of people with diabetes over 40, 30% of those over 50 and 70% of those over 70, and about half of people with limb-threatening disease have diabetes. It also changes the disease’s character: disease tends to be more distal — in the smaller vessels below the knee — and harder to treat with a procedure. Diabetes frequently brings neuropathy with it, which removes the pain that would otherwise signal a problem, so PAD in diabetes is more often silent and more often first noticed as a wound. Why that combination is dangerous →
High blood pressure
The most prevalent risk factor for PAD, present in 35 to 55% of people when PAD is diagnosed. It damages the arterial wall over time and accelerates plaque. For people with PAD and high blood pressure, the guideline target is below 130/80 mm Hg, and treating it does not starve the legs: studies of treated patients have shown improvement in claudication and function, with no sign of worse limb outcomes.
High cholesterol
Drives the plaque itself. A statin is recommended for everyone with PAD — prescribed for its effect on cardiovascular events rather than only for the number on the lipid panel, which is why a normal result usually means the treatment is working rather than that it can stop. Statins protect the legs too: in an analysis of more than 138,000 patients cited by the guideline, statin use was linked to about 30% fewer major limb events and 35% fewer amputations.
Physical inactivity and weight
Both contribute, and both are modifiable. Structured walking has a specific role in claudication beyond general fitness. How that works →
The factors you cannot change
| Factor | Why it matters |
|---|---|
| Age | Most Americans with PAD are 65 or older; risk is meaningful over 65, and over 50 with other risk factors |
| Family history | A family history of PAD is one of the features the guideline uses to flag people aged 50 to 64 for testing |
| Chronic kidney disease | Up to a quarter of people with kidney disease, and up to 45% of people on dialysis, have PAD; it also calcifies vessels, which makes the ABI harder to interpret |
| Known disease elsewhere | In one series cited by the guideline, 52% of people with PAD assessed before a leg procedure had coronary artery disease; arterial disease is rarely confined to one region |
| Race | The guideline notes higher PAD risk in Black Americans even after accounting for other risk factors; nearly 1 in 10 Black Americans over 40 have PAD |
The point people miss
A PAD diagnosis is not primarily a leg problem. It is a marker that the same process is very likely present in the heart and the brain, and the largest share of the harm PAD predicts is cardiovascular rather than limb-related. That is why the treatment plan contains medicines that do nothing for walking distance — they are aimed at the events you will not have. The full treatment map →
Who should consider being tested
The guideline counts these groups as at increased risk of PAD. Worth discussing an ankle-brachial index with your clinician if you:
- are 65 or older
- are 50 to 64 with diabetes, a smoking history, high cholesterol, high blood pressure, chronic kidney disease or a family history of PAD
- are under 50 with diabetes and one other risk factor
- have known artery disease elsewhere, such as in the heart, neck or kidney arteries, or an aortic aneurysm
- have leg symptoms on walking, a non-healing foot wound, or a foot that is cooler than the other
For people in those groups, the guideline considers a resting ABI reasonable; for people outside them with no suggestive findings, it does not recommend testing. Women are more likely than men to have PAD without symptoms, so the absence of leg pain is not reassurance on its own. The test is quick and painless, and finding PAD when it is silent still changes medical treatment in ways that reduce heart attack and stroke risk. What the test involves →
From the clinic
In a foot and ankle practice, the risk-factor conversation often starts with a toenail or a callus. Someone in their sixties who smokes or has diabetes, with thin, shiny skin and pulses I have to hunt for, gets the same advice whatever brought them in: an ABI, a conversation with their primary care doctor about a statin and blood pressure, and a quit plan if they smoke. The foot is often where the disease shows itself first.
Common questions
If I stop smoking now, does it help or is the damage done?
It helps, and it helps most in people who already have the diagnosis. In Cleveland Clinic’s figures, about 86 in 100 people who quit after a PAD diagnosis are alive five years later, against 69 in 100 who keep smoking, and quitting lowers the risk of limb problems too. Existing plaque is not usually reversed, but the trajectory changes substantially.
I have none of the risk factors. Can I still have PAD?
Yes, though it is less likely. And there are less common causes of reduced leg blood flow that do not involve plaque at all — popliteal entrapment in younger athletic people, for instance. Symptoms that fit the pattern deserve investigation regardless of the risk profile.
Does high cholesterol alone mean I will get PAD?
No. Risk factors shift probability; they do not determine outcome. Most people with raised cholesterol do not develop symptomatic PAD, and plenty of people with PAD have unremarkable cholesterol. Risk accumulates across factors rather than resting on any one.
Does diabetes change how PAD is treated?
It changes the assessment and the foot care more than the principles. Ankle pressures can read falsely normal because of vessel calcification, so toe pressures are used; disease is often more distal, which affects procedure choices; and daily foot inspection becomes considerably more important because reduced sensation hides injuries.
Is secondhand smoke a risk if I have PAD?
The guideline recommends that people with PAD avoid secondhand smoke in all indoor and enclosed spaces, including home, work and cars. It also recommends that anyone with PAD who uses any form of tobacco be offered help to quit at every visit, with medicine and counseling rather than willpower alone.
Where to go next
Sources
- Gornik HL, et al. 2024 ACC/AHA multisociety guideline for the management of lower extremity peripheral artery disease. Circulation 2024.
- American College of Cardiology. 2024 Lower Extremity PAD Guideline.
- American College of Cardiology. 2024 guideline for lower extremity PAD: key points.
- National Heart, Lung, and Blood Institute. Peripheral Artery Disease.
- National Heart, Lung, and Blood Institute. Facts about peripheral artery disease (PDF).
- American Heart Association. PAD toolkit (PDF).
- Society for Vascular Surgery. Peripheral Artery Disease.
- MedlinePlus. Peripheral arterial disease.
- StatPearls. Peripheral arterial disease.
- Cleveland Clinic. Peripheral artery disease (PAD).
- Mayo Clinic. Peripheral artery disease (PAD): symptoms and causes.
- NICE. Peripheral arterial disease: diagnosis and management (CG147).
- National Institute of Diabetes and Digestive and Kidney Diseases. Diabetes and Foot Problems.
Written by Tom Biernacki, DPM, FACFAS. Published 21 September 2026. Updated 15 October 2026. General education, not medical advice.