Leg pain that comes on with walking and stops with rest has a short list of likely explanations. Two of them dominate — narrowed arteries and a narrowed spinal canal — they are treated completely differently, and telling them apart starts with what you have to do to get relief.
Different from the usual pattern?
Pain in the foot at rest, pain that wakes you at night, a walking distance that has suddenly collapsed, or a leg that has become cold, pale or numb is not ordinary claudication. The last of those is 911; the others need to be seen the same day. New numbness around the groin or buttocks, or new bladder or bowel problems with leg symptoms is also an emergency. A calf that is swollen, warm, red and painful needs same-day care for a possible clot. Care thresholds →
The two main explanations
Arterial: claudication
Narrowed arteries deliver enough blood at rest but not enough for working muscle. Cramping or aching comes on after a fairly predictable walking distance, eases within about ten minutes of standing still, often sooner, and returns at about the same distance next time. It is worse uphill and worse walking fast. Which muscle hurts hints at where the narrowing is — calf for thigh arteries, thigh and buttock for pelvic arteries. Claudication in detail →
Spinal: neurogenic claudication
Narrowing in the spinal canal compresses nerves, and walking upright narrows it further. The pain is often more of a heaviness, weakness, numbness or tingling, it can start before you have walked far, and — the key difference — relief usually needs a change of position, not just stopping. Sitting down helps. Bending forward helps. Many people notice they can walk much further leaning on a shopping cart, or cycle without trouble while walking is difficult. Spinal stenosis is most common after 60, and the National Institute of Arthritis and Musculoskeletal and Skin Diseases describes the pain as spreading from the buttocks into the legs, worse with standing or walking and eased by sitting or bending forward. Many people improve without surgery, which is generally reserved for pain and weakness that seriously limit daily life.
How to tell them apart
| Arterial | Spinal | |
|---|---|---|
| What relieves it | Standing still for a few minutes | Sitting or bending forward |
| Time to relief | Within about 10 minutes, often sooner; fairly consistent | Variable, often longer, and only after a change of position |
| Reproducibility | Similar distance each time | Varies day to day |
| Walking uphill | Worse | Often easier — you are leaning forward |
| Cycling | Brings symptoms on | Often fine |
| Standing still for a long time | Comfortable | Can bring symptoms on |
| Sensation | Usually normal | Numbness, tingling or weakness common |
| Pulses | Reduced or absent | Normal |
| Key test | Ankle-brachial index | MRI of the lumbar spine |
They also coexist, particularly over 65 — which is exactly why the ABI is worth doing. It settles one of the two questions in a single short appointment. The ABI test →
Two simple observations you can make
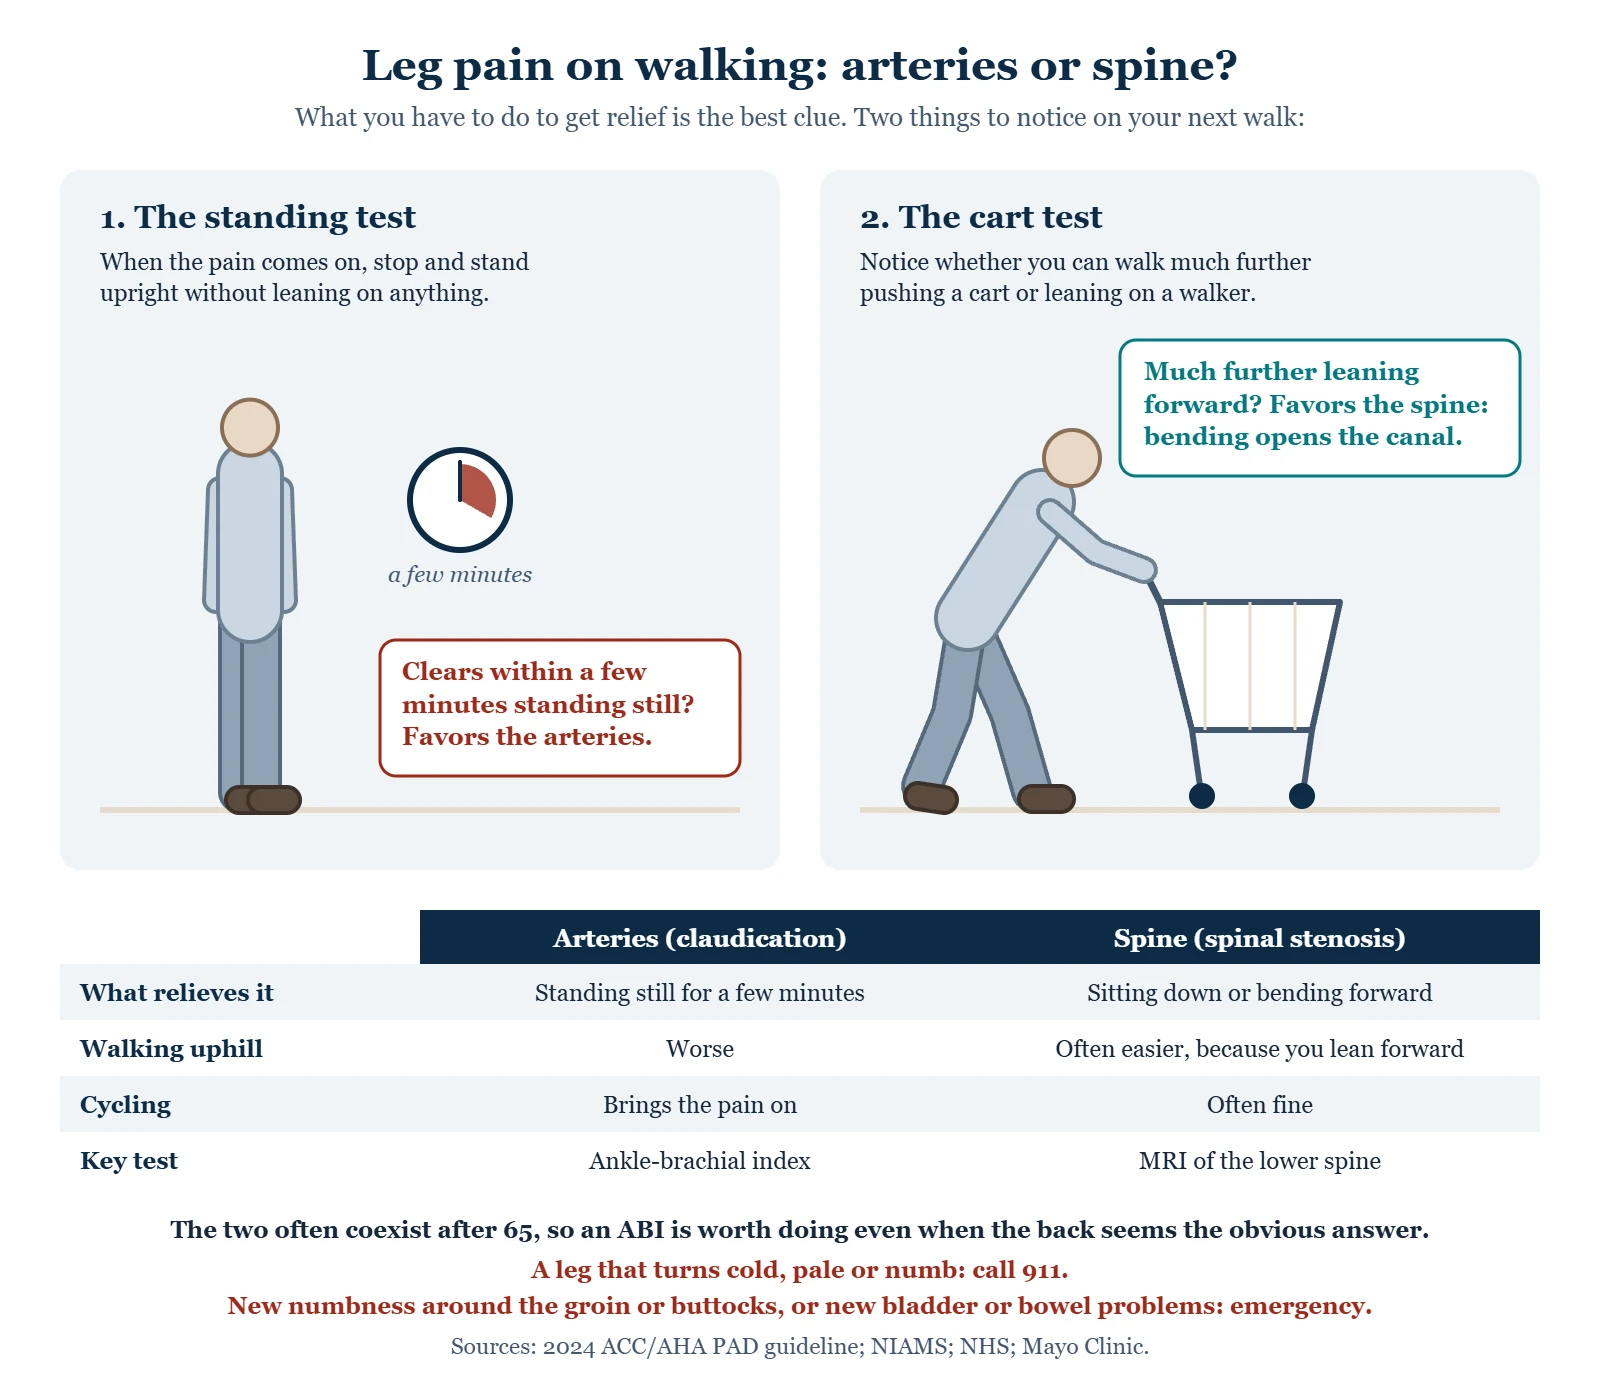
- The standing test. Next time the pain comes on, stop and stand upright without leaning on anything. If it clears within a few minutes, that favors the arteries. If it only settles once you sit or bend forward, that favors the spine.
- The cart test. Notice whether you can walk much further pushing a shopping cart or leaning on a walker. A big difference favors the spine, because bending forward opens the spinal canal.
Neither replaces an examination, but both make the conversation at the appointment more useful.
The other possibilities
| Cause | Who it tends to affect | How it behaves |
|---|---|---|
| Hip or knee osteoarthritis | Older adults, most often from 50 | Pain at the joint (for the hip, mainly the groin), stiff in the morning and after rest, flaring with activity; not cleared by standing still |
| Chronic exertional compartment syndrome | Athletes, most often under 30, especially runners | Tightness, aching or burning at a consistent point in exercise, settling within about 15 minutes of stopping; sometimes numbness |
| Venous claudication | People with a previous major clot in the thigh or pelvis | Tight, throbbing pain through the whole leg, worst in the thigh and groin; eases slowly with rest and faster with the leg raised |
| Popliteal artery entrapment | Young athletes, mostly in their teens or twenties and about 85% male | Calf claudication from an artery squeezed behind the knee by muscle |
| Peripheral neuropathy | Diabetes, B12 deficiency, alcohol and others | Burning, tingling or numbness present at rest, often worse at night |
| Muscle cramps or medicine-related muscle pain | Anyone; some people on statins | Aching or cramping not tied to a set distance; often in both legs |
| Stress fracture | New or increased running or walking | Pain at one bony spot that worsens with each session and is tender to press |
Compartment syndrome is confirmed by measuring the pressure inside the muscle compartment before and after exercise, and surgery to release the compartment (fasciotomy) is the most effective treatment. In a young runner, a stress fracture is worth ruling out too.
The single most useful thing you can bring
A number and a position. “About two blocks, and I have to sit down” is far more informative than “my legs hurt when I walk”. Note the distance that brings it on, how long relief takes, and whether you have to sit or can just stand. That one sentence does more diagnostic work than any description of the pain itself.
What the appointment involves
- History focused on distance, relief, position and reproducibility.
- Examination: pulses in both legs, skin and nails, hip and knee movement, neurological testing.
- An ABI, with a toe pressure if you have diabetes or kidney disease. An exercise ABI if the resting one looks normal but the story is convincing: up to 30% of people with symptoms and a normal resting test turn out to be abnormal after exercise.
- Spinal imaging if the pattern points that way.
- A plan for whichever it is — and for both if both are present.
From the clinic
People are often sent from one specialist to another with this symptom: the back doctor says it is circulation, the circulation doctor says it is the back. The way out of that loop is objective testing on both sides — an ABI and, if it is normal, an exercise ABI; spinal imaging if the history fits. When both turn out to be present, treating the more limiting one first and re-measuring the walking distance usually shows what is left.
Common questions
Can it be both?
Yes, and it is common enough over 65 that clinicians look for it. Treating only one and finding the walking distance barely changes is the usual way the second one gets discovered. Worth asking about directly if you have been treated for one without much improvement.
Why do my calves hurt when I walk but not when I rest?
That pattern — pain with walking, relief with rest — is the classic description of claudication from narrowed arteries, especially if the distance is predictable and standing still is enough to ease it. It is worth an ABI. If you need to sit or bend forward for relief, the spine becomes the more likely explanation.
Is it dangerous to keep walking?
For diagnosed, stable claudication, structured walking is part of the treatment. For an undiagnosed leg it is not a plan, and if you have a wound, rest pain, or a recent change it is the wrong advice entirely. The diagnosis comes first. More on structured walking →
My pain is in my foot, not my calf. Does that fit?
Foot pain on walking is less typical of classic claudication and raises other possibilities, including more distal arterial disease, nerve problems and structural foot conditions. Foot pain at rest, particularly at night and relieved by hanging the foot down, is a specific and more concerning arterial pattern that should be seen the same day.
Could my statin be causing the leg pain?
Muscle aches are a known side effect of statins in a minority of people, usually in both legs and not tied to a particular walking distance. In placebo-controlled comparisons the true risk is about 5% or less, and serious muscle damage is very rare, a few cases per million users. Do not stop the statin on your own — in PAD it is one of the most protective medicines you take. Raise it with your prescriber, who can check and adjust.
Isn’t this just part of getting older?
No. Mayo Clinic notes that putting it down to age is one reason claudication so often goes undiagnosed, and the NHS says there is no reason an otherwise healthy person should have leg pain when walking. A pattern you can describe in blocks and minutes deserves an explanation.
I am only 40. Can I have arterial disease?
Less likely, but not impossible — especially with smoking, diabetes, kidney disease or a strong family history. In younger and athletic people, popliteal entrapment and compartment syndrome also come into the frame. The point is the same: a reproducible walking-distance pattern deserves an explanation rather than a shrug.
Where to go next
- Foot and toe cramps: cramp, claudication or something else?
- Leg cramps at night: causes, quick relief and when to worry
- Claudication: what it means and how it is treated
- PAD symptoms and warning signs
- Calf pain: muscle, clot or artery?
- Leg pain at night
- What the ABI measures
- Walking with PAD
- Near Howell or Bloomfield Township, Michigan: a foot and ankle evaluation (the author’s own practice)
Sources
- Gornik HL, et al. 2024 ACC/AHA multisociety guideline for the management of lower extremity peripheral artery disease. Circulation 2024.
- American Family Physician. Peripheral artery disease: rapid evidence review (2019).
- American Family Physician. Peripheral vascular disease (2006).
- Mayo Clinic. Claudication: symptoms and causes.
- Mayo Clinic. Claudication: diagnosis and treatment.
- Mayo Clinic. Ankle-brachial index.
- NHS. Peripheral arterial disease (PAD).
- National Institute of Arthritis and Musculoskeletal and Skin Diseases. Spinal stenosis.
- American Academy of Orthopaedic Surgeons. Lumbar spinal stenosis.
- StatPearls. Spinal stenosis and neurogenic claudication.
- Mayo Clinic. Chronic exertional compartment syndrome: symptoms and causes.
- Mayo Clinic. Chronic exertional compartment syndrome: diagnosis and treatment.
- StatPearls. Popliteal artery entrapment syndrome.
- American Academy of Orthopaedic Surgeons. Osteoarthritis of the hip.
- National Institute of Diabetes and Digestive and Kidney Diseases. Peripheral neuropathy.
- Mayo Clinic. Statin side effects.
- Mayo Clinic. Stress fractures.
- Mayo Clinic. Muscle cramp.
- Mayo Clinic. Leg pain: when to see a doctor.
Written by Tom Biernacki, DPM, FACFAS. Published 20 September 2026. Updated 15 October 2026. General education, not medical advice.