The best-known symptom of peripheral artery disease (PAD) is leg pain on walking. The most common presentation is nothing at all. Both of those facts matter, and the second one is why this page exists: PAD is usually found by someone who went looking, not by someone who was waiting for pain.
The symptoms that need attention now
- Sudden coldness, pallor, mottling, numbness, weakness or severe pain in a leg or foot, over minutes to hours — call 911. Blood supply can be cut off abruptly and the window to save tissue is short.
- Pain in the forefoot or toes at rest, worse lying flat, relieved by hanging the foot down — get seen the same day.
- A wound on the foot that is not healing, or a new dark patch on a toe or heel — the same day. A toe or patch of skin that has turned black, gray or dark purple, or looks dead — an emergency department now.
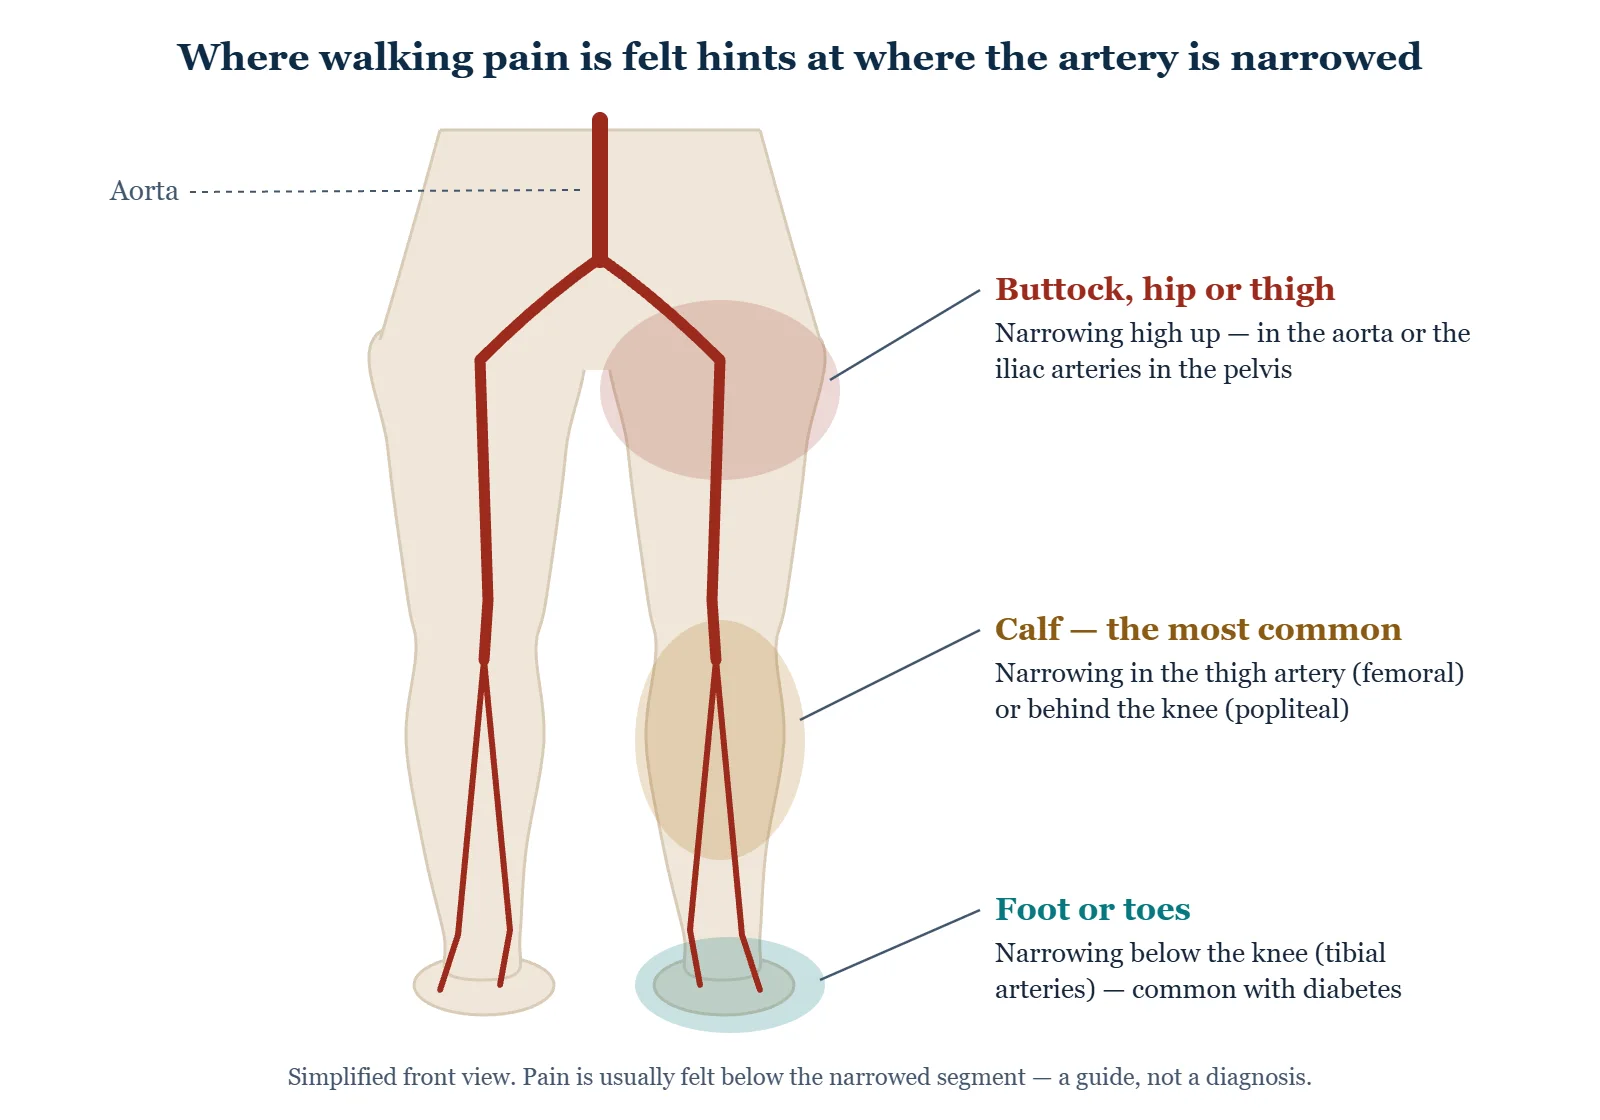
How common it is, and why it goes unnoticed
The 2024 American College of Cardiology and American Heart Association guideline estimates that 10 to 12 million Americans over 40 have PAD. Awareness lags far behind: in one US survey cited by the American Heart Association, only about 1 in 4 adults with risk factors and walking problems had even heard of it.
Most of those people do not have the textbook symptom. According to the National Heart, Lung, and Blood Institute, only about 1 in 4 people with PAD have the classic symptoms, more than half have atypical leg symptoms, and about 1 in 5 report none at all. People slow down, take the elevator, or stop walking as far, and put the change down to age or fitness, a mistake the NHS specifically warns about. A low ABI found this way is still worth finding: it marks a substantially raised risk of heart attack and stroke, and that risk responds to treatment.
Claudication: the classic pattern
Cramping, aching, tightness or fatigue in the calf, thigh or buttock that:
- comes on after walking a fairly consistent distance,
- eases within about ten minutes of standing still, often sooner — you do not need to sit down,
- and returns at roughly the same distance the next time.
The reproducibility is what distinguishes it. Muscle strains do not behave like that, and neither does most back-related leg pain. Walking uphill, quickly or carrying something brings it on sooner. If that is true for you, say so — it strengthens the arterial picture. Claudication in detail →
| Where it aches on walking | Where the narrowing usually is | Worth knowing |
|---|---|---|
| Buttock, hip or thigh | Aorta or iliac arteries, in the abdomen and pelvis | Often both legs; in men it can come with erectile dysfunction |
| Calf | Femoral artery in the thigh or popliteal artery behind the knee | The most common pattern |
| Foot or arch | Smaller arteries below the knee | Less common; diabetes and kidney disease tend to affect these arteries, and it is easily mistaken for a foot problem |
The signs a clinician looks for
Many of the most useful signs of PAD are things you cannot feel but someone examining your feet can see:
- Weak or absent pulses at the top of the foot and behind the inner ankle bone, or a difference between the two feet.
- A cool foot, or one foot cooler than the other.
- Color change with position — the foot goes pale when raised and turns dusky red when it hangs down. That red-when-down color is called dependent rubor, and it is a sign of severe disease.
- Slow capillary refill — press on a toenail and the color takes longer than usual to come back.
- Thin, shiny, hairless skin on the lower leg and foot, and thick, slow-growing toenails.
- Wasting of the calf muscles in one leg.
- A bruit — a whooshing sound over an artery heard through a stethoscope.
None of these alone makes the diagnosis, and several are common in older feet with normal arteries. Together they raise the question; the ankle-brachial index answers it.
The symptoms people do not connect to circulation
- Legs that tire quickly, put down to age or being unfit. People often stop walking as far and never notice they are avoiding the symptom.
- A persistently cold foot, or one foot colder than the other. Cold feet in detail →
- Hair loss on the lower leg and foot, shiny or thin skin, thickened slow-growing toenails.
- A blister, crack or small cut that takes weeks rather than days.
- Color changes: pale when the leg is raised, dusky red or purplish when it hangs down. Foot color changes →
- Muscle wasting in the calf.
- Erectile dysfunction, which can accompany disease in the pelvic arteries.
PAD and diabetes: why the warning signs go quiet
Diabetes changes almost everything on this page. The disease tends to affect the smaller arteries below the knee, so the classic calf claudication is less common. Nerve damage removes the pain that would otherwise announce the problem — someone can have severely reduced blood flow and a wound on the foot and feel very little. And calcium in the artery walls can make the ankle pressures read falsely normal, so a “normal” ABI is less reassuring. The guideline estimates that among people with diabetes, PAD affects up to 20% of those over 40, 30% of those over 50 and 70% of those over 70, and about half of people with limb-threatening disease have diabetes. NICE specifically warns against ruling out PAD in someone with diabetes because the ABI is normal or raised; when the ankle arteries will not compress and the ABI reads above 1.40, a toe pressure or toe-brachial index is the next test.
In practice that means three things if you have diabetes: check your feet every day rather than waiting for pain, ask whether your pulses and toe pressures have been checked, and treat any break in the skin of the foot as something to be seen promptly. Wounds that will not heal →
Why so many people have no symptoms
Partly because narrowing has to be fairly advanced before it limits supply at ordinary walking speeds, and partly because people unconsciously slow down or walk less. In diabetes there is a third reason: nerve damage removes the pain that would otherwise signal the problem. A silent PAD diagnosis still matters — it marks substantially raised risk of heart attack and stroke, and that risk is treatable.
Rest pain and tissue loss
When narrowing becomes severe enough that supply is inadequate even at rest, the picture changes. Rest pain is typically in the forefoot and toes, worse at night and lying flat, and eased by dependency — hanging the foot out of bed, or sleeping in a chair. It is often described as severe, and it frequently coexists with skin breakdown.
Rest pain, an ulcer that will not heal, or gangrene, lasting more than two weeks and caused by a proven arterial blockage, make up chronic limb-threatening ischemia (CLTI). The guideline estimates it develops in 11 to 20% of people with known PAD, and historically up to 30% of people with CLTI needed an amputation within a year. The Society for Vascular Surgery advises urgent referral to a vascular surgeon for rest pain, especially at night, or a foot sore that will not heal. This is urgent, not routine, and the management involves restoring blood flow rather than dressings alone. Rest pain and CLTI →
Sudden symptoms: acute limb ischemia
A different and more dangerous event is a sudden blockage — a clot forming on a narrowed artery, or one travelling from the heart. It does not build over months; it arrives over minutes to hours. Clinicians remember the signs as the “six Ps”:
- Pain, often severe
- Pallor — the leg turns pale or mottled
- Pulselessness
- Poikilothermia — the leg is cold
- Paresthesia — numbness or pins and needles
- Paralysis — weakness or inability to move the foot
Weakness or paralysis is a late and grave sign. This is a 911 call, not a wait-and-see.
What else causes leg pain on walking
| Cause | How it tends to behave |
|---|---|
| PAD (claudication) | Same distance each time; eases within minutes of standing still |
| Spinal stenosis | Comes on with standing as well as walking; needs sitting or bending forward to ease; often better leaning on a shopping cart or walking uphill |
| Venous claudication | A tight, bursting pain through the whole leg, usually after a previous deep vein clot; eases slowly with rest and faster with the leg raised |
| Hip or knee arthritis | Pain at the joint, often worst on starting off; varies day to day; not relieved quickly by standing still |
| Neuropathy | Burning, tingling or numbness that is present at rest and often worse at night, not tied to walking distance |
These can coexist, which is one reason the ABI is so useful — it settles the arterial question objectively. Leg pain when walking: telling them apart →
Who is at risk
Smoking is the strongest single risk factor, raising the risk about four-fold, and the guideline notes that risk stays more than double a never-smoker’s for 10 to 20 years after quitting. Diabetes also raises it about four-fold, and high blood pressure is the most common risk factor of all. Age, high cholesterol, chronic kidney disease (up to a quarter of people with kidney disease, and up to 45% of people on dialysis, have PAD) and known heart or carotid artery disease all add to it. The guideline counts you as at increased risk if you are 65 or older; 50 to 64 with diabetes, a smoking history, high cholesterol, high blood pressure, kidney disease or a family history of PAD; under 50 with diabetes and one other risk factor; or living with known artery disease elsewhere. Risk factors in detail →
What to bring to the appointment
- The walking distance that reliably brings it on, and how long relief takes.
- Whether it is one leg or both, and whether one is worse.
- Whether elevation helps or hurts.
- Any wound, blister or color change, however small — photograph it if it might look different by the appointment.
- Your smoking history, diabetes status, and your medicine list.
From the clinic
A lot of PAD walks into a foot and ankle office disguised as something else: a toenail problem that will not settle, a blister from new shoes that is still there a month later, a “cold foot” that only bothers someone in bed. The pattern I take most seriously is one foot that looks and feels different from the other — cooler, paler, slower to color up, with fainter pulses. Feet should broadly match. When one does not, the circulation deserves a look before anyone trims, cuts or operates on that foot.
Common questions
What does PAD pain feel like?
Usually a cramp, ache, tightness or tired heaviness in a muscle — most often the calf — that builds with walking and fades within a few minutes of stopping. Many people describe it as their legs “giving out” rather than as pain. Severe disease causes a different, constant burning or aching pain in the toes at rest, typically worse at night.
How far can someone with PAD usually walk?
It varies enormously, from a couple of city blocks to a few hundred feet, and the number matters less than whether it is changing. A distance that has shortened noticeably over weeks or months is worth reporting, and so is a distance that suddenly collapses.
Could my leg pain be my back instead?
It could. Spinal stenosis produces leg pain on walking too, but it typically needs sitting or leaning forward for relief rather than simply standing still, it varies more from day to day, and it often improves walking uphill or pushing a shopping cart. Arterial pain is more reproducible. The two can also coexist, which is why the ABI is useful — it answers one of the two questions definitively.
Are cold feet enough to suggest PAD?
On their own, no. Cold feet are extremely common in people with normal arteries. Cold feet plus weak pulses, plus skin or nail changes, plus pain on walking is a different matter, and any wound in a cold foot deserves a check regardless.
Does PAD cause leg swelling?
Not usually. Swelling is much more often a vein, lymph, heart, kidney or medication problem. The exception is severe PAD, where people with rest pain sleep with the leg hanging down and the foot swells as a result. Swelling plus a cold, painful foot is a reason to be seen quickly.
Can PAD be reversed?
The narrowing itself is not usually reversed by lifestyle alone, but the outlook is far better than most people assume. Stopping smoking, a statin and other protective medicines, and a structured walking program can substantially improve walking distance and reduce the risk of heart attack, stroke and amputation. Procedures can restore flow when they are needed. Treatment options →
I have no pain but I am worried. Should I be tested?
Worth discussing with your clinician if you are in one of the guideline’s increased-risk groups: 65 or older; 50 to 64 with risk factors such as diabetes, smoking, high cholesterol, high blood pressure, kidney disease or a family history of PAD; under 50 with diabetes plus another risk factor; or known artery disease elsewhere. For those groups it considers a resting ABI reasonable; for people outside them with no suggestive findings, it does not recommend testing. The test is quick, non-invasive, and a positive result changes medical treatment in ways that reduce heart attack and stroke risk — so it is useful even when the legs feel fine.
Does a normal ABI rule out PAD?
Not always. In diabetes and kidney disease, stiff, calcified ankle arteries can make the reading falsely normal or high, and in the guideline’s data nearly a quarter of people with limb-threatening disease had an ABI in the normal range. If your symptoms fit and the resting test is normal, an ABI repeated after walking, or toe pressures, is the next step.
Is PAD the same as poor circulation?
PAD is one specific cause of what people call poor circulation — narrowed arteries delivering too little blood. Vein problems, lymphedema and conditions such as Raynaud’s are others, and they behave very differently. Poor circulation, sorted by cause →
Where to go next
- Numb toes: when it is circulation and when it is not
- Foot cramps at night: cramp or rest pain?
- Leg cramps at night or claudication?
- Blue toe syndrome: a toe that suddenly turns blue or purple
- Buerger’s disease: toe sores and cold fingers in people who smoke
- Gangrene of the toes: what it looks like and how it is treated
- Claudication: leg pain on walking that eases with rest
- The ABI test and what the numbers mean
- The main PAD guide
- PAD treatment
- Walking with PAD
- Leg pain when walking: the other possible causes
- Arterial ulcers: how they look and how they heal
- Signs of poor circulation in the legs and feet, with pictures
Sources
- Gornik HL, et al. 2024 ACC/AHA multisociety guideline for the management of lower extremity peripheral artery disease. Circulation 2024.
- American College of Cardiology. 2024 guideline for lower extremity PAD: key points.
- National Heart, Lung, and Blood Institute. Peripheral artery disease: symptoms.
- National Heart, Lung, and Blood Institute. Peripheral artery disease: diagnosis.
- National Heart, Lung, and Blood Institute. Facts about peripheral artery disease (PDF).
- American Heart Association. PAD toolkit (PDF).
- American Heart Association. Symptoms and diagnosis of PAD.
- Mayo Clinic. Peripheral artery disease (PAD): symptoms and causes.
- Cleveland Clinic. Peripheral artery disease (PAD).
- Society for Vascular Surgery. Peripheral artery disease.
- Society for Vascular Surgery. Acute limb ischemia.
- Society for Vascular Surgery. Diabetes and vascular disease.
- NICE. Peripheral arterial disease: diagnosis and management (CG147).
- NHS. Peripheral arterial disease (PAD).
- MedlinePlus. Peripheral arterial disease.
- StatPearls. Peripheral arterial disease.
- StatPearls. Spinal stenosis and neurogenic claudication.
- American Family Physician. Peripheral vascular disease.
- American Academy of Orthopaedic Surgeons. Lumbar spinal stenosis.
- National Institute of Diabetes and Digestive and Kidney Diseases. Peripheral neuropathy.
Written by Tom Biernacki, DPM, FACFAS. Published 20 September 2026. Updated 15 October 2026. General education, not medical advice.