Most people are told a clot is treated and finished. For a substantial minority it leaves something behind: a leg that aches, swells and changes over the following years. It has a name, it is not imagined, and there is a great deal that can be done about it.
What it is
A deep vein clot damages the vein from the inside. Even after the body has cleared or recanalized it, the delicate one-way valves within that vein are often destroyed, and the vein wall may stay narrowed or scarred. The result is the same mechanical problem as chronic venous insufficiency, but with a known starting point: blood falls back down the leg instead of being carried up, pressure in the small vessels stays high, and the tissue pays for it.
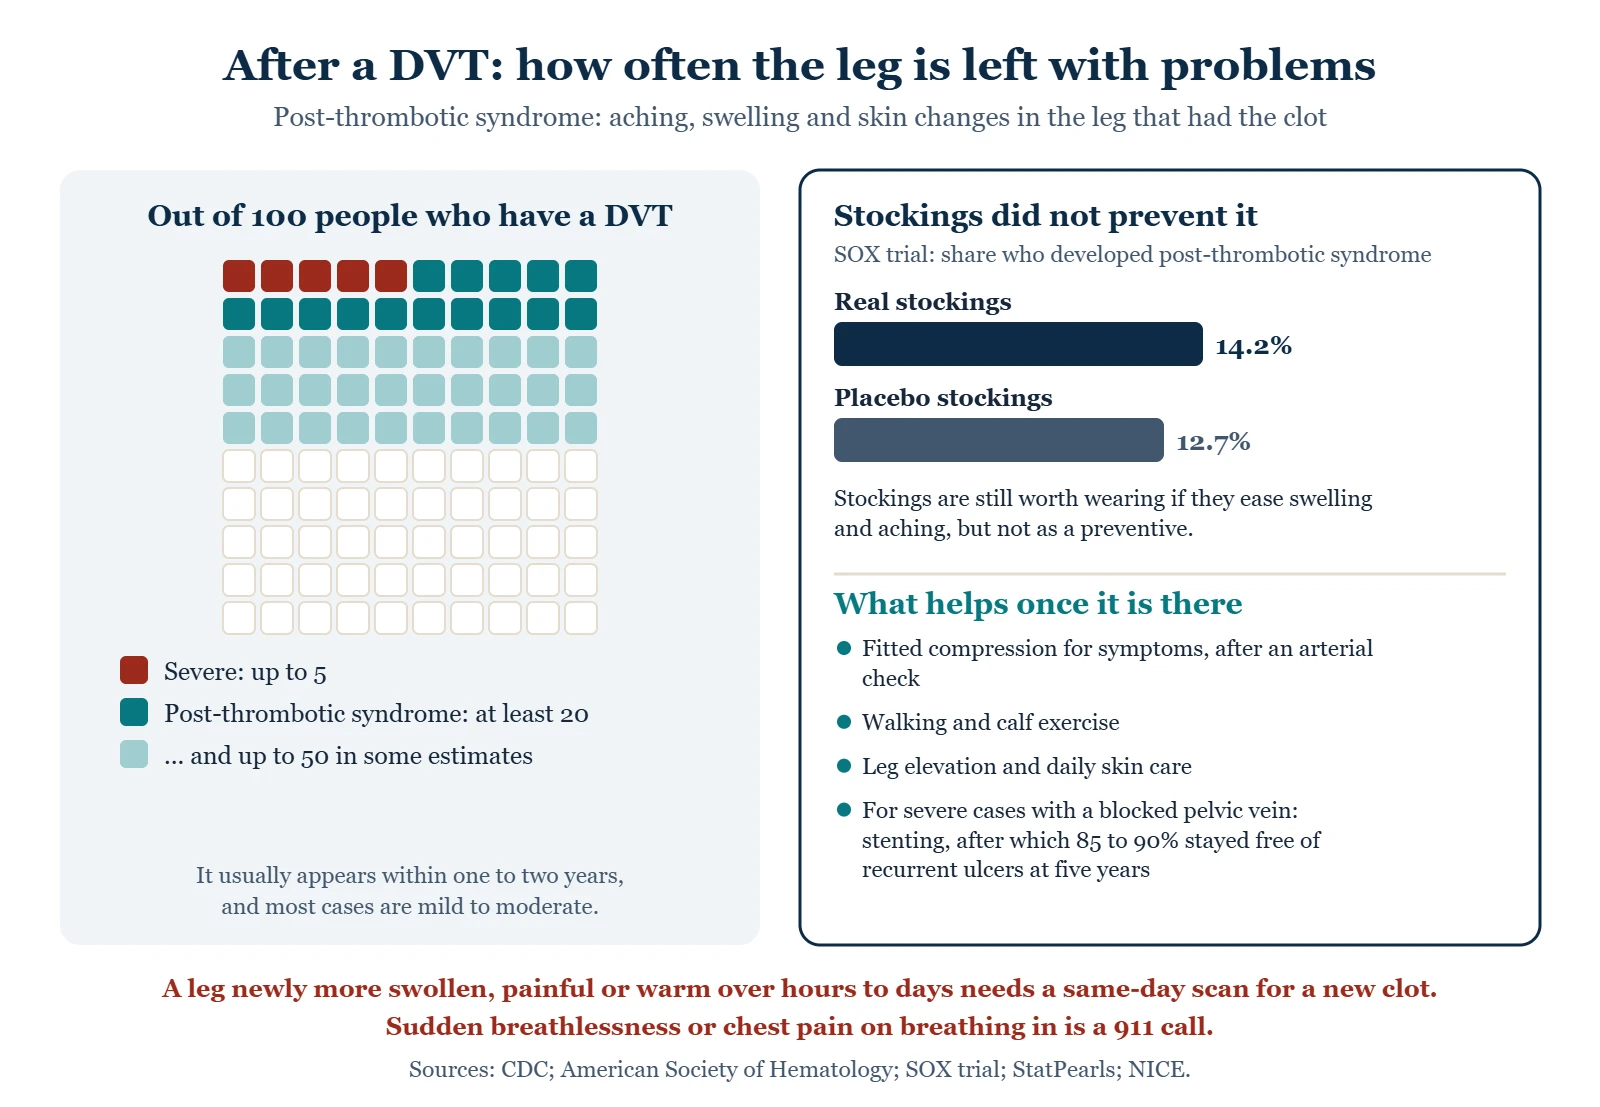
It is common. The CDC estimates that between a third and a half of people who have a DVT go on to develop post-thrombotic syndrome, and the American Society of Hematology puts it at 20 to 50%, severe in up to 5%. It usually appears within the first one to two years, and the leg that had the clot is the leg affected. Most cases are mild to moderate.
What it feels and looks like
| Feature | Detail |
|---|---|
| Heaviness and aching | Worse through the day, worse standing, relieved by raising the leg |
| Swelling | The affected leg only. Often noticeable by evening and better by morning |
| Cramping or a bursting pain on walking | Called venous claudication: a tight, throbbing pain through the whole leg, often worst in the thigh and groin, that eases slowly with rest and faster with the leg raised |
| Itching, tingling, pins and needles | Common and often dismissed |
| Skin changes | Brown staining around the ankle, dryness, eczema, and in time hardened tight skin above the ankle |
| Visible veins | New prominent veins over the thigh, groin or abdomen can be collaterals routing blood around an obstructed segment |
| Ulceration | The end of the spectrum, usually just above the inner ankle. More → |
New symptoms are not automatically this
A leg that becomes newly more swollen, painful or warm over hours to days needs same-day assessment for a fresh clot, not an assumption that it is post-thrombotic syndrome. Clots come back often — the CDC estimates that a third of people with a venous clot have another within 10 years — and telling the two apart requires an ultrasound rather than a judgment call. Sudden breathlessness or chest pain on breathing in is a 911 call.
How it is diagnosed
There is no single test. It is a clinical diagnosis made from the combination of a documented previous DVT in that leg, symptoms and signs that persist beyond three to six months after the clot, and exclusion of a new clot. A duplex ultrasound shows whether the vein has reopened, whether the valves are competent, and whether there is residual obstruction; in selected cases imaging of the pelvic veins is added, because an obstruction high up is one of the more treatable patterns.
Clinicians often use a scoring tool that grades symptoms and signs into mild, moderate or severe. It is worth asking for the severity rather than just the label, because it influences what is offered.
Treatment
Compression for symptoms. Graduated below-knee stockings, correctly measured and worn daily, can ease swelling and aching and protect the skin. As always the arterial supply is checked first. The safety check, then the fit.
Walking and calf exercise. The calf muscle pump is doing the work that the valves no longer do, and walking is encouraged after a DVT; StatPearls notes that exercise does not appear to raise the risk of a clot traveling. If you are unsure where to start, a physical therapy referral is a reasonable thing to ask for.
Elevation and skin care. Raising the leg above heart level for periods during the day, daily moisturizing, and prompt attention to any break in the skin. Doing it properly →
Treating obstruction where it exists. For a minority — usually those with severe symptoms and a blocked iliac vein in the pelvis — opening and stenting that segment can make a substantial difference: StatPearls reports that 85 to 90% of people stay free of recurrent ulcers five years after iliac vein stenting. It is a specialist assessment and not appropriate for most people, but it is worth knowing the option exists if your symptoms are severe and nobody has mentioned it.
Anticoagulation is about preventing another clot rather than treating the syndrome itself. Whether it continues long term depends on why the first clot happened, and that is a conversation to have explicitly rather than by default. How long treatment lasts →
What the evidence says about stockings and prevention
For years, people were told to wear compression stockings for two years after a DVT to prevent this syndrome. That advice has not held up. In the large placebo-controlled SOX trial, 14.2% of people wearing real stockings developed post-thrombotic syndrome, against 12.7% wearing placebo stockings, and a Cochrane review of the wider evidence found at most a borderline benefit on low-quality evidence. NICE now advises against offering stockings to prevent it, and CHEST and the American Society of Hematology advise against routine use. Stockings are still worth wearing if they ease swelling and pain — that is a good reason — but not as a preventive.
The best treatment is the one given early
What gives the leg its best chance is good care of the original clot: anticoagulation taken as prescribed, without gaps, and walking rather than bed rest once treatment has started. If you are reading this in the weeks after a new DVT, that is the actionable part.
From the clinic
The patients who struggle most with this were often never told it had a name. They had a clot after an injury or surgery, finished their blood thinner, and spent the next two years being told the heavy, swollen leg was “just how it is now”. Naming it opens the door: properly fitted compression for comfort, a walking plan, skin care before the ankle breaks down, and a specialist look at the pelvic veins when symptoms are severe.
Common questions
My leg still hurts a year after my DVT. Is that normal?
It is common, and it has a name. Persisting heaviness, aching and swelling in the leg that had the clot, six months or more afterward, is post-thrombotic syndrome rather than something you should have got over. It is worth naming at an appointment, because it opens the door to compression, physical therapy and, in severe cases, assessment for a treatable obstruction.
How do I know if it is a new clot instead?
You cannot reliably tell, and neither can a clinician without imaging — which is exactly why a clear change in the leg over hours to days is a same-day ultrasound rather than a wait. Post-thrombotic symptoms fluctuate through the day and week; a genuine step change in swelling or pain is different.
Do I have to wear compression forever?
That depends on whether it helps you. Stockings are not recommended to prevent post-thrombotic syndrome, but many people with established symptoms find they control the swelling and aching, and removing them lets the pressure return. If you wear them, replace them about every six months, because they lose their compression with wear, and remember that a garment you can actually get on is worth far more than a stronger one sitting in a drawer. Tell your clinician if they are hard to apply; there are aids and alternatives.
Can it be cured?
The valve damage is permanent, so cure is the wrong frame. Control is realistic, and for many people symptoms can be brought down with compression, walking, elevation and skin care. Where a pelvic vein is blocked, stenting can produce a genuinely large improvement — which is the main reason severe cases deserve a specialist opinion rather than acceptance.
Why do I have new veins on my abdomen?
Those are usually collateral veins — the body routing blood around a blocked segment higher up. They are a sign worth reporting rather than a cosmetic issue, because they point toward an obstruction that imaging can locate and that may be treatable.
Should I wear compression stockings after a new DVT to prevent this?
Not for prevention. The placebo-controlled SOX trial found no benefit, and NICE, CHEST and the American Society of Hematology advise against routine stockings for that purpose. If the leg is swollen and sore, stockings can make it more comfortable, and that is a perfectly good reason to wear them.
Where to go next
Sources
- Centers for Disease Control and Prevention. About Blood Clots.
- Centers for Disease Control and Prevention. Data and statistics on venous thromboembolism.
- National Heart, Lung, and Blood Institute. Venous Thromboembolism.
- American Society of Hematology. 2020 guidelines for management of venous thromboembolism: treatment of DVT and PE.
- CHEST. Antithrombotic therapy for VTE disease: second update of the CHEST guideline (2021).
- NICE. Venous thromboembolic diseases: diagnosis, management and thrombophilia testing (NG158).
- Cochrane. Compression therapy for prevention of post-thrombotic syndrome.
- StatPearls. Post-thrombotic syndrome.
- StatPearls. Venous insufficiency.
- Cleveland Clinic. Chronic venous insufficiency (CVI).
- American Family Physician. Peripheral vascular disease (2006).
- American Family Physician. Venous ulcers: diagnosis and treatment (2019).
- NHS. Deep vein thrombosis (DVT).
- Society for Vascular Surgery. Chronic Venous Insufficiency.
- MedlinePlus, National Library of Medicine. Venous Insufficiency.
Written by Tom Biernacki, DPM, FACFAS. Published 21 September 2026. Updated 15 October 2026. General education, not medical advice.