Chronic venous insufficiency is what happens when the valves in the leg veins stop closing properly. Blood falls back down between muscle contractions, pressure in the lower leg stays high, and over years that sustained pressure changes the tissue — first as aching and evening swelling, later as stained, hardened skin and, at the far end, ulcers. It is common, it is slow, and the early stages are where treatment does the most good.
When venous leg problems need prompt attention
- One leg suddenly more swollen and painful than the other — that can be a new clot and needs same-day assessment. DVT →
- Spreading redness, heat and pain in the lower leg — possible cellulitis, the same day; with a fever, chills or feeling unwell, an emergency department now.
- Bleeding from a vein — lie down, raise the leg high, press firmly, and get help.
- A break in the skin above the ankle that has not healed in two weeks — book an appointment rather than waiting.
How the damage happens
Standing upright puts a long column of blood above the ankle. The leg manages it with valves and the calf pump: every step squeezes the deep veins and pushes blood upward, and the valves stop it falling back. When valves leak, that column is no longer broken into segments, and the pressure at the ankle stays high even while you are walking. Fluid is pushed out into the tissue; red blood cells leak out too, and the iron they leave behind stains the skin brown. Inflammation follows, and eventually the skin and underlying tissue become thickened and fragile.
That is why venous disease is a slow story with a visible sequence, rather than a single event. Estimates vary widely with how it is defined: StatPearls puts chronic venous insufficiency at 10 to 35% of US adults, while Cleveland Clinic estimates about 1 in 20 adults, with varicose veins in about 1 in 3. Each year, about 1 in 50 people with varicose veins progress to chronic venous insufficiency.
The stages, as clinicians record them
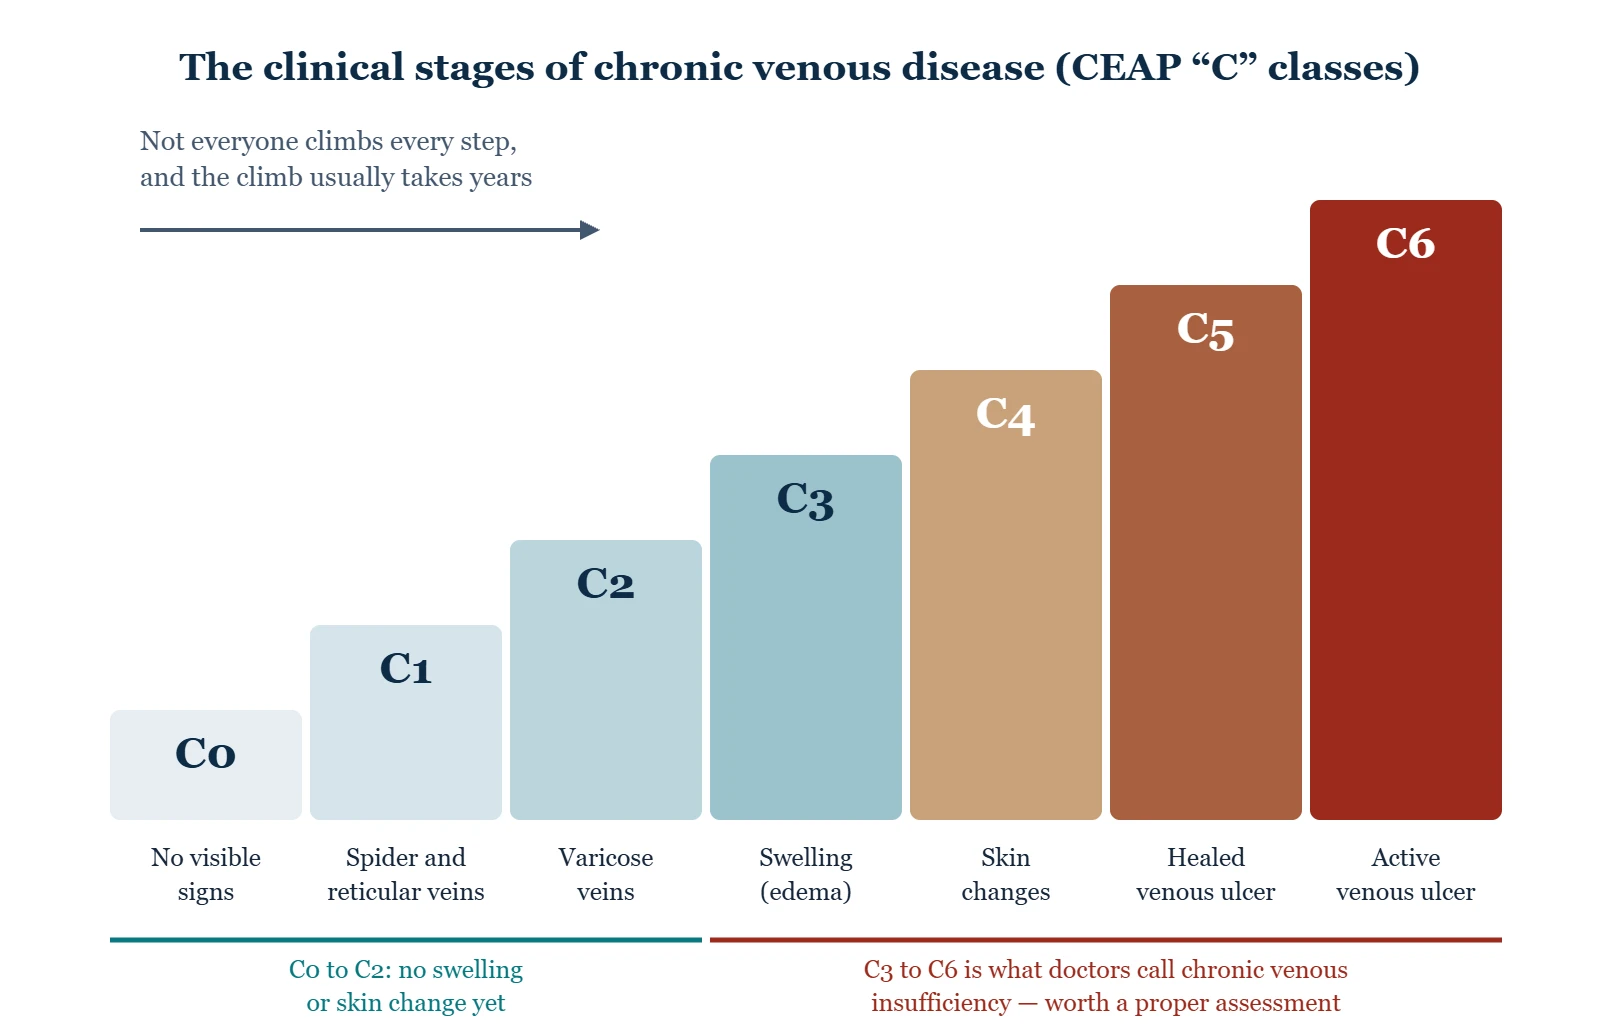
| Class | What it means | What you might notice |
|---|---|---|
| C0 | No visible signs | Aching or heaviness can still be present |
| C1 | Spider or reticular veins | Fine red, purple or blue veins, often around the ankle |
| C2 | Varicose veins | Bulging, twisting surface veins |
| C3 | Edema | Ankle swelling that builds through the day |
| C4a | Pigmentation or eczema | Brown staining; itchy, scaly or weeping skin |
| C4b | Lipodermatosclerosis or atrophie blanche | Hard, tight skin above the ankle; small white scars |
| C4c | Corona phlebectatica | A fan of fine veins around the ankle or instep |
| C5 | Healed venous ulcer | A scar where an ulcer has closed |
| C6 | Active venous ulcer | An open wound, usually above the inner ankle |
Not everyone travels the whole sequence, and it can take decades. Symptoms — aching, heaviness, tiredness, cramps, itching, restless legs — can be present at any stage, including C0. Clinicians generally reserve the term chronic venous insufficiency for class C3 (swelling) and above, so varicose veins on their own are not the same thing. The 2020 revision of CEAP added the C4c class and an “r” for disease that has come back after treatment.
Symptoms
- Heaviness, aching and tiredness in the legs, worse the longer you are upright, better after a night lying flat
- Ankle swelling that builds through the day and is largely gone by morning
- Itching, especially around the inner ankle
- Night cramps and restless legs
- Visible veins — thread veins at the ankle, varicose veins on the inner leg and calf
The pattern matters more than any one symptom: worse with standing and heat, better with walking and elevation. Leg pain that works the other way round — brought on by walking and relieved by standing still — points to the arteries instead. Arteries or veins? →
What causes the valves to fail
- A previous DVT. A clot damages the valves it sits against — the resulting picture is called post-thrombotic syndrome, and it develops in 20 to 50% of people after a DVT, usually within one to two years. Cleveland Clinic ranks a previous DVT as the most important risk factor of all.
- Inherited vein wall weakness. A strong family history is common.
- Pregnancy, through hormonal effects and increased pressure.
- Prolonged standing, which is why certain occupations feature heavily.
- Age and weight, both of which increase the load on the system.
- Reduced calf pump function — a stiff ankle, limited walking, or a shuffling gait means the pump does less work.
- Narrowing of a large vein in the pelvis, as in May-Thurner syndrome, which backs pressure up into one leg.
Assessment
A venous duplex ultrasound maps which veins are refluxing, how badly, and whether there is any clot. Reflux is defined by how long blood runs backward after the vein is squeezed and released: more than half a second in the surface, calf and perforating veins, and more than one second in the main thigh and knee veins. The scan is done standing when that is safe, so that gravity shows what the valves are doing. Alongside it, the arterial circulation is checked — usually with an ABI — because the answer determines whether compression is safe. That second step is not optional and is the reason this site keeps repeating it.
Treatment
| Approach | What it does | Notes |
|---|---|---|
| Graduated compression | Supports the veins, reduces swelling, slows skin change | The backbone of management. Requires arterial assessment and correct fitting. Not for anyone with a markedly low ABI, severe arterial disease or uncontrolled heart failure. For ulcers, at least 20–30 mmHg, ideally 30–40. |
| Elevation | Reduces venous pressure directly | Above heart level, for at least 30 minutes three or more times a day; a footstool is not enough. How → |
| Walking and ankle exercises | Engages the calf pump | Standing still is worse than walking or sitting |
| Weight loss where relevant | Lowers the pressure the veins work against | Helps swelling and symptoms |
| Skin care | Keeps fragile skin intact | Daily plain emollients; prompt attention to any break |
| Endovenous ablation | Closes a refluxing surface vein from the inside using heat, glue or a chemical | Common first-line procedure for suitable veins; done under local anesthetic |
| Foam sclerotherapy | Injected agent closes smaller or winding veins | Often for residual veins or veins near an ulcer |
| Deep vein stenting | Opens a narrowed or blocked pelvic vein | Specialist treatment for selected patients; after iliac vein stenting, 85–90% stay free of recurrent ulcers at five years |
| Ulcer care | Compression bandaging plus wound management | Clinician-applied; not a self-management task. Venous ulcers → |
For refluxing main surface veins, NICE recommends heat-based ablation first, then foam sclerotherapy, then surgery, and heat ablation closes the treated vein in roughly 85 to 93% of people at two years. When there is an ulcer, treating the reflux early pays off. In the EVRA trial of 450 people with venous leg ulcers, closing the refluxing vein within two weeks, alongside compression, healed ulcers faster than waiting until the ulcer had closed (a median of 56 days against 82), and in longer follow-up the ulcers also came back less often. Vascular surgery guidelines likewise recommend adding surface vein treatment to compression to reduce ulcer recurrence. Closing a refluxing vein does not remove the underlying tendency, so compression and the daily habits usually continue afterwards.
Compression is not a matter of buying the strongest ones
Higher pressure is not better; it is different, and it is chosen. Too much pressure is uncomfortable enough that people stop wearing them, which is worse than a lower pressure worn every day — and in a leg with impaired arterial supply it can cause harm. Compression safety → · Fit and pressure labels →
A day with venous insufficiency, done well
- Morning: put compression on before the swelling builds — ideally soon after getting up. Moisturize the lower legs first or at night, not under the stocking.
- Through the day: walk when you can; if your work keeps you standing, shift weight and do calf raises every half hour; if it keeps you sitting, circle and pump your ankles.
- Evening, and twice more if you can: lie down with your legs above heart level for at least 30 minutes. Cleveland Clinic’s advice is three or more times a day.
- Every day: look at the skin above both ankles. New itching, weeping, color change or a break in the skin is the time to act, not after it grows.
What supplements and medicines can and cannot do
The 2023 US vascular guideline suggests some vein supplements, such as micronized purified flavonoid fraction (MPFF), Ruscus extract and, more tentatively, horse chestnut, for pain, heaviness, cramps and swelling, while noting that none of them is an FDA-approved drug. In Cochrane reviews these “phlebotonics” slightly reduced swelling but had little or no effect on ulcer healing, and horse chestnut seed extract reduced leg volume and pain in short trials. They can ease symptoms; they do not replace compression or treat the reflux. For ulcers specifically, the prescription medicine pentoxifylline improved healing in a Cochrane review, including when added to compression. Diuretic “water tablets” are not a treatment for venous swelling unless something else, such as heart failure, is also present; they treat the symptom while leaving the cause untouched.
From the clinic
The single most common thing I see go wrong is compression that never gets worn. A stocking that is too tight, too hot, impossible to pull on over an arthritic hand, or the wrong length sits in a drawer. Nothing on this page works if that happens. If you have given up on stockings, go back and say why — there are lighter grades, zip and wrap-style garments, and donning aids, and a garment you actually wear beats a stronger one you do not.
Common questions
Is venous insufficiency the same as venous stasis?
Effectively yes. “Venous stasis” describes blood pooling in the lower leg; “chronic venous insufficiency” names the underlying valve failure. The skin changes it produces are called stasis dermatitis. They are three names circling one process.
Is chronic venous insufficiency serious?
It is not usually life-threatening, and unlike arterial disease it does not lead to amputation, but it is progressive and it can end in skin breakdown and ulcers that take months to heal and tend to come back. Treated early and consistently, most people keep it at the aching-and-swelling stage.
Will it keep getting worse?
Untreated, it tends to progress slowly. Consistent compression, elevation, walking and skin care meaningfully slow that, and procedures can address the reflux driving it. The variable that predicts most is whether the compression is actually worn, which is why fit and comfort are clinical issues rather than conveniences.
Can venous insufficiency be cured?
Damaged valves do not repair themselves, but treatment can take a refluxing surface vein out of the circuit and control the pressure in the rest. For many people that means symptoms largely settle and skin changes stop advancing, even though some ongoing care continues.
Do I need my varicose veins treated?
If they are visible and causing nothing, treatment is largely cosmetic. If they come with aching, swelling, skin changes or a previous ulcer, treating the reflux has a clinical purpose. The duplex ultrasound and your symptoms together decide, not the appearance alone. Varicose veins →
Do I have to wear stockings for three months before a vein procedure?
Many insurers require it, but the 2023 guideline from the Society for Vascular Surgery, the American Venous Forum and the American Vein and Lymphatic Society suggests against making a compression trial a condition of treating symptomatic reflux, noting the lack of evidence behind the rule. For symptomatic reflux in the main surface veins, the guidelines favor a procedure over long-term stockings, and NICE offers stockings only when a procedure is unsuitable. Your plan’s rules still apply, so ask the clinic how they handle it.
How long does a venous ulcer take to heal?
Most heal within six months with expert compression care, and in a Cochrane review compression made healing considerably faster and more likely than no compression. Closing a refluxing vein early can speed it further. Venous ulcers often come back, with recurrence reported in up to 70%, which is why compression stockings are advised indefinitely once an ulcer has healed. Venous ulcers →
Can exercise fix it?
Exercise cannot repair a leaky valve, but the calf pump is a major part of how the leg copes, so walking and ankle exercises genuinely help symptoms and swelling. Combined with compression they do more than either alone.
Why are my ankles brown?
When pressure in the veins stays high, red blood cells leak into the skin and leave iron behind, which stains it brown or rust-colored, usually above the inner ankle. The staining itself is harmless, but it is a sign that the venous pressure has been high for a long time and the skin needs protecting.
Where to go next
- Brown staining above the ankles: what it says about your veins
- Red dots on the legs: when they come from the veins
- Lipodermatosclerosis: hard, tight skin in vein disease
- Stasis dermatitis: the skin changes explained
- Venous leg ulcers
- Varicose veins: symptoms and treatment choices
- Vein procedures: what each one does
- Compression safety
- Choosing compression socks
- Heavy, tired legs
- Spider veins
- How to improve circulation in your legs and feet
- Are varicose veins dangerous? When to worry
- Weeping legs: when swollen legs leak fluid
Sources
- StatPearls. Venous insufficiency.
- Cleveland Clinic. Chronic venous insufficiency (CVI).
- MedlinePlus. Venous insufficiency.
- Society for Vascular Surgery. Chronic venous insufficiency (patient handout, PDF).
- NHS. Varicose eczema.
- NHS. Venous leg ulcer.
- NICE. Varicose veins: diagnosis and management (CG168).
- American Family Physician. Venous ulcers: diagnosis and treatment (2019).
- Society for Vascular Surgery, American Venous Forum and American Vein and Lymphatic Society. 2023 clinical practice guidelines for varicose veins of the lower extremities, part II.
- CEAP 2020 update. The 2020 update of the CEAP classification system and reporting standards.
- Society for Vascular Surgery and American Venous Forum. 2011 clinical practice guidelines for varicose veins and associated chronic venous diseases.
- EVRA trial. A randomized trial of early endovenous ablation in venous ulceration. N Engl J Med 2018.
- EVRA trial. Long-term clinical and cost-effectiveness of early endovenous ablation in venous ulceration. JAMA Surg 2020.
- Cochrane. Compression bandages or stockings versus no compression for treating venous leg ulcers.
- Cochrane. Phlebotonics for venous insufficiency.
- Cochrane. Horse chestnut seed extract for chronic venous insufficiency.
- Cochrane. Pentoxifylline for treating venous leg ulcers.
- StatPearls. Venous leg ulcer.
Written by Tom Biernacki, DPM, FACFAS. Published 20 September 2026. Updated 15 October 2026. General education, not medical advice.