Venous leg ulcers are the most common leg wound, they are largely a pressure problem rather than a wound problem, and they heal with compression. That last sentence is the whole page in miniature — but the compression only goes on after someone has checked the arteries.
The NHS defines a leg ulcer as a sore that takes more than two weeks to heal, and estimates that more than 60% of leg ulcers are venous. American Family Physician puts venous ulcers at 1 to 3% of Americans, and 4% of adults aged 65 and older.
When a leg ulcer needs urgent attention
Same day for spreading redness and warmth around the wound, increasing pain, foul discharge, fever or chills, or a wound that has grown noticeably in a few days. Infection in a leg that already drains poorly escalates faster than people expect.
Prompt assessment for a leg ulcer that is very painful, sits on the toes or the outer ankle rather than the inner one, has a dry pale or black base, or comes with a cold foot and weak pulses. That pattern is arterial, and compression would be the wrong treatment. More →
What a venous ulcer looks like
It sits in the gaiter area — the band between the ankle and the calf — and most often just above the inner ankle bone. It is shallow with an irregular border, the base is usually pink or yellow and moist rather than dry, and it weeps. It is often uncomfortable rather than severe, and the discomfort typically eases when the leg is raised.
The skin around it has usually been telling the story for years: brown or rusty staining, dry itchy flaking, swelling that comes and goes with the day, and sometimes a hardened, tight, narrowed band above the ankle that makes the leg look like an inverted champagne bottle. Those skin changes come first, and recognizing them is the chance to prevent the ulcer entirely. Stasis dermatitis →
Telling the three common ulcers apart
| Type | Where, and what it looks like | Pain, skin and pulses |
|---|---|---|
| Venous | Inner ankle and gaiter area; shallow, irregular edge, moist and weeping | Aching, better with the leg raised; staining, swelling, eczema, hardening; pulses usually present |
| Arterial | Toes, heel, outer ankle and pressure points; deep, punched-out edge, dry pale or black base | Severe, worse with the leg raised and better hanging down; thin, shiny, hairless, cool skin; pulses weak or absent |
| Neuropathic | Ball of the foot, under the big toe, anywhere that takes pressure; round, with a thick rim of callus | Often painless, which is why it is found late; callus, dry skin, reduced sensation; pulses either |
Mixed ulcers exist, and they are common enough that the assessment below is not optional in anyone.
What the assessment should include
- An ankle-brachial index before any compression. This is the single most important step, and it is the one most often skipped. Compression on a leg with significant arterial disease can cause harm: StatPearls lists an ABI below 0.5 as a reason not to compress at all, and American Family Physician guidance rules out firm 30 to 40 mmHg compression below 0.6. The ABI →
- A look at the whole leg and both feet, not just the wound — including between the toes.
- Measurement of the ulcer, so progress is a fact rather than an impression. Photographs with a ruler in frame work well.
- Duplex ultrasound of the leg veins to find which veins are leaking. This is what makes treatment of the underlying cause possible. The venous scan →
- Blood tests for diabetes, anemia, kidney function and nutrition, which all affect healing.
- A swab only if infection is suspected. Every open wound grows bacteria; a positive swab from a wound that looks fine is not a reason for antibiotics.
- A biopsy if the ulcer looks atypical or shows no sign of healing after 4 to 12 weeks of proper treatment. A small number of long-standing ulcers turn out to be something else, including skin cancer, and this is how that gets found.
What actually heals them
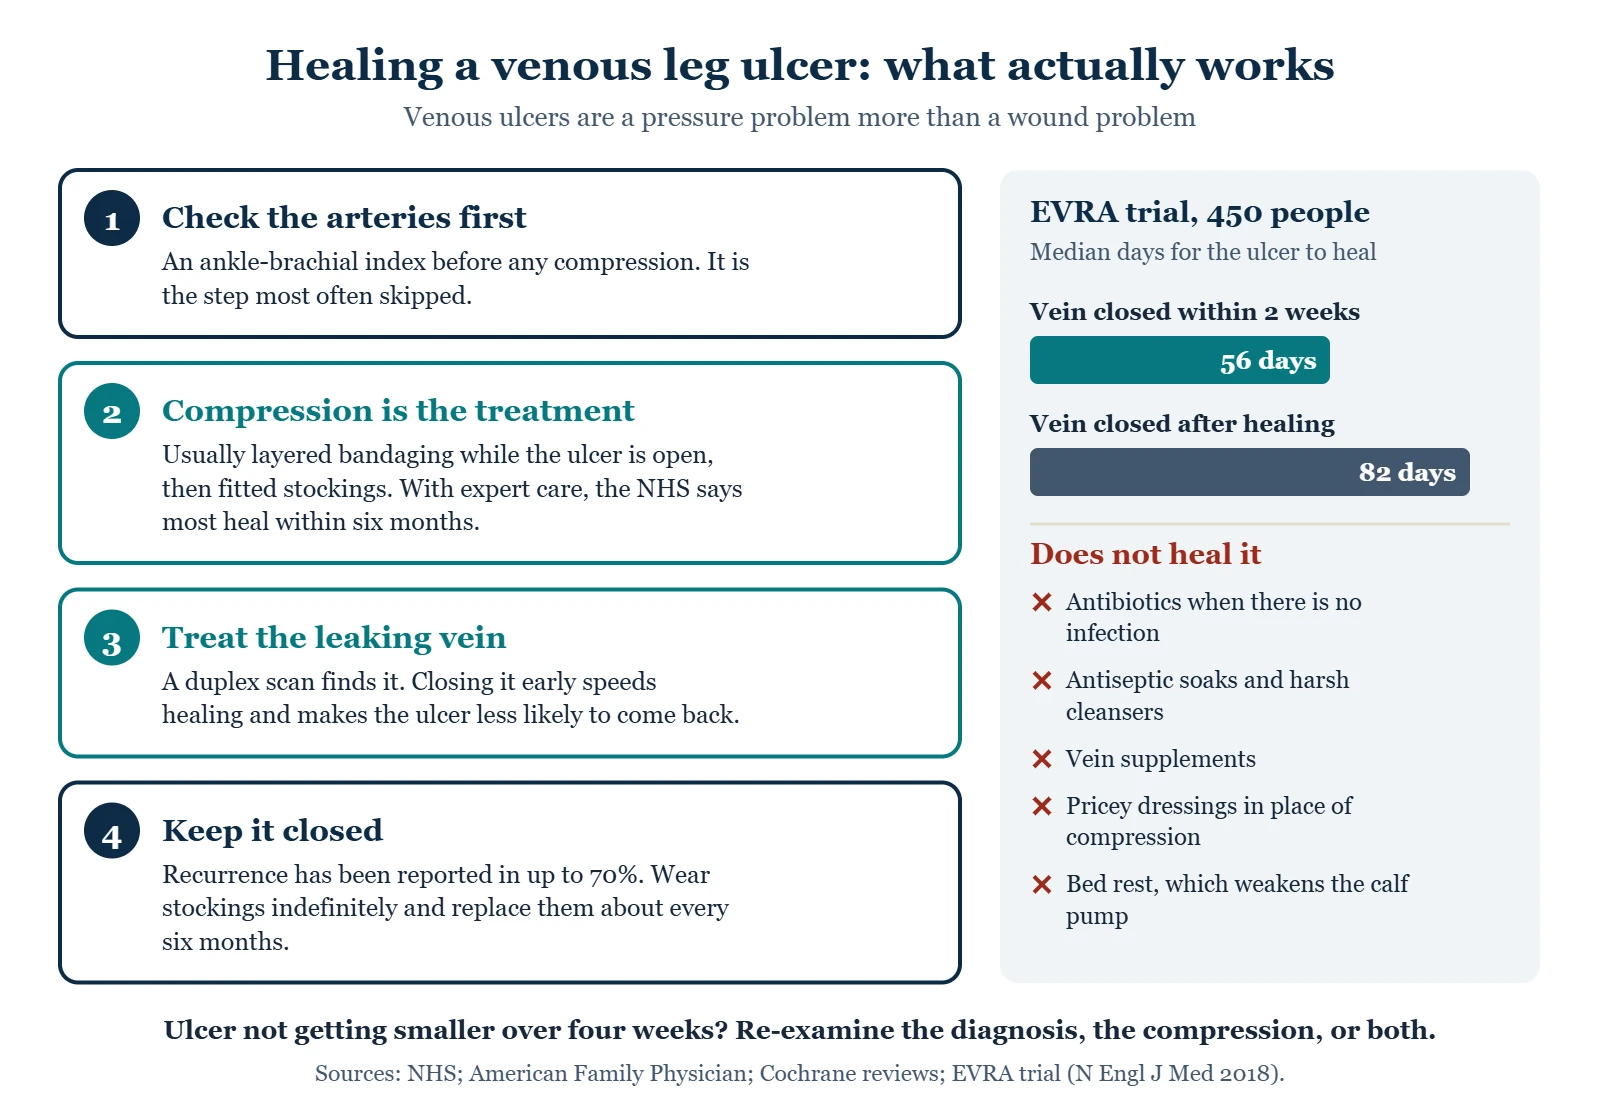
Compression is the treatment. Not the dressing, not an antibiotic, not a cream — compression. In a Cochrane review of 14 trials, compression healed ulcers considerably faster than no compression, made healing within a year more likely, and probably reduced pain. With expert compression care, the NHS says most venous ulcers heal within six months. Multi-layer bandaging applied by someone trained in it is the usual approach while the ulcer is open, moving to fitted stockings once it closes; American Family Physician guidance advises at least 20 to 30 mmHg, and preferably 30 to 40. If compression is uncomfortable to the point that you take it off, say so rather than abandoning it, because there are several systems and a different one often works. Safety first, then fit.
Treating the underlying vein problem changes the outcome. Closing the leaking veins — usually with a catheter-based technique done under local anesthetic — helps ulcers heal faster and makes them less likely to come back. In the EVRA trial of 450 people, closing the refluxing vein within two weeks healed ulcers in a median of 56 days, against 82 days when the procedure waited until the ulcer had healed, and in longer follow-up the ulcers came back less often. Vascular surgery guidelines recommend adding surface vein treatment to compression to reduce recurrence. How the underlying problem works →
The rest supports those two. Simple non-adherent dressings chosen for how much fluid the wound produces, rather than expensive ones. Raising the legs above heart level for periods during the day. Walking and ankle exercises, which work the calf muscle pump. Treating the surrounding eczema. Attention to protein intake and blood sugar. For stubborn ulcers, the prescription medicine pentoxifylline improved healing in a Cochrane review, including when added to compression.
What does not help
- Antibiotics for a wound that is not infected. They treat infection; they do not heal the ulcer.
- Antiseptic soaks and harsh cleansers, which damage the healing surface.
- Over-the-counter creams on the surrounding skin containing neomycin, lanolin, calamine or benzocaine, which MedlinePlus advises avoiding.
- Vein supplements as a healing treatment. In a Cochrane review they had little or no effect on ulcer healing.
- Expensive advanced dressings used in place of adequate compression.
- Bed rest, which weakens the calf pump that the whole system depends on.
Keeping it closed
This is the part that gets least attention and matters most. Venous ulcers come back often — recurrence has been reported in up to 70% — and American Family Physician advises wearing compression stockings indefinitely after healing, taking them off at night and replacing them about every six months, since they lose their compression with wear. The plan after healing should include correctly measured and fitted stockings at the right strength, a replacement schedule, treatment of any leaking veins that have not been addressed, daily skin care and moisturizing, and a low threshold for getting any new break in the skin looked at early. Getting the fit right →
From the clinic
The venous ulcers that heal fastest are the ones where compression went on in the first week and the vein scan happened soon after. The slowest are the ones that spent months under expensive dressings with no compression at all, or with compression that kept coming off because it hurt and nobody adjusted it. The wound is rarely the problem; the pressure underneath it is.
Common questions
How long does a venous ulcer take to heal?
With expert compression care, the NHS says most heal within six months, and American Family Physician figures suggest 30 to 60% heal by 24 weeks and 70 to 85% within a year. Treating the leaking vein early can shorten that: in the EVRA trial, the median was 56 days. A useful rule is that an ulcer getting meaningfully smaller over four weeks is on track; one that is not is a reason to re-examine the diagnosis, the compression, or both — rather than to keep doing the same thing for another month.
Why do I need compression if the wound is on my skin?
Because the wound is a symptom of pressure. Failing valves let blood fall back down the leg, pressure in the small vessels stays high, fluid and inflammatory cells leak into the tissue, and the skin eventually breaks down. Compression counteracts that pressure. Treating the surface without treating the pressure is why some ulcers stay open for years.
Can I get it wet or shower?
Showering is usually fine with the wound covered, and your team will tell you what suits the dressing you have. What to avoid is soaking the leg in a bath or a basin for long periods, and harsh soaps and antiseptics on the wound itself.
My ulcer smells. Is it infected?
Not necessarily. Heavily exuding wounds and some dressings smell without infection being present. The signs that matter are spreading redness and warmth, increasing pain, fever, and the wound getting bigger. Any of those together with odor should be seen the same day.
Will antibiotics heal it?
No. The NHS is clear that antibiotics do not help ulcers heal; they are for treating infection when it is present. Repeated courses for an ulcer that is not getting smaller are usually a sign that compression, or the vein problem underneath, has not been addressed.
Should I have my veins treated if the ulcer is already healing?
It is worth asking about. Closing the refluxing veins is what reduces the chance of the ulcer returning, and recurrence is the main long-term problem with venous ulcers. In the EVRA trial, treating the vein early, rather than waiting for the ulcer to close, sped healing and reduced recurrence. Ask for a duplex ultrasound and a conversation about it rather than assuming that a healed ulcer means the job is finished.
Where to go next
- Hemosiderin staining: what brown skin above the ankle means
- Lipodermatosclerosis: the skin change that often comes before an ulcer
- Chronic venous insufficiency explained
- Stasis dermatitis: the warning stage
- Compression safety
- A wound that will not heal: the wider picture
- Leg compression machines: when a pump is prescribed
- Arterial ulcers: how they look and how they heal
Sources
- NHS. Venous leg ulcer and treatment.
- American Family Physician. Venous ulcers: diagnosis and treatment (2019).
- American Family Physician. Diagnosis and treatment of venous ulcers (2010).
- American Family Physician. Chronic wounds: evaluation and management (2020).
- Cochrane. Compression bandages or stockings versus no compression for treating venous leg ulcers.
- EVRA trial. A randomized trial of early endovenous ablation in venous ulceration. N Engl J Med 2018.
- EVRA trial. Long-term clinical and cost-effectiveness of early endovenous ablation in venous ulceration. JAMA Surg 2020.
- Society for Vascular Surgery and American Venous Forum. 2011 clinical practice guidelines for varicose veins and associated chronic venous diseases.
- Cochrane. Pentoxifylline for treating venous leg ulcers.
- Cochrane. Phlebotonics for venous insufficiency.
- StatPearls. Venous leg ulcer.
- MedlinePlus. Stasis dermatitis and ulcers.
- MedlinePlus, National Library of Medicine. Venous Ulcers — Self-Care.
- Society for Vascular Surgery. Chronic Venous Insufficiency.
- National Institute of Diabetes and Digestive and Kidney Diseases. Diabetes and Foot Problems.
Written by Tom Biernacki, DPM, FACFAS. Published 21 September 2026. Updated 15 October 2026. General education, not medical advice.