Varicose veins are surface veins that have become enlarged and twisted because the valves inside them stopped closing properly. Whether they need treating has little to do with how they look and a lot to do with what else the leg is doing — and the best treatments today are office procedures with a short recovery, not the vein stripping many people still picture.
When a varicose vein needs urgent attention
- Bleeding from a varicose vein. Lie down, raise the leg high, press firmly over the point with a clean pad, and call 911. Raising the leg is what stops it — standing up makes it worse.
- A hard, hot, red, tender cord along a vein — this can be superficial thrombophlebitis, which needs assessment because it can extend into the deep system.
- A break in the skin near the ankle that is not healing.
- A whole leg suddenly swollen and painful — that is a different problem and needs same-day assessment. More →
What counts as a varicose vein
Doctors separate leg veins you can see into three sizes. Spider veins (telangiectasias) are fine red or purple threads under 1 mm across. Reticular veins are the flat blue-green veins of 1 to 3 mm. Varicose veins are 3 mm or more across, usually raised, rope-like or twisted, and most often on the inner leg and the back of the calf. They are very common. England’s NICE guideline estimates that at least a third of people have visible varicose veins, the Society for Vascular Surgery puts the number of Americans affected at as many as 40 million, and in the long-running Framingham study 23% of men and 30% of women developed them over 16 years.
The size distinction matters because the cause and the treatment differ. Spider veins are mostly a cosmetic issue; more on those here. Varicose veins are a sign that a valve-bearing surface vein is leaking — usually the great saphenous vein running up the inside of the leg, or the small saphenous vein at the back of the calf.
Symptoms
Many varicose veins cause nothing at all. When they do, the symptoms have a recognizable rhythm: they build through the day, are worse after standing still and in hot weather, and ease with walking, lying down or raising the legs.
- Aching, heaviness or a throbbing, tired feeling in the legs
- Burning or itching over the veins
- Night cramps and restless legs
- Ankle swelling that is worse in the evening
- Itchy, dry or discolored skin around the ankle in longer-standing cases
Symptoms do not track neatly with size. Large, bulging veins can be painless, and modest-looking ones can ache, which is why an ultrasound — not a glance — decides what is going on underneath.
Why they happen
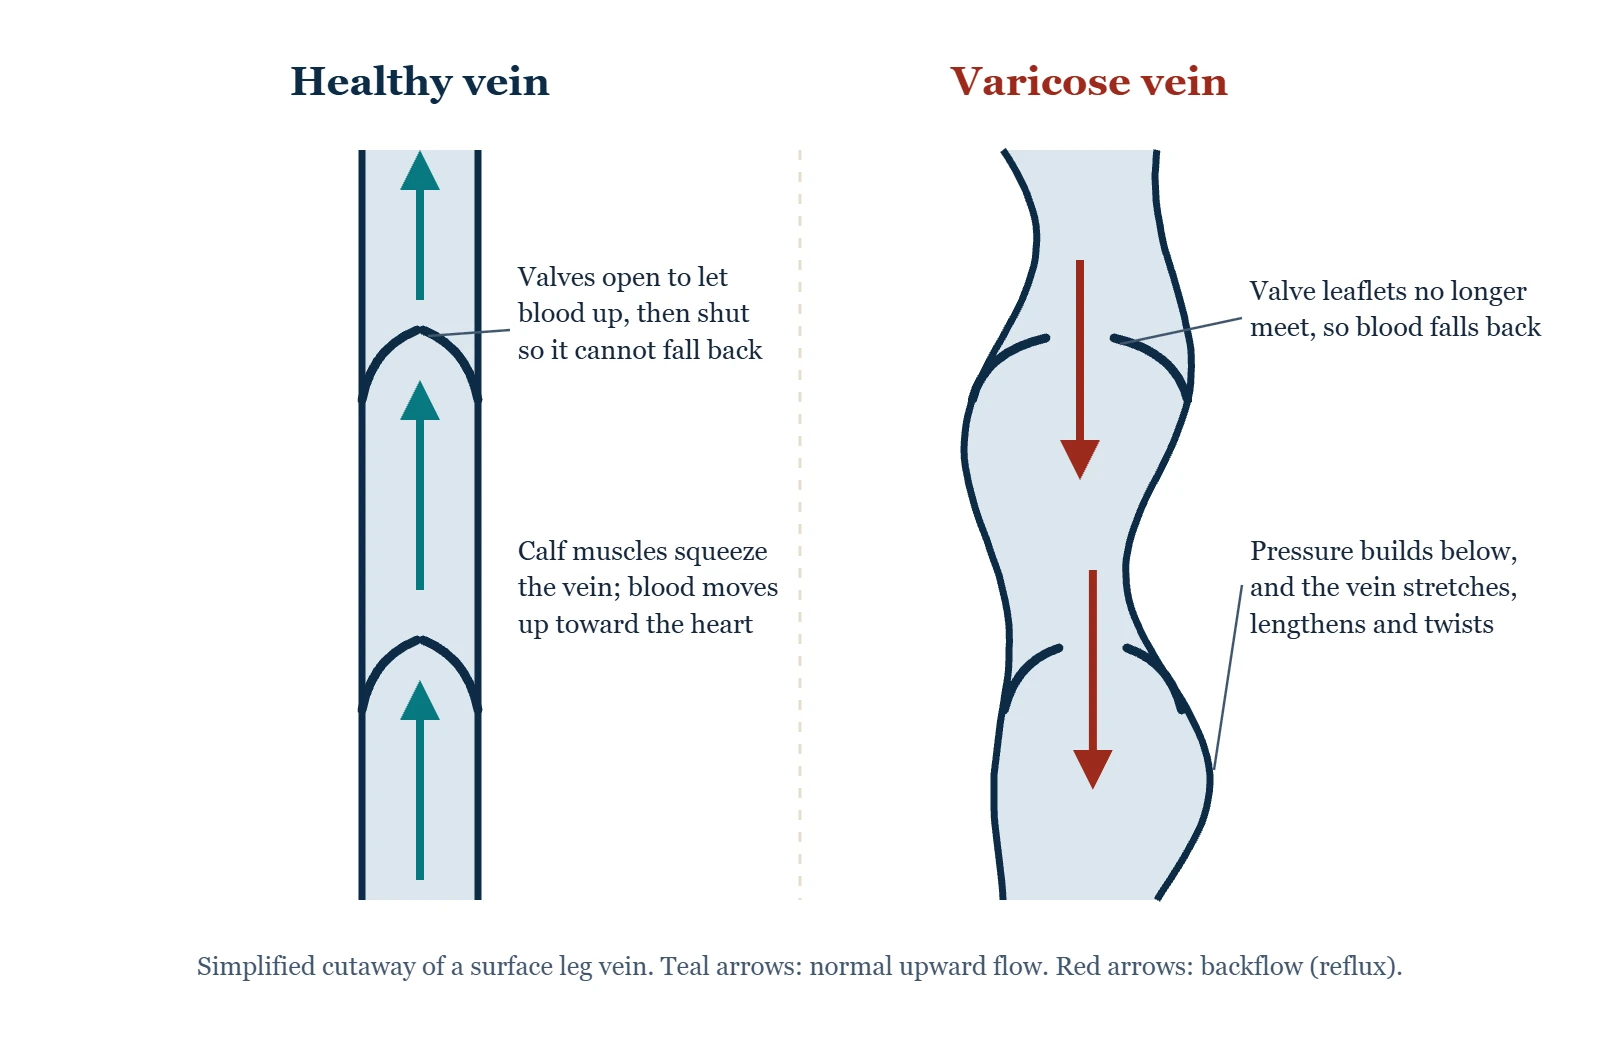
Leg veins carry blood upward against gravity, helped by the calf muscles and a series of one-way valves. When valves leak, blood refluxes downward and pressure rises in the veins below. Surface veins have less support from surrounding tissue than deep veins, so they stretch, lengthen and become visibly tortuous.
Contributing factors: a strong family history, being female, pregnancy, age, jobs that involve prolonged standing, a previous deep vein clot, and higher body weight. Most people with varicose veins have more than one of these. Mayo Clinic singles out family history and obesity as the two main ones.
Cosmetic or clinical — the distinction that matters
| Mostly cosmetic | Clinically significant |
|---|---|
| Visible veins, no symptoms | Aching, heaviness or throbbing that builds through the day |
| Thread veins and spider veins | Ankle swelling that clears overnight |
| No skin change | Itching, dryness or eczema over the lower leg |
| No swelling | Brown or rust staining above the ankle |
| Stable over years | Skin becoming firm and tight; a previous or current ulcer |
The right-hand column is the same disease process moving forward — what doctors call chronic venous insufficiency. Those features are the argument for treating the underlying reflux rather than the appearance, and they are what most insurers look for too.
When to get them checked
The UK’s NICE guideline sets out thresholds that translate well to the US. Varicose veins that bleed need to be seen straight away. Veins that cause symptoms, veins with skin changes such as staining or eczema, a clot in a surface vein, and a leg ulcer that has not healed within two weeks all warrant a vein specialist. Veins that are purely visible and cause nothing do not need treating for medical reasons.
In practice: if your veins ache, swell, itch or bleed, if the skin above your ankle is changing color or texture, or if you have had a clot in one, it is worth a proper vein assessment rather than just living with it.
Assessment
A venous duplex ultrasound maps which veins are refluxing and how badly, and checks for clot. It needs to include a standing or tilted portion, because valve leakage only shows properly when gravity is loading the veins — a scan done entirely lying flat can miss reflux. Leakage counts as abnormal when blood runs backward for more than half a second in a surface vein, or for more than a second in the main deep veins of the thigh and knee. Alongside it, an arterial check establishes whether compression is safe.
More on what the two ultrasounds do →
Treatment options
| Treatment | How it works | What to expect |
|---|---|---|
| Endovenous thermal ablation (radiofrequency or laser) | A thin catheter heats the leaking vein from the inside so it seals shut, under local anesthetic | Usually the first choice for a leaking main surface vein. You walk out the same day, and in a large review of laser ablation about 97% of treated veins were still closed at three to five years |
| Non-thermal ablation (medical glue or mechanochemical) | The vein is sealed with medical adhesive, or with a rotating wire plus a sclerosing drug, without heat | An equally acceptable alternative in US guidelines, with fewer numbing injections and, for glue, less compression afterwards. About 7% of people react to the glue |
| Foam sclerotherapy | A foamed drug injected under ultrasound guidance makes the vein scar shut | Suits smaller or winding veins and veins left after ablation. Less durable for the main vein: in the CLASS trial about half of foam-treated veins were still closed at five years, against 89% after laser |
| Phlebectomy | Bulging surface veins are removed through tiny nicks in the skin | Often done in the same session as ablation; bruising for a week or two |
| Surgical stripping | The vein is tied off and removed under general or spinal anesthesia | Now rarely performed, because ablation means less pain and a quicker return to activity; typically one to two weeks off work |
Closing a vein does not remove the underlying tendency, so new veins can appear over the years and compression and daily habits usually continue. In a long-term review of laser ablation, about a third of patients (36.6%) had some recurrence within five years — mostly new veins rather than the treated one reopening. It is more likely with obesity, long daily sitting, or a pregnancy after treatment.
Why the order of treatment differs between countries
UK guidance from NICE recommends going straight to endothermal ablation for symptomatic varicose veins, then foam sclerotherapy if ablation is unsuitable, then surgery — and advises against compression stockings as the treatment unless a procedure is not suitable. The current US guidelines from the Society for Vascular Surgery and American Venous Forum likewise recommend a procedure over long-term stockings for a leaking saphenous vein, and suggest against making people wear stockings for three months first. Many US insurers still require that trial anyway: Michigan’s Medicare contractor, for example, requires symptoms plus a failed three-month trial of conservative care, and treats a procedure without them as cosmetic. So the stocking trial is usually an insurance step rather than a medical one. If you are heading toward treatment, start it early, wear them, and keep a record.
What recovery after a vein procedure looks like
- Walking out the same day. Endovenous procedures are done under local anesthetic, and walking straight afterwards is encouraged rather than allowed.
- Compression for about a week afterwards in many practices. Guidance differs between countries and clinics, so follow your own team’s instructions.
- Bruising, tightness and a pulling sensation along the treated vein for a week or two are common and expected.
- A follow-up ultrasound is often done to confirm the vein has closed and that no clot has extended into the deep system.
- Get same-day care, with an ultrasound, for new calf swelling and pain; call 911 for breathlessness or any chest pain. A clot after vein treatment is uncommon but can reach the lungs.
Varicose veins in pregnancy
Pregnancy raises blood volume and hormone levels, and the growing womb presses on the pelvic veins, so varicose veins often appear or worsen — sometimes in the vulva as well as the legs. The Society for Vascular Surgery estimates that half or more of American women develop varicose veins in pregnancy. In most cases they return to normal within a year of delivery, although each further pregnancy makes lasting veins more likely. Compression stockings and leg elevation help with symptoms during pregnancy; procedures are generally postponed until after the baby is born, partly because many veins settle on their own.
Living with them
- Keep moving. Walking uses the calf pump, one of the main things helping venous return. MedlinePlus suggests walking or swimming for 30 minutes, five days a week. Long periods of standing still are the hard part, not exercise.
- Break up standing and sitting. Calf raises or a short walk every half hour or so make a noticeable difference by the end of the day.
- Raise your legs above heart level three or four times a day for 5 to 15 minutes — a footstool alone does little. How to elevate properly →
- Compression eases aching and swelling, once an arterial check has confirmed it is safe and the size is right; 20–30 mmHg suits most people with symptomatic veins. Choosing compression socks →
- Weight — reducing it lowers the pressure the veins have to work against.
- Look after the skin above the ankle with a plain moisturizer, and do not scratch itchy patches over veins. Skin care →
What creams and supplements do
Nothing applied to the skin closes a leaking valve. Some products reduce the sensation of heaviness, which is a real benefit and a different claim from treating the disease. Of the supplements, horse chestnut seed extract has the best evidence: in a Cochrane review of people with chronic venous insufficiency it modestly reduced leg volume compared with placebo, with mild and infrequent side effects. Vein supplements as a group probably reduce swelling slightly but have not been shown to improve quality of life or heal ulcers, and US guidelines give them only a weak recommendation for symptom relief. None is an FDA-approved drug, raw horse chestnut seeds are poisonous, and anything you take is worth mentioning to your clinician. Be wary of anything promising to “remove” varicose veins topically — the vein is a structure several millimeters under the skin, and no cream reaches it.
From the clinic
The varicose veins I worry about are rarely the impressive-looking ones. They are the modest veins with a rim of brown staining above the inner ankle, or itchy, shiny skin there that someone has been treating as eczema for a year. That skin is telling you the venous pressure has been high for a long time, and it is the step before an ulcer. If that is what your ankle looks like, the conversation should be about treating the reflux — not about whether the veins are worth fixing for appearance.
Common questions
Will varicose veins get worse if I leave them?
They tend to progress slowly, and the progression is in the underlying venous pressure rather than just the appearance. Whether that matters depends on whether you have symptoms or skin changes. Visible veins with nothing else are often stable for years; veins with aching, swelling and staining are further along a path that can end in skin breakdown.
Are varicose veins dangerous?
Usually not. The complications worth knowing are bleeding from a thin-walled vein, a painful clot in a surface vein (superficial thrombophlebitis), and, over years, skin damage and ulcers around the ankle. They are not the same as a deep vein clot, but they are linked: in one large study, people with varicose veins were diagnosed with a deep vein clot about five times as often. New swelling or pain in one leg still needs a same-day check.
Does crossing my legs cause them?
There is no good evidence that it does. Family history, weight, pregnancy, age and prolonged standing are the real contributors.
Can I exercise with varicose veins?
Yes, and you should. Walking uses the calf pump, which is one of the main things helping your venous return. Prolonged standing still is the difficult one, not movement.
Do compression stockings get rid of varicose veins?
No. They support the veins and ease aching and swelling while you wear them, but they do not close a leaking valve or make existing veins disappear. They are a symptom treatment, and a useful one — after an arterial check confirms they are safe for you.
Which treatment is best?
For a leaking saphenous vein, endovenous ablation — closing the vein from inside with heat — is the usual first choice, with non-thermal options and foam sclerotherapy as alternatives. The right answer depends on the size and route of the vein, what the ultrasound shows, and your other health conditions, which is why it is a decision made with the scan in hand.
Do they come back after treatment?
The treated vein stays closed in most cases — about 97% at three to five years after laser ablation in one large review — but the underlying tendency remains, and around a third of people develop some new veins within five years. That is not treatment failure; it is the reason daily habits continue afterwards and a check-up makes sense if symptoms return.
Will insurance cover it?
Often, when the veins are causing problems. Most plans look for documented symptoms or skin changes, an ultrasound showing reflux, and a trial of compression before approving a procedure, and treat purely cosmetic work as not covered. Michigan’s Medicare contractor, for example, requires symptoms and a failed three-month trial of conservative care, and does not cover spider veins unless they bleed. Ask your plan what it requires, because the documentation has to be gathered in advance.
Where to go next
- Lipodermatosclerosis: hard, brown skin above the ankle
- Vein procedures: what each one does
- The underlying venous insufficiency
- Spider veins: causes and treatment
- Skin changes above the ankle
- Choosing compression socks
- Compression safety
- Heavy, tired legs
- Are varicose veins dangerous? When to worry
- Compression socks for varicose veins
Sources
- NHS. Varicose veins.
- National Institute for Health and Care Excellence (NICE). Varicose veins: diagnosis and management (CG168) — recommendations.
- NICE. CG168 — introduction.
- National Heart, Lung, and Blood Institute. Varicose Veins.
- Society for Vascular Surgery. Varicose veins and spider veins (patient guide).
- Gloviczki P, et al. Society for Vascular Surgery, American Venous Forum and American Vein and Lymphatic Society. Clinical practice guidelines for the management of varicose veins of the lower extremities, Part I. J Vasc Surg Venous Lymphat Disord, 2023.
- Gloviczki P, et al. Clinical practice guidelines for the management of varicose veins, Part II.
- StatPearls, NCBI Bookshelf. Varicose Veins.
- StatPearls, NCBI Bookshelf. Endovenous Laser Ablation.
- StatPearls, NCBI Bookshelf. Radiofrequency Ablation.
- StatPearls, NCBI Bookshelf. Superficial Vein Thrombosis.
- Cochrane. Endovenous ablation and foam sclerotherapy versus open surgery for great saphenous vein varices.
- Cochrane. Compression stockings for the initial treatment of varicose veins.
- Cochrane. Horse chestnut seed extract for chronic venous insufficiency.
- Cochrane. Phlebotonics for venous insufficiency.
- NICE. Cyanoacrylate glue occlusion for varicose veins (IPG670).
- Centers for Medicare & Medicaid Services. Local Coverage Determination L34536: Treatment of Varicose Veins of the Lower Extremities.
- Mayo Clinic. Varicose veins — symptoms and causes.
- MedlinePlus. Varicose veins — self-care.
- MedlinePlus. Varicose vein stripping.
Written by Tom Biernacki, DPM, FACFAS. Published 21 September 2026. Updated 15 October 2026. General education, not medical advice.