Both cause leg symptoms. Both are called “circulation problems”. They are close to opposites, and the single most consequential difference is that the standard treatment for one can be harmful in the other.
Why this matters in practice
Compression is a mainstay of venous treatment. In a leg where the arterial supply is poor, compression can reduce blood flow further, and both American Family Physician and NICE treat significant artery disease as a reason not to use strong compression. NICE advises that anyone who needs compression hosiery should be assessed for PAD first. That is why this site keeps saying the arterial check comes before the socks — it is not caution for its own sake. Compression safety →
The mechanisms, in one sentence each
PAD is narrowed arteries: not enough blood getting into the leg. It affects an estimated 10 to 12 million US adults over 40.
Chronic venous insufficiency is leaky vein valves: blood not getting out of the leg efficiently, so pressure builds. Estimates for US adults range from 10% to 35%, depending on how it is defined.
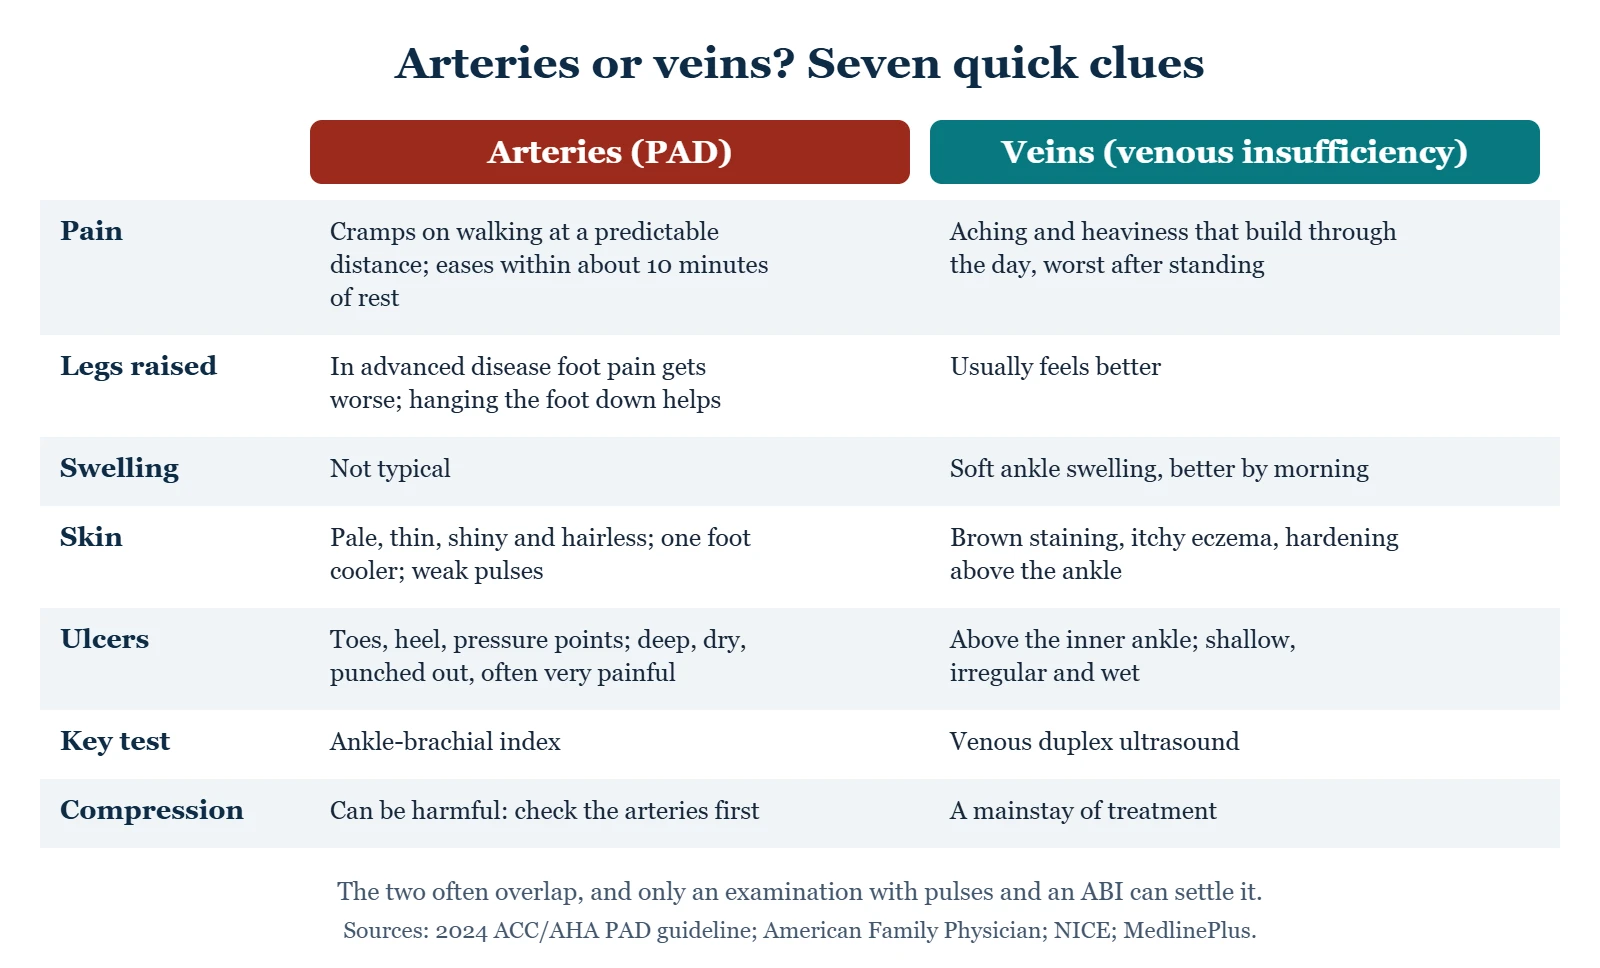
Telling them apart
| PAD (arterial) | Venous insufficiency | |
|---|---|---|
| Pain pattern | Cramping or fatigue in the calf, thigh or buttock that starts after a predictable walking distance and eases within about 10 minutes of rest | Aching, heaviness, cramping or itching that builds through the day, worst after prolonged standing |
| Effect of walking | Brings the pain on | Often feels better moving than standing still |
| Effect of elevation | In advanced disease, raising the leg worsens foot pain; people dangle the foot | Relieves symptoms |
| Time of day | Related to activity, not the clock — except rest pain at night in advanced disease | Worse in the evening, better in the morning |
| Swelling | Not typical | Typical — soft, around the ankle, better overnight |
| Skin color | Pale when raised, dusky red when hanging down | Brown or rust staining above the ankle |
| Skin texture | Thin, shiny, hairless; slow-growing toenails | Dry, itchy, eczema-like; later hard and thickened |
| Temperature | One foot often cooler than the other | Usually normal or warm |
| Pulses | Weak or absent | Usually normal |
| Ulcer location | Toes, heel, top of the foot, bony pressure points | Above the inner ankle (the “gaiter” area) |
| Ulcer appearance | Deep, dry, punched out with sharp edges; typically very painful, especially at night | Shallow, irregular, wet; can be painful |
| Key test | Ankle-brachial index, plus toe pressures when needed | Venous duplex ultrasound |
| Compression | Potentially harmful — assess first | Central to treatment |
The overlaps that catch people out
- Classic symptoms are the exception. Only about a third of people with PAD have textbook claudication, and about one in five report no symptoms at all. “My legs ache when I walk” and “my legs ache at the end of the day” are both ambiguous; the reproducible distance-then-relief pattern is what points to arteries, and the build-through-the-day pattern points to veins.
- You can have both. Arterial disease is present in up to a quarter of people with venous disease or venous ulcers, according to American Family Physician and StatPearls. Mixed disease is managed differently from either alone, with compression modified or withheld depending on the arterial numbers.
- Nerve damage masks the arterial story. In diabetes, reduced sensation can remove the pain that would otherwise signal claudication or an ulcer, and stiff, calcified arteries can make the ABI read normal or high. NICE warns against ruling out PAD in someone with diabetes on the strength of a normal or raised ABI. Neuropathy or circulation? →
- Both cause ulcers, and an ulcer does not announce its type. Venous ulcers are the large majority of lower-leg ulcers — about 65% by NICE’s estimate and 80% by American Family Physician’s — but location and appearance are not definitive. That is why anyone with a suspected venous ulcer should have their pulses checked and an ABI before compression bandaging. Venous ulcers →
Reading the tests
The ankle-brachial index compares blood pressure at the ankle with the arm. Under the 2024 American College of Cardiology and American Heart Association guideline, 0.90 or below is abnormal, 0.91 to 0.99 borderline, 1.00 to 1.40 normal, and above 1.40 means the arteries are too stiff to compress — in which case toe pressures are needed, with a toe-brachial index of 0.70 or below abnormal. A normal reading does not end the question in diabetes: in nearly a quarter of people with limb-threatening disease, the ABI reads in the normal range.
A venous duplex ultrasound is the test of choice for venous reflux. It counts blood falling backward for more than half a second in the surface veins, or more than a second in the main deep veins, as reflux.
For compression, the ABI sets the limits. Wound-care references grade it: full compression when the ABI is normal, more cautious or modified compression with a vascular referral as it falls toward 0.6, and no sustained compression, with urgent referral, below 0.6 (or an ankle pressure under 60 mmHg or a toe pressure under 30 mmHg). American Family Physician advises against 30 to 40 mmHg compression when the ABI is below 0.6, and a reading above about 1.3 to 1.4 is treated as unreliable rather than reassuring. These are decisions for the clinician holding the numbers, not thresholds to apply yourself.
Treated almost opposite ways
For PAD: supervised walking carries the guideline’s strongest recommendation — 30 to 45 minutes, at least three times a week for at least 12 weeks, walking until the pain is moderate to near-maximal, resting, and repeating — alongside a high-intensity statin, antiplatelet treatment, stopping smoking and foot care, with cilostazol for claudication and a procedure for limb-threatening disease or symptoms that do not respond. Walking with PAD →
For venous insufficiency: compression is central — in a Cochrane review of 14 trials, people treated with compression were about twice as likely to have their venous ulcer heal at any point than those without it — together with raising the legs above the heart for 30 minutes three or four times a day, and treatment of the refluxing veins themselves, with heat-based ablation NICE’s first choice. Up to 70% of venous ulcers come back, which is why compression usually continues after healing. The venous insufficiency guide →
The one question worth asking yourself
Does putting your legs up make it better or worse? Better points venous. Worse — particularly foot pain at night that eases when you hang the foot down — points arterial, and that is a symptom to be seen about promptly rather than to note with interest.
What happens at the appointment
- History: the pattern, the timing, the effect of walking and elevation, and what else you have.
- Examination: pulses, skin, temperature and swelling, with both legs compared. Being able to feel all four foot pulses makes PAD unlikely.
- An ABI, and toe pressures if you have diabetes, kidney disease or a reading above 1.40.
- A venous duplex ultrasound if reflux or a clot is in question.
- A plan that reflects which system — or both — is involved. NICE suggests referral to a vascular service for varicose veins causing symptoms, skin changes from venous disease, or a leg ulcer that has not healed after two weeks.
From the clinic
The most consequential question about a swollen, discolored leg is often not “is this venous?” but “is the arterial supply good enough for compression?” I still meet people wearing strong compression stockings for swelling when their foot pulses are barely there. The order matters: pulses and an ABI first, then compression at the strength the numbers allow. And when a leg has both problems, the arteries usually get dealt with first, because no ulcer heals without a blood supply.
Common questions
Can I have both PAD and venous insufficiency?
Yes, and it is not rare: arterial disease is present in up to a quarter of people with venous ulcers. Mixed disease changes the plan substantially — compression may be reduced, modified or avoided entirely depending on the arterial pressures, and the arterial problem is usually addressed first because healing depends on blood supply.
Can I wear compression socks if I have PAD?
Only after an ABI and a conversation with your clinician. Mild arterial disease may allow reduced compression under supervision, but strong compression is avoided when the arterial supply is poor — American Family Physician advises against 30 to 40 mmHg compression when the ABI is below 0.6. Compression safety →
Should I put my legs up?
For venous swelling, yes: above the level of the heart for about 30 minutes, three or four times a day. For advanced arterial disease, raising the leg can make foot pain worse, and hanging the foot down eases it — which is itself a sign to be seen promptly.
What is a normal ABI?
Between 1.00 and 1.40. A reading of 0.90 or below means PAD, 0.91 to 0.99 is borderline, and above 1.40 means the arteries are too stiff to measure reliably, so toe pressures are used instead. What the ABI measures →
Is PVD the same as PAD?
Peripheral vascular disease is the broader umbrella and technically includes venous disease; peripheral artery disease specifically means the arteries. In everyday use the two are often swapped, so it is worth asking which one is meant when you see it on a letter.
My ulcer is on my inner ankle. Does that mean it is venous?
It points that way, and most ulcers in that area are venous — but location alone does not settle it, and the consequence of getting it wrong is significant, because venous ulcers are treated with compression. That is why a pulse check and an ABI are standard before compression bandaging, whatever the ulcer looks like.
Which is more serious?
Different kinds of serious. PAD carries a substantially raised risk of heart attack and stroke, and its most advanced form, chronic limb-threatening ischemia, develops in an estimated 11% to 20% of people with PAD and historically carried a high risk of amputation and death within a year. Venous disease is not life-threatening, but untreated it tends to progress and causes long-term skin damage, ulcers and considerable day-to-day misery. Neither is a reason to relax about the other.
Where to go next
Sources
- Gornik HL, et al. 2024 ACC/AHA multisociety guideline for the management of lower extremity peripheral artery disease. Circulation 2024.
- National Heart, Lung, and Blood Institute. PAD — Symptoms.
- Society for Vascular Surgery. Chronic Venous Insufficiency.
- American Family Physician. Venous ulcers: diagnosis and treatment (2019).
- American Family Physician. Diagnosis and treatment of venous ulcers (2010).
- American Family Physician. Chronic wounds: evaluation and management (2020).
- Cochrane. Compression bandages or stockings versus no compression for treating venous leg ulcers (2021).
- Society for Vascular Surgery, American Venous Forum and American Vein and Lymphatic Society. 2023 clinical practice guidelines for varicose veins of the lower extremities, part II.
- NICE. Peripheral arterial disease: diagnosis and management (CG147).
- NICE. Varicose veins: diagnosis and management (CG168).
- StatPearls. Venous Leg Ulcer.
- MedlinePlus, National Library of Medicine. Venous insufficiency.
- Mayo Clinic. Peripheral artery disease (PAD).
- Cleveland Clinic. Foot and toe ulcers.
- NHS. Leg ulcer — diagnosis.
Written by Tom Biernacki, DPM, FACFAS. Published 20 September 2026. Updated 16 October 2026. General education, not medical advice.