Cold feet are one of the most common reasons people start worrying about circulation — and one of the weakest signs of it on its own. Most cold feet are not arterial. The ones that are usually come with company: one foot colder than the other, weak pulses, pain on walking, or a sore that will not heal.
Cold plus any of these needs attention now
A foot or leg that turns suddenly cold, pale, mottled, numb or severely painful over minutes to hours is an emergency — call 911. Blood supply can be cut off abruptly, and permanent damage can happen within four to six hours.
Get seen the same day for a cold foot that also has: a wound that will not heal, a new dark patch on a toe or heel, pain in the foot at rest or at night, or a color that has clearly changed compared with the other foot. Go to an emergency department now for a toe or patch of skin that has turned black, gray or dark purple, or looks dead.
The honest starting point
Plenty of people with entirely normal arteries have permanently cold feet, and plenty of people with significant arterial disease have warm ones. Temperature alone is a poor test, which is why this page is about the combination of findings rather than the symptom by itself.
The feet are also designed to get cold. When the body needs to conserve heat, it narrows the small blood vessels in the hands and feet first to protect the core. Because they are the farthest point from the heart, the feet are usually the first part of you to chill and the last to warm up again, and Cleveland Clinic describes the narrowing itself as a normal, healthy response to cold. Several of the conditions that exaggerate it, including Raynaud’s, chilblains and an underactive thyroid, are more common in women.
One useful distinction before anything else: feet that feel cold to you and feet that are cold to someone else’s hand are different findings. The first often points toward nerves; the second toward blood flow. Ask someone to touch both of your feet and compare them with your calves and with each other.
What causes cold feet
| Cause | What usually comes with it |
|---|---|
| Just being cold, or a cool house | Both feet, resolves with warm socks, no other findings |
| Peripheral artery disease | Weak or absent pulses, thin shiny hairless skin, slow nails, leg pain on walking, wounds that will not heal. Often one foot colder than the other |
| Raynaud’s phenomenon | Color changes in a sequence — white, then blue, then red — triggered by cold or stress, often fingers too, with tingling as it recovers |
| Peripheral neuropathy | Feet feel cold but are warm to touch; burning, tingling, numbness; both feet, starting at the toes |
| Underactive thyroid | Cold everywhere, fatigue, weight change, dry skin, constipation |
| Anemia, including iron deficiency | Tiredness, breathlessness on exertion, pallor |
| Chilblains | Itchy, red or purple, sometimes swollen patches on the toes a few hours after damp cold that is not freezing; they usually clear in two to three weeks |
| Smoking | Nicotine makes vessel spasm more likely, and smoking raises the risk of arterial disease two- to four-fold |
| Some medicines | Cold hands or feet is a common side effect of beta blockers; ergotamine migraine medicines and pseudoephedrine decongestants can do it too. Raise it with the prescriber rather than stopping anything suddenly |
| Very low body weight | Feeling cold all over, not just in the feet |
Raynaud’s: when the color changes
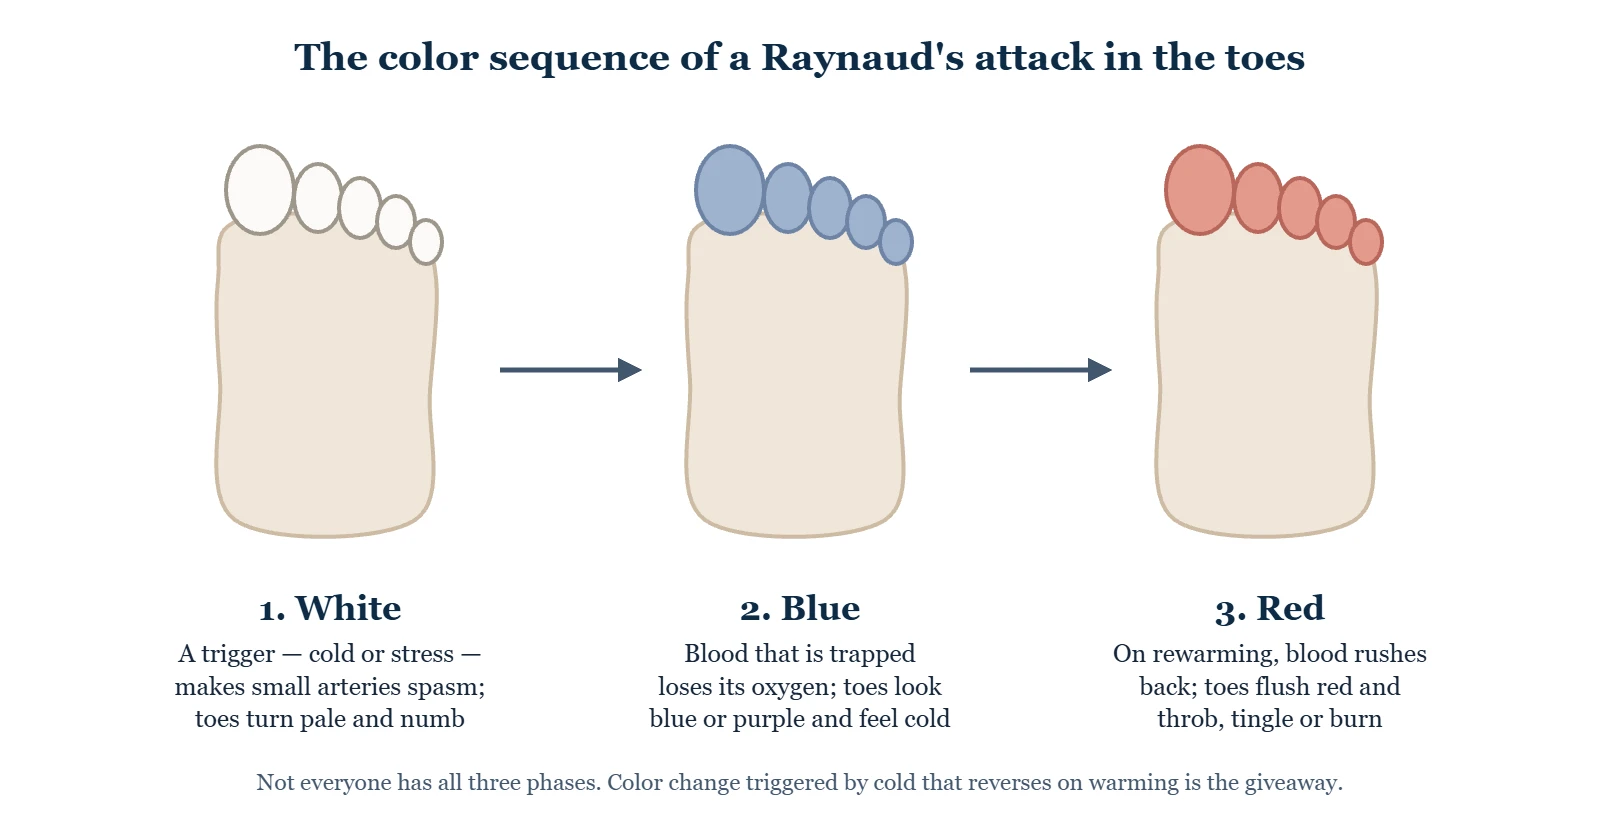
Raynaud’s is a spasm of small blood vessels rather than a blockage. The giveaway is the sequence and the trigger: a sharply demarcated color change brought on by cold or stress, which reverses on warming, often with numbness during the attack and throbbing or tingling as it ends. It is common, affecting an estimated 3 to 5 percent of adults worldwide, more often women. A typical attack lasts around 20 minutes but can run from a few minutes to hours, and many people only ever see one or two of the three colors. Nicotine makes attacks more likely, and so can some medicines, including beta blockers, decongestants containing pseudoephedrine or phenylephrine, ergotamine migraine drugs and stimulants such as methylphenidate.
It comes in two forms. Primary Raynaud’s occurs on its own, is much more common, usually starts in the teens or twenties, and is a nuisance rather than a danger. Secondary Raynaud’s comes with another condition — most often an autoimmune disease such as scleroderma or lupus — tends to start later, can be more serious, and occasionally causes sores on the tips of the toes or fingers. A first episode after about age 30, attacks on one side only, or any sore on a toe or fingertip are reasons to get it looked at.
Cold feet and diabetes
Diabetes complicates cold feet in two directions. It raises the risk of arterial disease, so a cold foot is more likely to mean something. And it damages nerves, so feet can feel cold, burning or numb when they are actually warm — or fail to feel heat at all. Nerve damage may affect up to half of people with diabetes, and the American Diabetes Association warns that it makes it easy to burn your feet with hot water, hot water bottles or heating pads. Its advice is simple: the best way to warm cold feet is warm socks. If you have diabetes and cold feet, the right next step is a foot examination with pulses and sensation testing, not a heating pad. Nerves or circulation? →
What to check yourself
- Compare the two feet. One noticeably colder than the other is more meaningful than both being cold.
- Have someone else touch them. Cold to them, or only cold to you?
- Look at the skin and nails. Shiny, hairless skin and thickened slow-growing nails are arterial signs.
- Note what happens on walking. Calf or thigh cramping that comes on at a predictable distance and eases with rest is the symptom that changes the picture entirely.
- Watch for color sequences. White then blue then red on cold exposure points toward Raynaud’s.
- Check for wounds. Any break in the skin on a cold foot deserves prompt attention.
What a clinician will do
Feel the pulses in both feet, look at skin, hair and nails, test sensation, and — if anything points that way — measure the ankle-brachial index. Blood tests for thyroid function and anemia are common, and if Raynaud’s looks secondary, tests for autoimmune disease. The examination takes minutes and settles most of this.
What actually helps
- Warm socks and layers, and keeping the whole body warm rather than only the feet — core temperature drives peripheral blood flow. Wool or synthetic socks stay warmer than cotton once feet sweat.
- Dry feet and dry socks. Damp feet lose heat quickly; change socks after exercise.
- Shoes with room. Tight footwear and tight socks restrict blood flow to the toes.
- Movement. Walking, and wiggling the toes and circling the ankles when you have been sitting for a while, keep blood moving.
- Stopping smoking, which helps both the spasm and the underlying disease. More →
- Treating what is found — thyroid, anemia, arterial disease, or a medication swap. Raynaud’s that is frequent or severe can be treated with medicines that relax the blood vessels, most often a calcium channel blocker such as nifedipine, which some people take only through the colder months.
What not to do
Do not apply direct heat — heating pads, hot water bottles, hot soaks or foot spas — if you have reduced sensation or known arterial disease. Feet that cannot feel temperature burn easily, and a burn on a poorly supplied foot is a serious wound. Warm socks are the safe answer. Test bath water with your hand or elbow, never your foot. Heated socks: who should ask first →
From the clinic
“My feet are always cold” is one of the most common things I hear, and most of the time the examination is reassuring: good pulses, healthy skin, two feet that match. The finding that changes my thinking is asymmetry — one foot cool, pale or slow to pink up while the other is fine. Two cold feet are usually a thermostat question. One cold foot is a plumbing question, and it deserves an ABI.
Common questions
Do cold feet mean poor circulation?
Usually not by themselves. Cold feet with normal pulses, normal skin and no pain on walking are very often just cold feet. It is the combination — one foot colder than the other, weak pulses, skin changes, walking pain, or a wound — that suggests arterial disease.
Why are my feet cold at night?
Often simply because you are still, the room is cooler and the body is conserving heat. Loose bed socks and a warm room help. Foot pain at night that eases when you hang the foot over the side of the bed is different — that can be arterial rest pain and should be seen promptly.
My feet feel freezing but my partner says they are warm. What is that?
That pattern points toward the nerves rather than blood flow. Damaged sensory nerves can misreport temperature, so the sensation is real even though the foot is objectively warm. It is worth mentioning, because it often comes alongside other neuropathy findings. More →
Can low iron cause cold feet?
It can. Anemia, including iron deficiency, is a common cause of feeling cold generally, along with tiredness and breathlessness on exertion. A simple blood test checks for it — do not start iron tablets without one.
Will compression socks warm my feet?
They are not a treatment for cold feet, and if the cause turns out to be poor arterial supply they can be unsuitable. Compression helps the venous system; it does not increase arterial delivery into the foot. Why the check comes first →
Should I get my circulation tested?
Worth discussing if you smoke or have smoked, have diabetes or kidney disease, are over 65, or have any of the accompanying findings above. The ankle-brachial index is quick and painless, and gives a real answer rather than a guess.
Can blood pressure tablets cause cold feet?
Some can. Cold hands or feet is a common side effect of beta blockers, which are used for blood pressure, heart conditions and migraine. Do not stop one suddenly, because that can be dangerous, but do raise it with your prescriber, who can weigh whether something else would suit you better.
Is it chilblains or frostbite?
Chilblains come from damp cold that is not freezing: itchy red or purple patches appear on the toes a few hours later and usually clear in two to three weeks. Frostbite is tissue actually freezing, with white or grayish-yellow skin that feels unusually firm or waxy and numb, and it needs an emergency department now. Do not rub frostbitten skin, and never rewarm either one with a heating pad, radiator or stove, because numb skin burns easily.
Where to go next
- Numb toes: common causes and warning signs
- Acrocyanosis: hands and feet that stay blue or purple
- Trench foot: when cold, wet feet become an injury
- Frostbite and frostnip: what to do when toes freeze
- Poor circulation in the legs and feet: the bigger picture
- PAD symptoms and warning signs
- Red, blue, pale or purple feet
- Neuropathy vs. poor circulation
- What the ABI measures
- Heated socks and insoles: who should ask first
- How to improve circulation in your legs and feet
- Burning or numb feet: where to start
- Cold feet at night: why your body is warm but your feet are not
- Raynaud’s syndrome: fingers and toes that turn white, then blue
- Chilblains on the toes: causes, treatment and when to worry
- Socks for swollen feet: non-binding, wide and warm
- Near Howell or Bloomfield Township, Michigan: a foot and ankle evaluation (the author’s own practice)
Sources
- Cleveland Clinic. Cold feet.
- Cleveland Clinic Health Essentials. Why are my hands and feet always cold?
- Cleveland Clinic. Acute limb ischemia.
- Mayo Clinic. Peripheral artery disease (PAD): symptoms and causes.
- Cleveland Clinic. Peripheral artery disease (PAD).
- MedlinePlus Genetics. Raynaud phenomenon.
- Cleveland Clinic. Raynaud’s phenomenon.
- National Institute of Arthritis and Musculoskeletal and Skin Diseases. Raynaud’s phenomenon.
- National Institute of Arthritis and Musculoskeletal and Skin Diseases. Raynaud’s phenomenon: diagnosis, treatment and steps to take.
- NHS. Raynaud’s.
- Mayo Clinic. Raynaud’s disease: diagnosis and treatment.
- Mayo Clinic. Diabetic neuropathy.
- American Diabetes Association. Foot complications.
- MedlinePlus. Diabetes: taking care of your feet.
- MedlinePlus. Diabetic foot.
- Mayo Clinic News Network. Cold feet that aren’t cold to the touch may indicate a neurologic problem.
- Cleveland Clinic. Hypothyroidism.
- Mayo Clinic. Iron deficiency anemia.
- MedlinePlus. Cold intolerance.
- Mayo Clinic. Beta blockers.
- Mayo Clinic. Chilblains.
- NHS. Chilblains.
- CDC. Preventing frostbite.
Written by Tom Biernacki, DPM, FACFAS. Published 21 September 2026. Updated 15 October 2026. General education, not medical advice.